

まとめ
ベータブロッカーは,特にリポフィルのベータブロッカーは,睡眠の連続性を妨害し,覚醒を増加させる可能性があります. これらの中枢神経系 (CNS) 効果は,コントロールされた研究中に健康な被験者に観察されました.
科学分野:
- 薬理学 薬理学とは
- 神経科学は神経科学である.
- スリープ・メディシン (睡眠医学)
背景:
- ベータブロッカーは,一般的に処方される薬です.
- 中枢神経系 (CNS) の副作用は,ベータブロッカーの使用で頻繁に報告されています.
- 異なるベータブロッカーの中枢神経系効果を理解することは,患者のケアにとって極めて重要です.
研究 の 目的:
- 4つのベータブロッカー (アテノロール,メトプロロール,プロプラノロール,ピンドロロール) とプラセボのCNS機能に対する効果を比較する.
- 睡眠を含む中枢神経系機能の客観的および主観的な測定値を評価する.
- ベータブロッカーのリポフィリシティが中枢神経系に与える影響を調査する.
主な方法:
- ダブルブラインド,プラセボ対照,ラテン正方形のデザイン研究.
- 30人の健康な男性被験者は,5つの異なる治療法 (ベータブロッカー4種,プラセボ1種) をそれぞれ1週間,そして2週間のシャワウアウト期間で受けた.
- 評価には,ポリソムノグラフィー,精神運動検査,気分,睡眠,性機能に関する主観的なアンケートが含まれていました.
主要な成果:
- リポフィルベータブロッカー (メトプロロール,プロプラノロール,ピンドロロール) は,プラセボとアテノロールと比較して,睡眠中の覚醒と覚醒を大幅に増加させた.
- ピンドロロルは,目動きの急速な睡眠時間 (REM) をユニークで有意に短縮し,REMの遅延時間を増加させた.
- 主観的な報告は客観的な発見を裏付け,リポフィルベータブロッカーの服用で覚醒と不安が増加することを示しました.
結論:
- リポフィリティは,ベータブロッカーの中枢神経系の副作用,特に睡眠の連続性に影響を与える重要な要因です.
- 異なるベータブロッカーは,睡眠構造に異なる影響を及ぼし,ピンドロロールはレム睡眠に明確な影響を及ぼします.
- これらの発見は,ベータブロッカーの関連の中枢神経系の副作用を評価する際に,個々の薬物特性を考慮することの重要性を強調しています.
関連する概念動画
 01:17
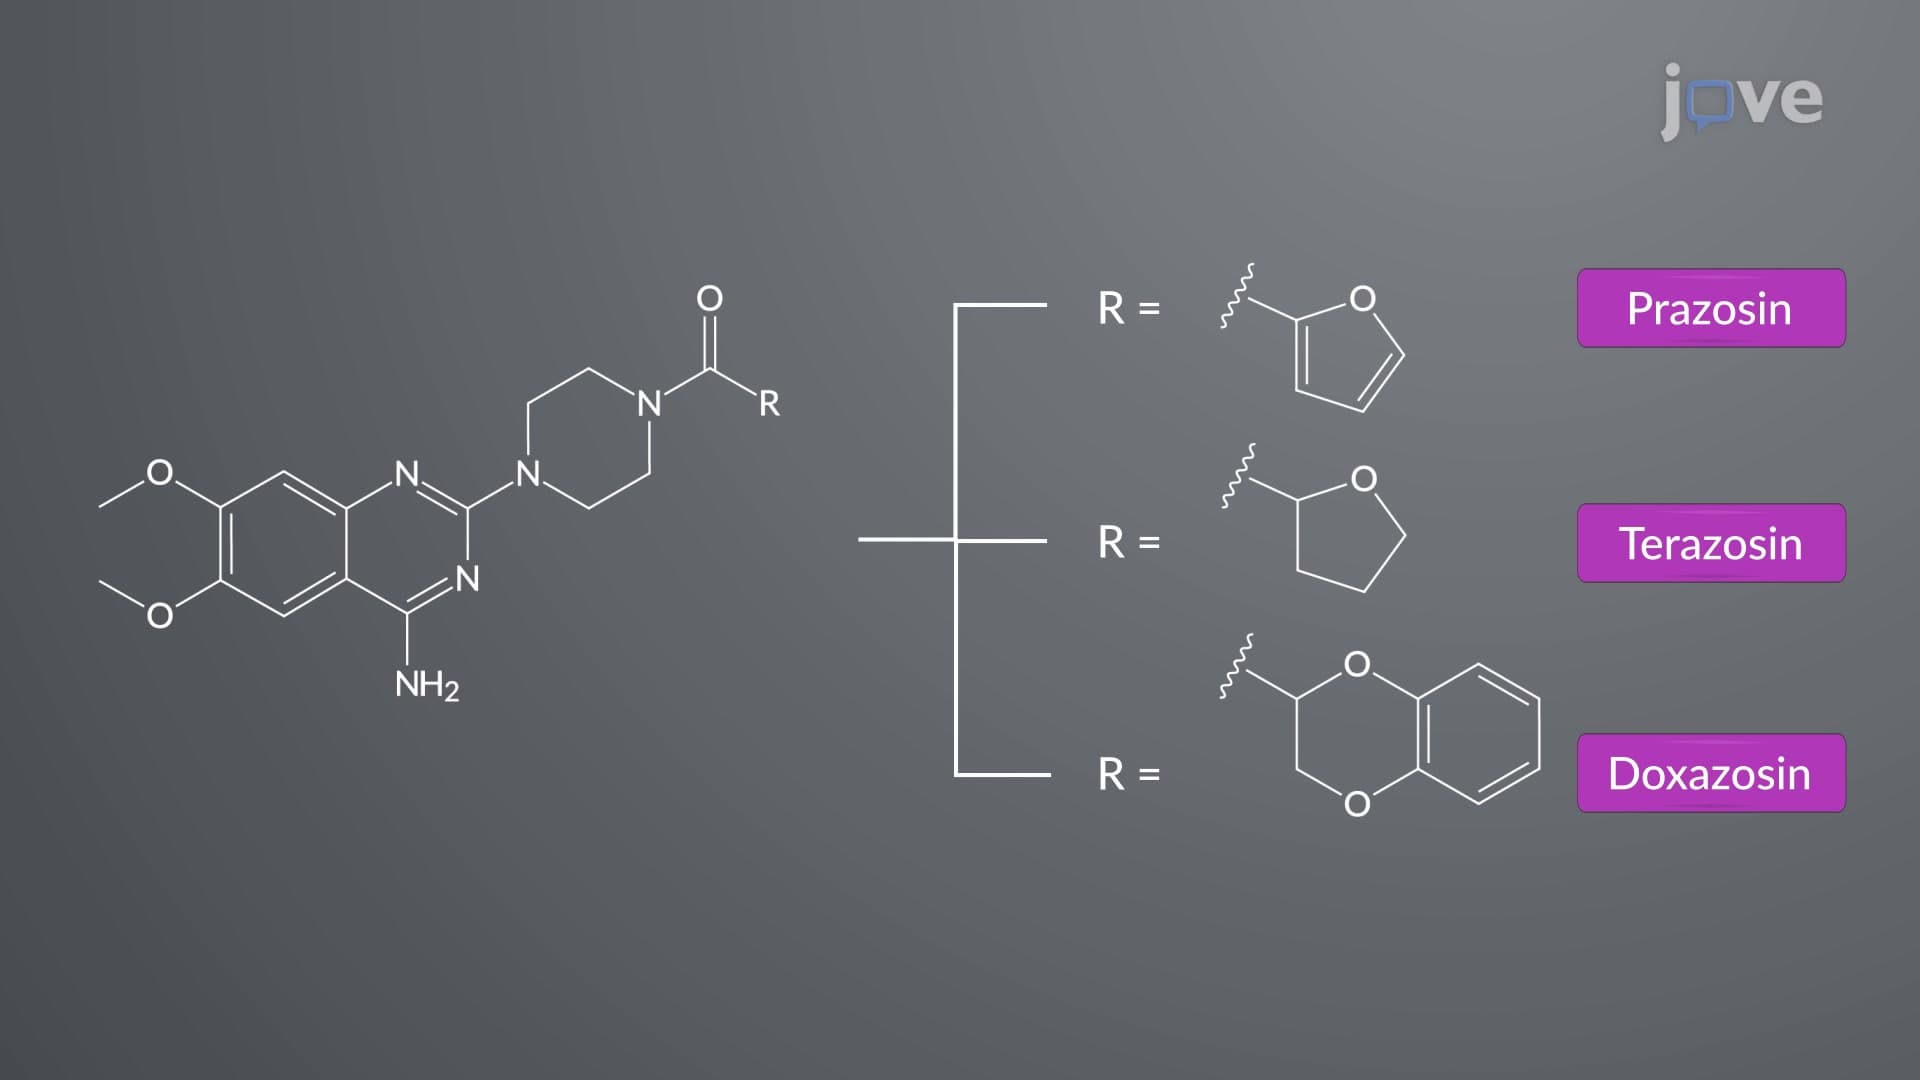
Adrenergic Antagonists: Chemistry and Classification of ɑ-Receptor Blockers
Adrenergic antagonists, or sympatholytics, inhibit adrenoceptor activation driven by catecholamines or agonists. Based on their adrenoceptor specificity, adrenergic blockers can be categorized into two primary groups: α-adrenergic blockers (α-blockers) and β-adrenergic blockers (β-blockers). α-blockers interact with α1 and α2 subtypes of α-adrenoceptors.
Nonselective α-blockers: Nonselective α-blockers contain haloalkylamine or imidazoline moieties. Phenoxybenzamine, with a haloalkylamine...
Nonselective α-blockers: Nonselective α-blockers contain haloalkylamine or imidazoline moieties. Phenoxybenzamine, with a haloalkylamine...
 01:25
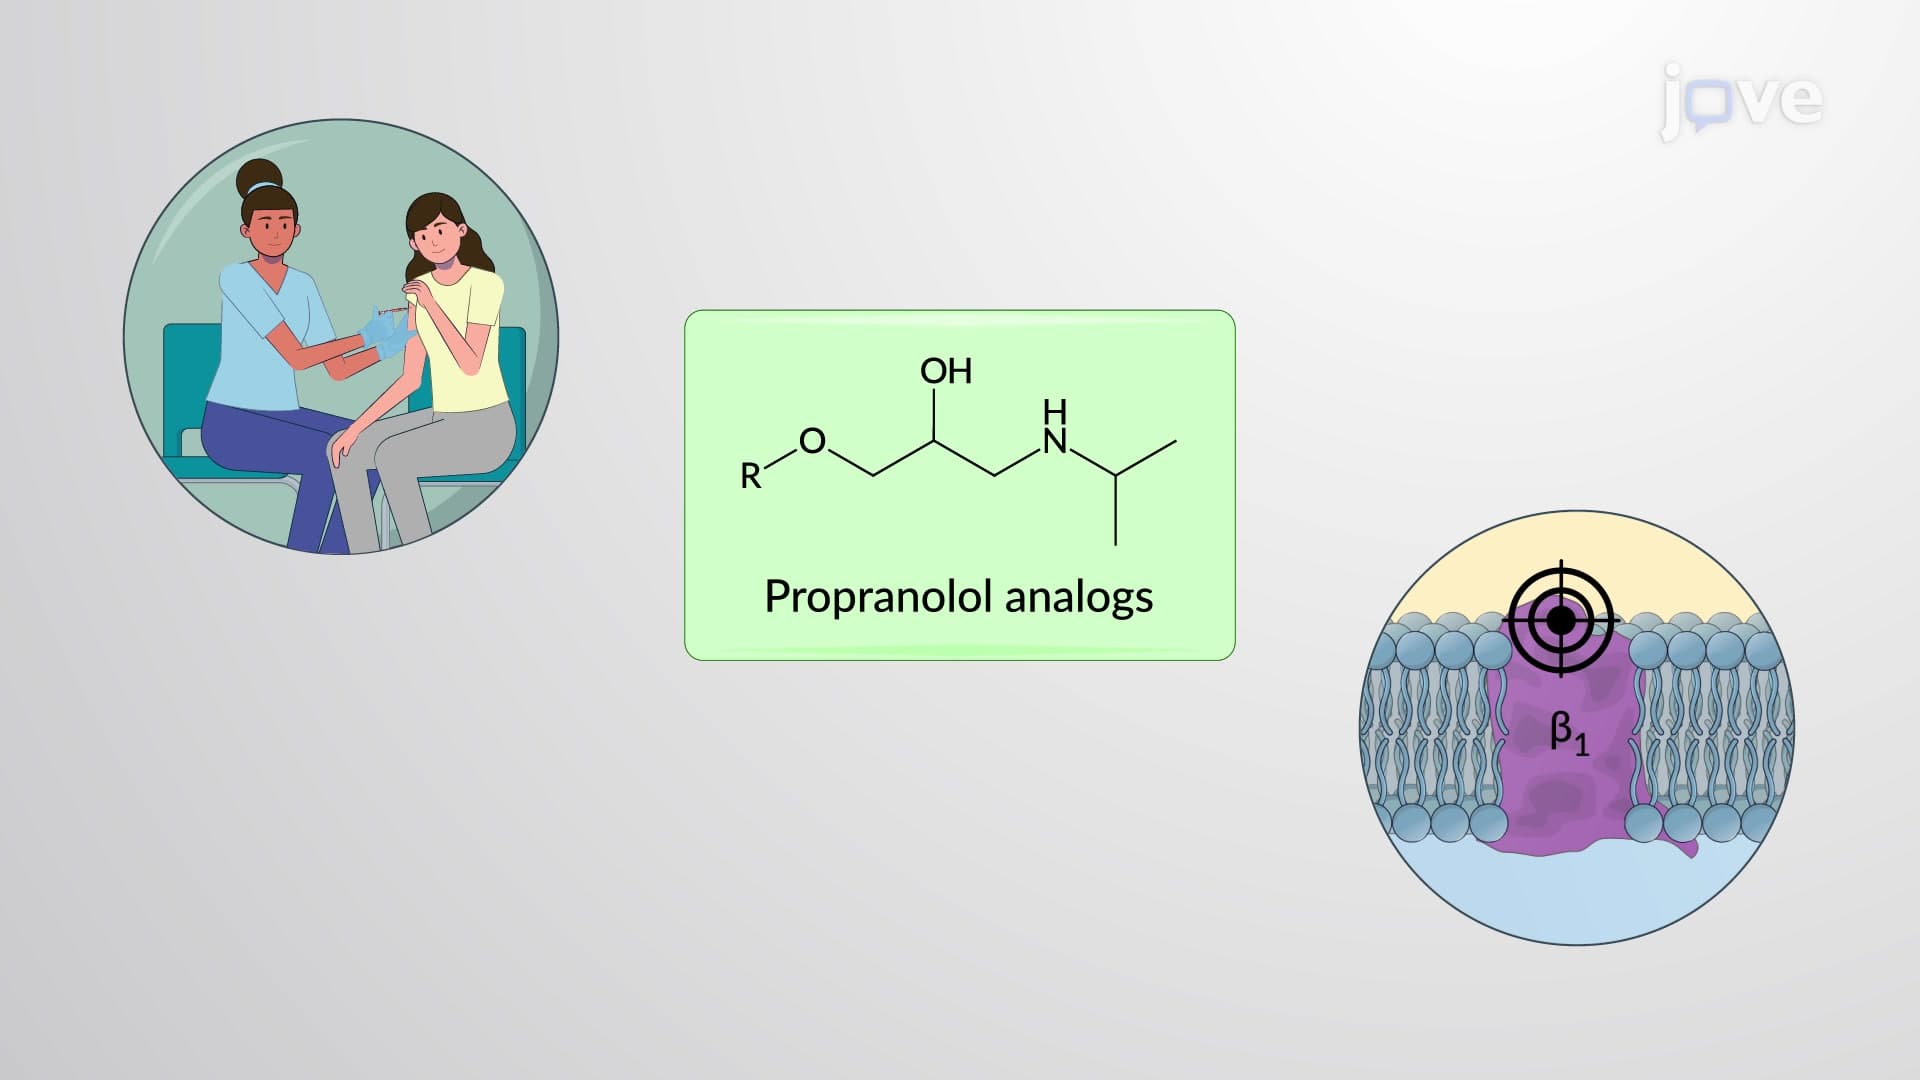
Adrenergic Antagonists: Chemistry and Classification of β-Receptor Blockers
β-adrenergic antagonists, or β-blockers, modulate the sympathetic nervous system by targeting β-adrenoceptors and inhibiting catecholamine-mediated sympathetic responses. β-blockers differ in their adrenoceptor subtype affinity, lipophilicity, and α-blocking capabilities. The history of β-blocker development began with the prototype, dichloroisoprenaline, which exhibited partial agonist activity. As a result, propranolol was developed as a pure antagonist but nonselective agent, paving the way...
 01:27
Adrenergic Antagonists: Pharmacological Actions of β-Receptor Blockers
β-receptor blockers significantly impact the cardiovascular system by counteracting catecholamine-induced sympathetic responses. These medications decrease heart rate, contractility, and cardiac output, potentially leading to cardiac depression, life-threatening bradycardia, and death. Therapeutically, β-blockers function as mild antihypertensives and are utilized in treating angina pectoris and cardiac arrhythmias. However, nonselective β-blockers inhibit β2-receptors in bronchial smooth...
 01:17
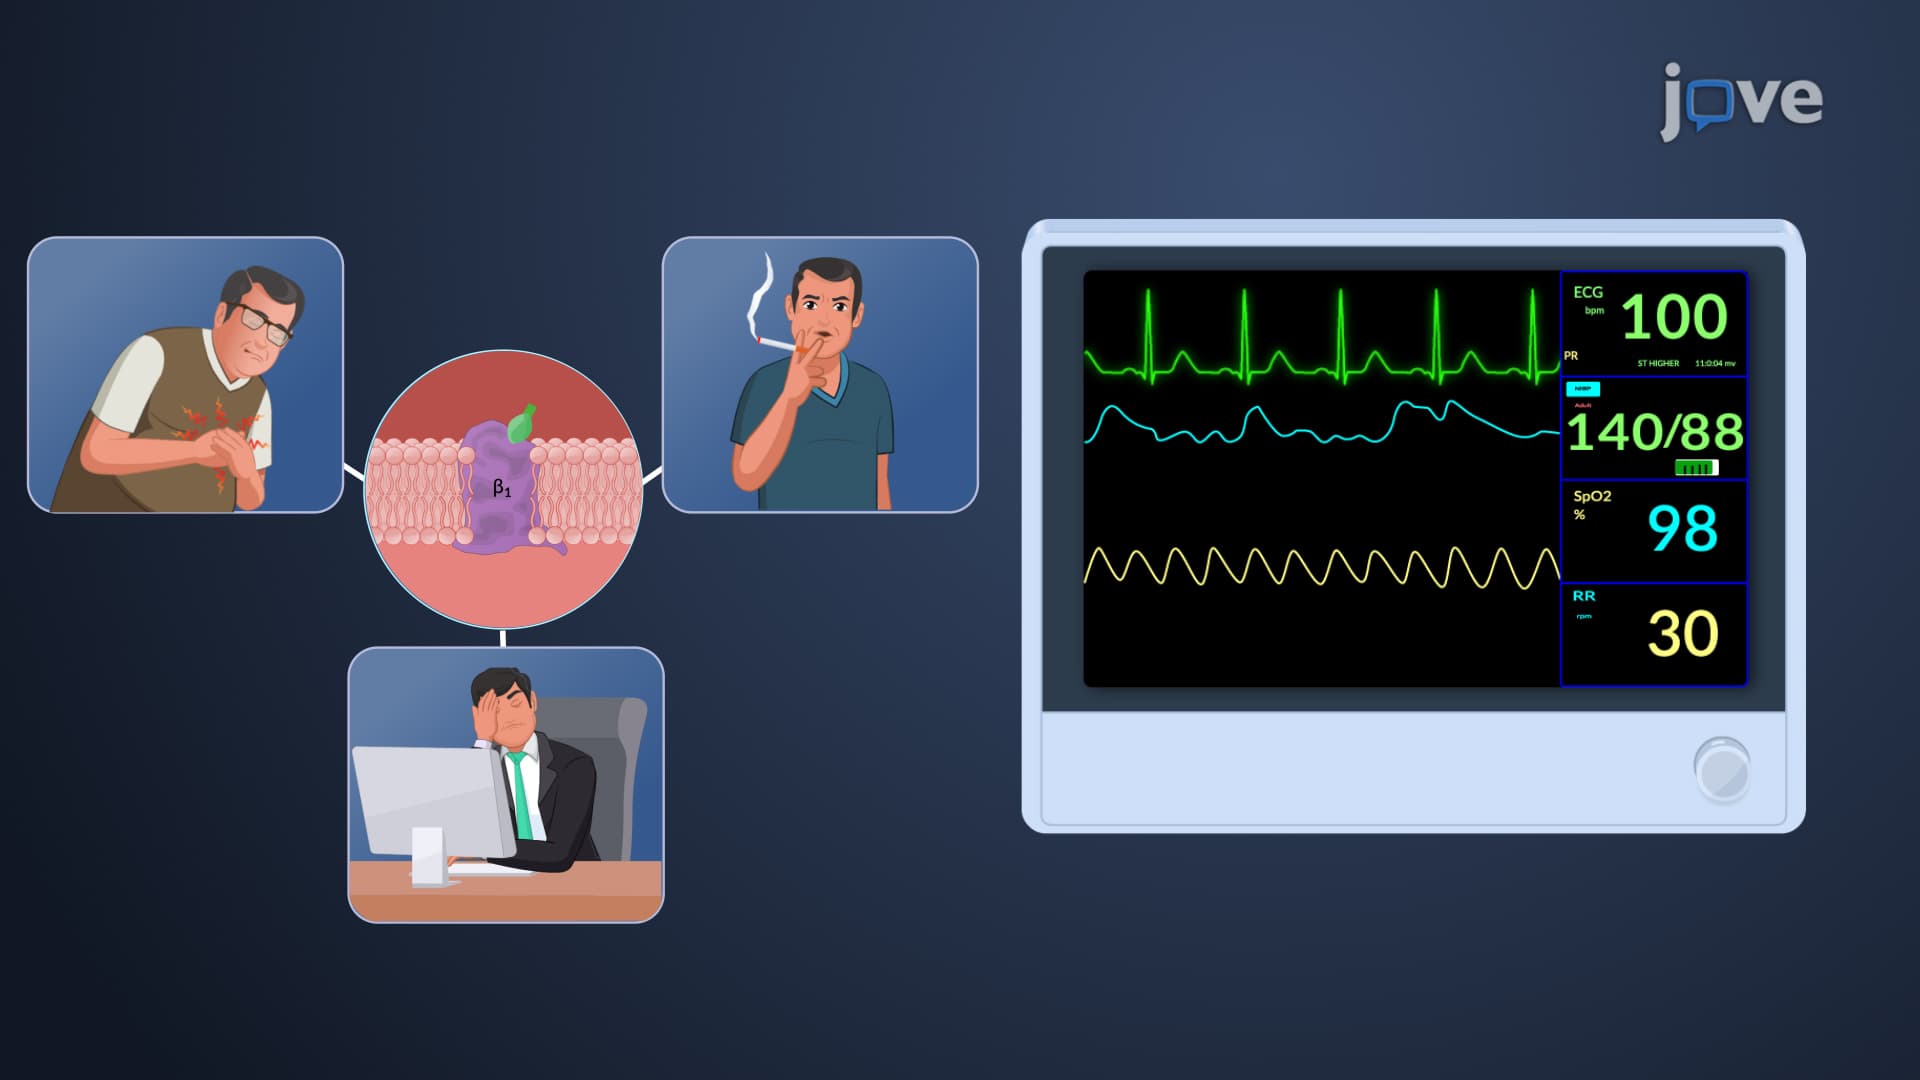
Antihypertensive Drugs: Action of β1 Blockers
β1-receptors are primarily located in the heart and kidneys. In cardiac myocytes, these receptors interact with neurotransmitters released by the sympathetic nervous system during heightened activity or danger. As a result, β1-receptors get activated, initiating a series of biochemical processes. Excessive activation of beta receptors due to chronic stress can abnormally increase heart rate and contractility, resulting in high blood pressure or hypertension. To counteract this, β1-blockers...
 01:28
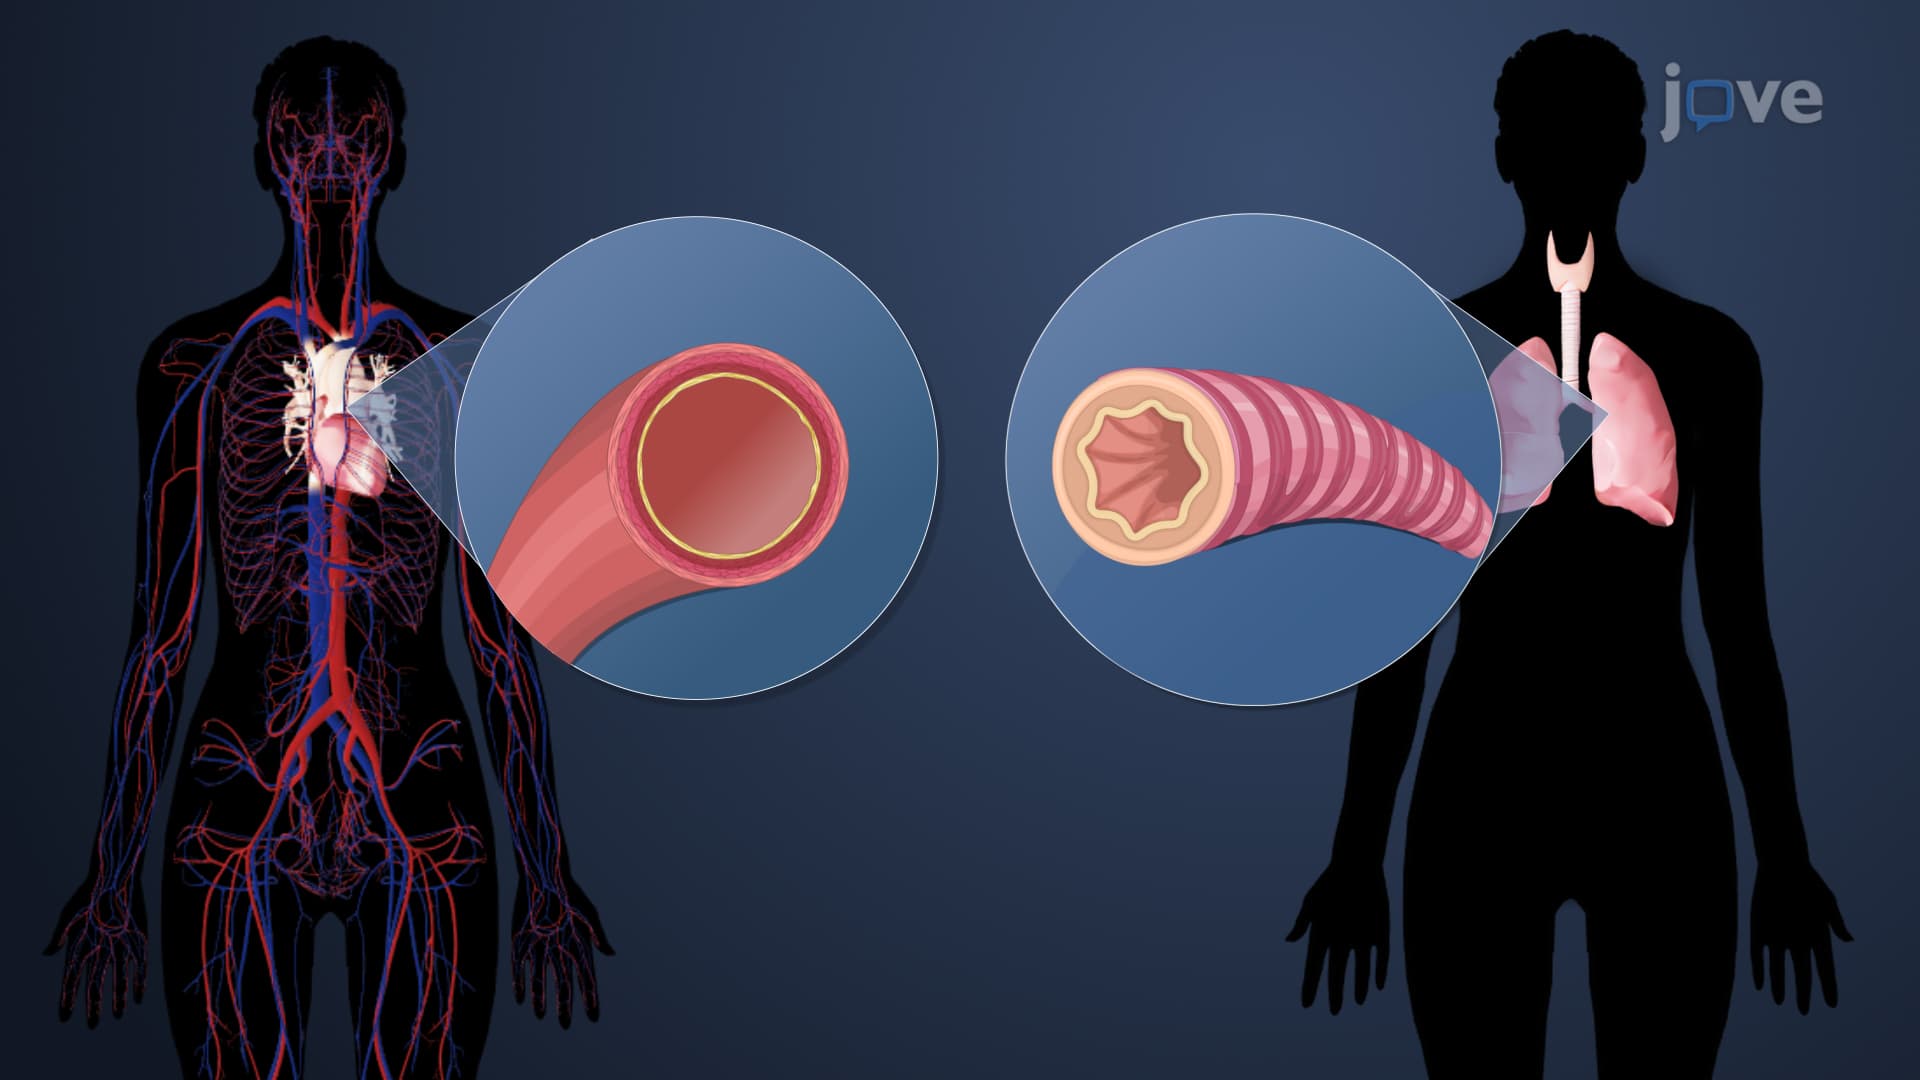
Antihypertensive Drugs: Types of β-Blockers
β receptors are classified into three subclasses: β1, β2, and β3. β1 receptors are primarily located in the heart and kidneys. When they get activated, they increase heart rate, contractility, and renin release. This process enhances blood pressure and aids in stress management. In contrast, β2 receptors are situated mainly in the lungs, blood vessels, and skeletal muscles. Upon activation, they trigger smooth muscle relaxation, causing bronchodilation and vasodilation. This widens airways and...
 01:24
Antiarrhythmic Drugs: Class II Agents as β-Adrenergic Blockers
Adrenergic stimulation generally impacts cardiac rate and rhythm. Specifically, stimulation of the β-adrenoceptors triggers an increase in intracellular calcium ion influx and pacemaker currents, which may cause arrhythmias. Catecholamines like adrenaline also demonstrate β2-adrenoceptor-mediated hypokalemia, impacting cardiac action potential and disrupting the normal cardiac rhythm. Class II antiarrhythmic drugs are β-adrenoceptor antagonists or β-blockers, which indirectly block calcium...