
認知症のリスクのある高齢者における楽器演奏と灰色の物質の関連性:全脳VBM分析
Nicole Espinosa1,2,3, Marshall A Dalton1, Hannes Almgren2,4
1School of Psychology, Faculty of Science, University of Sydney, Sydney, NSW, Australia.
GeroScience
|September 3, 2025

まとめ
終身の楽器演奏は 認知症のリスクのある高齢者の 灰色の質の密度の増加と関連しています この脳への利点は 活発なプレーヤーで観察され
科学分野:
- 神経科学
- 神経イメージング
- 認知の老化
背景:
- プロのミュージシャンは 音楽の訓練に伴う神経可塑性を示しています
- プロではないミュージシャンの脳健康に 生涯に渡る音楽経験が与える影響は 十分に理解されていません
- 認知症のリスクのある高齢者は 音楽のような認知的介入から恩恵を受けます
研究 の 目的:
- 終身の楽器演奏が認知症のリスクのある高齢者の灰色の質 (GM) 密度の変化と関連しているかどうかを調査する.
- この集団における音楽体験と神経心理学的機能の関係を調べる.
主な方法:
- 認知症のリスクのある61人の参加者 (年齢50歳以上) が,記憶クリニックから募集されました.
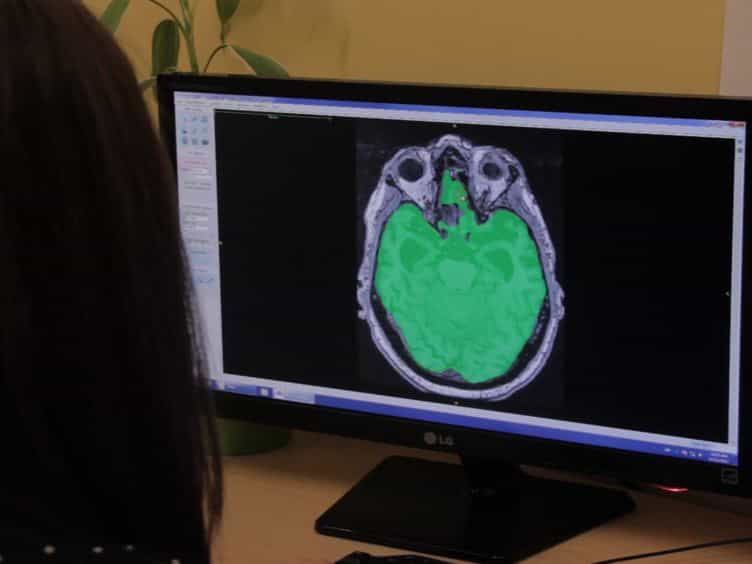
- 磁気共鳴画像 (MRI) と神経心理学的評価は,GM密度と認知機能 (学習,記憶,実行機能) を測定するために使用されました.
- 参加者は音楽の歴史に基づいて 活発な演奏者,元演奏者,無知なグループに分けられました 分析には,ヴォクセルベースの形態測定と一般的な線形モデルを使用した.
主要な成果:
- アクティブな音楽プレーヤーは,先行者グループと比較して,左側プラナム・テンポラール,左側プラナム・ポラール,右側後部インスラ,そして左側小脳の外部を含む特定の脳領域におけるGM密度の有意な増加を示した.
- 活動的なプレーヤーは,元プレーヤーと比較して,左小脳外側でより高いGM密度を示しました.
- 遺伝子組み換え物質の密度において,以前参加したグループと,以前参加したグループとの間に有意な差は認められませんでした. 音楽経験は神経心理学的パフォーマンスと有意に関連しませんでした.
結論:
- 音楽の訓練に伴う脳の領域の 遺伝子組み換え密度の増加と関連しています 認知症のリスクのある人でもそうです
- この発見は 活発な音楽の参加と 保存された脳構造の間の 関連性を示唆しています
- 脳の健康維持と 認知症予防戦略における 音楽の役割を 調べるにはさらなる研究が必要です
さらに関連する動画
関連する概念動画
 01:26
Alzheimer's Disease: Overview
1.7K
Alzheimer's Disease (AD) is a continually advancing neurodegenerative disorder, distinguished by escalating memory loss, cognitive dysfunction, and dementia. The disease unfolds in three stages: preclinical, mild cognitive impairment (MCI), and dementia. Its onset is insidious, and the progression gradual, with the cause not well explained by other disorders.
The clinical diagnosis of AD hinges on the presence of memory and other cognitive impairments. Biomarkers, such as changes in Aβ...
The clinical diagnosis of AD hinges on the presence of memory and other cognitive impairments. Biomarkers, such as changes in Aβ...
1.7K
 01:22
Alzheimer's Disease: Treatment
1.3K
Alzheimer's Disease (AD), a neurodegenerative disorder, is pathologically identified by amyloid plaques and neurofibrillary tangles composed of tau protein. AD pharmacotherapy aims to manage cognitive symptoms, delay disease progression, and treat behavioral symptoms. The treatment is primarily symptomatic and palliative, with no definitive disease-modifying therapy available. Cholinesterase inhibitors, including donepezil (Aricept), rivastigmine (Exelon), and galantamine (Razadyne), are...
1.3K
 01:29
Alzheimer Disease l: Introduction
29
Alzheimer disease is a chronic, progressive, and irreversible neurodegenerative disorder and the most common cause of dementia in older adults. It leads to gradual neuronal loss, causing cognitive decline, behavioral changes, and loss of functional independence.Risk Factors and EtiologyThe disease is multifactorial. Age is the strongest risk factor, with prevalence doubling every 5 years after age 65. Genetic factors include mutations in genes such as APP, PSEN1, and PSEN2, which are associated...
29
 01:23
Alzheimer Disease ll: Pathophysiology
42
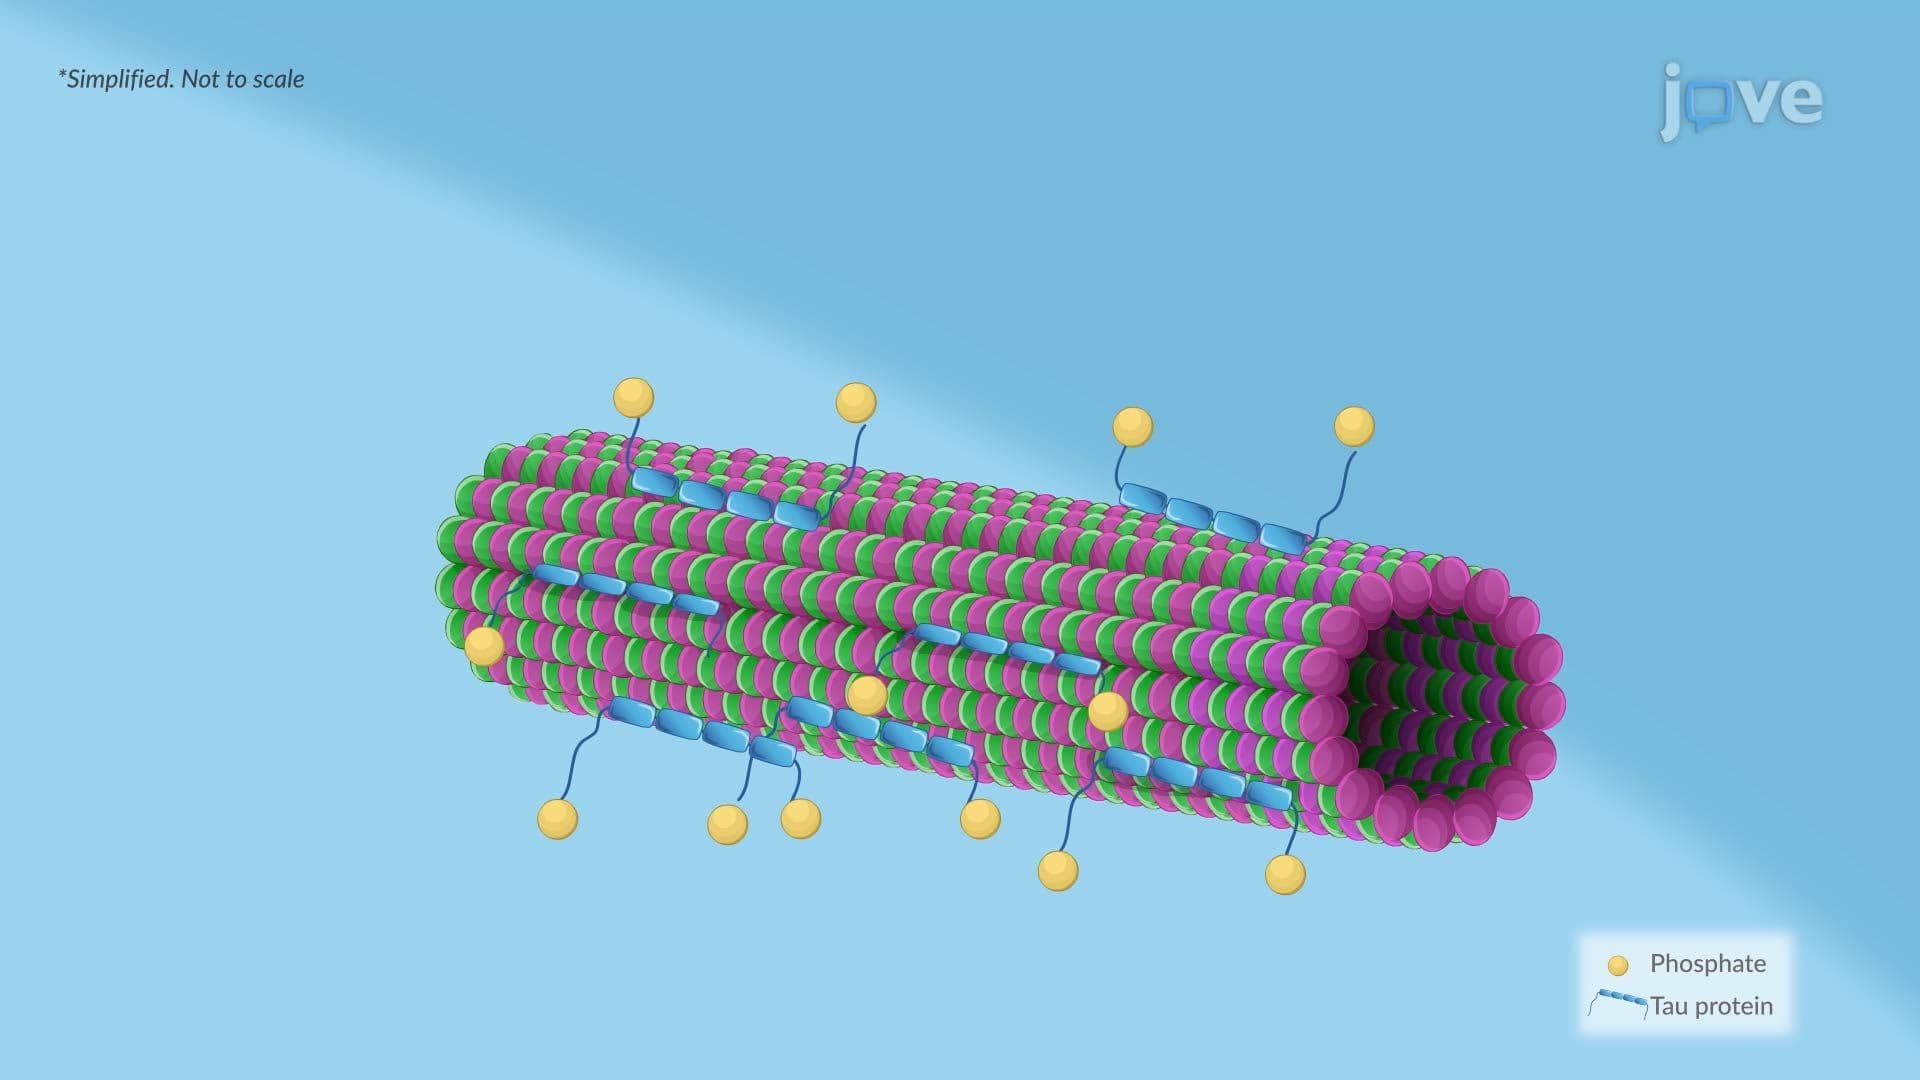
Alzheimer disease involves structural changes in the brain that begin long before symptoms appear. The most distinctive features are extracellular neuritic plaques and intracellular neurofibrillary tangles.Neuritic plaques form in the cerebral cortex and around blood vessels. These plaques contain a dense core of beta-amyloid (Aβ)—a toxic protein fragment that clumps outside neurons. The core is surrounded by damaged neuronal extensions, as well as reactive astrocytes and...
42
 01:22
Dementia l: Introduction
35
Dementia is an acquired, progressive syndrome characterized by a decline in multiple cognitive domains severe enough to impair daily functioning and reduce independence. Although memory loss is a central feature, the diagnosis requires additional deficits involving language, executive function, visuospatial skills, judgment, calculation, or abstract reasoning. These cognitive impairments reflect underlying neurodegenerative or vascular processes that gradually disrupt neuronal networks...
35