関連する実験動画
Updated: May 9, 2026

07:49

Measuring Local Anaphylaxis in Mice
Published on: October 14, 2014
19.5K
小児のコファクター強化食品アナフィラキシー:疫学,病理生理学,および臨床現象の記述的レビュー
Alpana Mohta1, Emilio Narvaez2, Patricia Mir-Ihara2,3,4
1Department of Dermatology, Venerology and Leprosy, Sharda Multispeciality Clinic, Bikaner, India.

まとめ
小児におけるコファクター強化食物アレルギー (CEFA) は,運動や感染症などの要因によって悪化する食物アレルギーです. 低診断は一般的であり,よりよい認識と研究が必要であることを強調しています.
科学分野:
- 小児アレルギーと免疫学
- アナフィラキシー 研究
- 免疫学
背景:
- 運動やNSAIDのような共同因子はアレルギー反応を強め,重度のアナフィラキシーを引き起こす可能性があります.
- 以前に様々な用語で説明された,コファクター強化食品アレルギー (CEFA) は,統一的な概念です.
- 小児のコファクター強化食物アナフィラキシー (PCEFA) は,コファクターが食物アレルギーを著しく悪化させる深刻な状態である.
研究 の 目的:
- 小児におけるコファクター強化食物アナフィラキシー (PCEFA) の現在の理解をレビューする.
- PCEFAの有病率,一般的な共因体,および主たるアレルゲンを強調する.
- 診断の課題と小児科でのさらなる研究の必要性について議論する.
主な方法:
- コファクター強化食品アナフィラキシーの小児症例に焦点を当てた文献レビュー.
- 小児アナフィラキシーにおける文書化された共因体とアレルゲンの分析.
- 診断基準と誤診パターンの議論
主要な成果:
- コファクターは,小児の食物アナフィラキシー症例の14%から18.3%に存在し,運動と感染症が最も一般的です.
- オメガ5グリアジンはPCEFAの主なアレルゲンです.
- PCEFAはしばしばイディオパシー性アナフィラキシー,運動誘発性アナフィラキシー,または喘息として誤診されます.
結論:
- PCEFAは変異性があるため 診断が不十分です
- 現在の研究は主に成人に焦点を当てており,小児に特化した研究が必要である.
- PCEFAの管理には,診断の精度と標的治療戦略の改善が不可欠です.


関連する概念動画
 02:06
Allergic Reactions
Overview
 01:26
Pharmacokinetics: Drug–Food and Drug–Viral Interactions
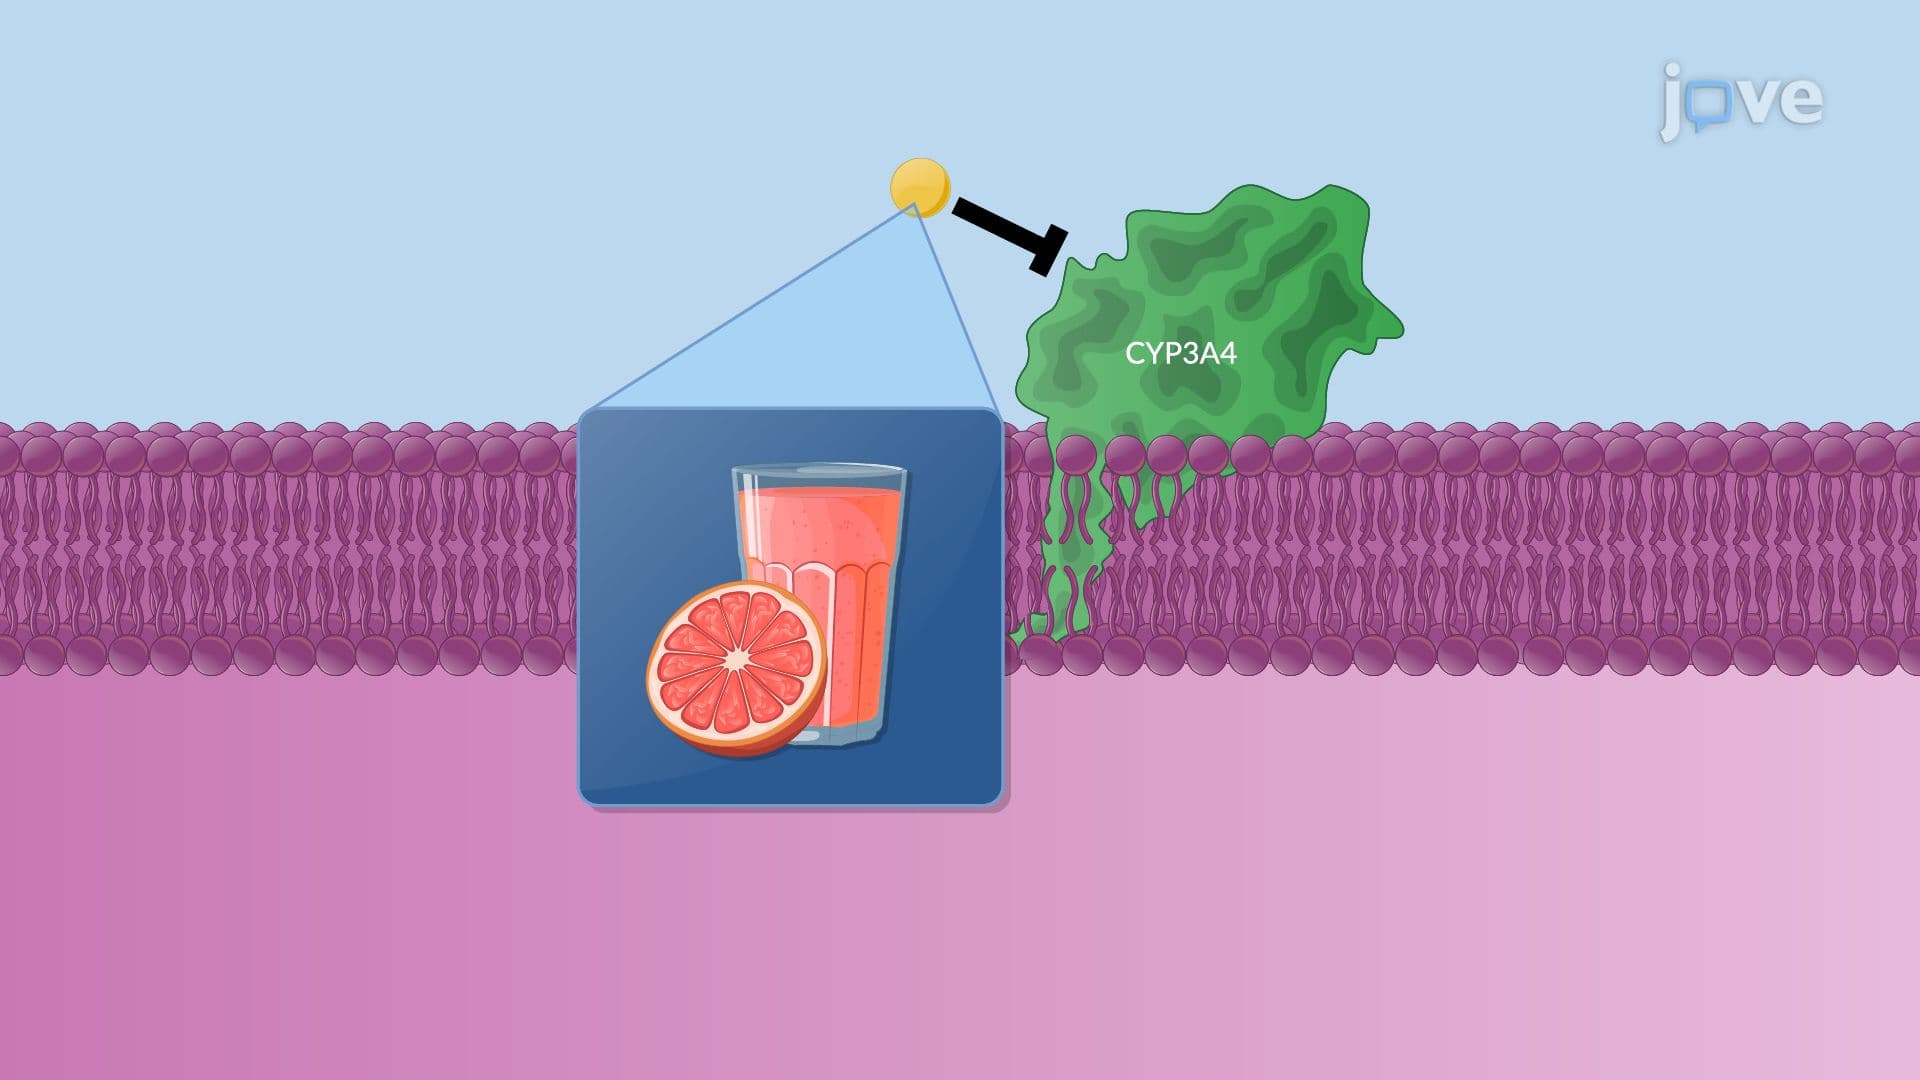
A drug interaction occurs when the concurrent use of another drug, food, or an external substance alters the pharmacological activity of a drug. This interaction can modify the action of the original drug, affecting its effectiveness and safety.Drug–food interactions are significant as they impact drug absorption, metabolism, and excretion. For example, grapefruit juice is a well-known disruptor of drug metabolism. It inhibits the cytochrome P450 3A4 enzyme, crucial for the metabolism of many...
 01:23
Pharmacokinetics in Pediatric Patients: Overview and Drug Absorption
Understanding the physiological differences in the pediatric population is crucial for effective pharmacotherapy. Neonates, infants, and children exhibit significant variations in gastric pH, gastric emptying time, intestinal transit time, and biliary function. These variations profoundly affect oral drug absorption, necessitating a nuanced approach to pediatric dosing.Neonates present with a unique physiological profile, having a gastric pH greater than 4 and faster and more irregular gastric...
 01:24
Pharmacokinetics in Pediatric Patients: Drug Metabolism
In pediatric care, understanding the nuances of hepatic drug metabolism is crucial, as it significantly differs from that of adults. This divergence is primarily due to the developmental stage of drug-metabolizing enzymes, which affects how medications are processed in the body. In neonates, for instance, the activity of Phase I enzymes—critical for the initial breakdown of drugs—is markedly reduced, functioning at just 20–40% of the levels seen in adults. This reduction poses a challenge in...
 01:30
Allergic Reactions: Anaphylaxis
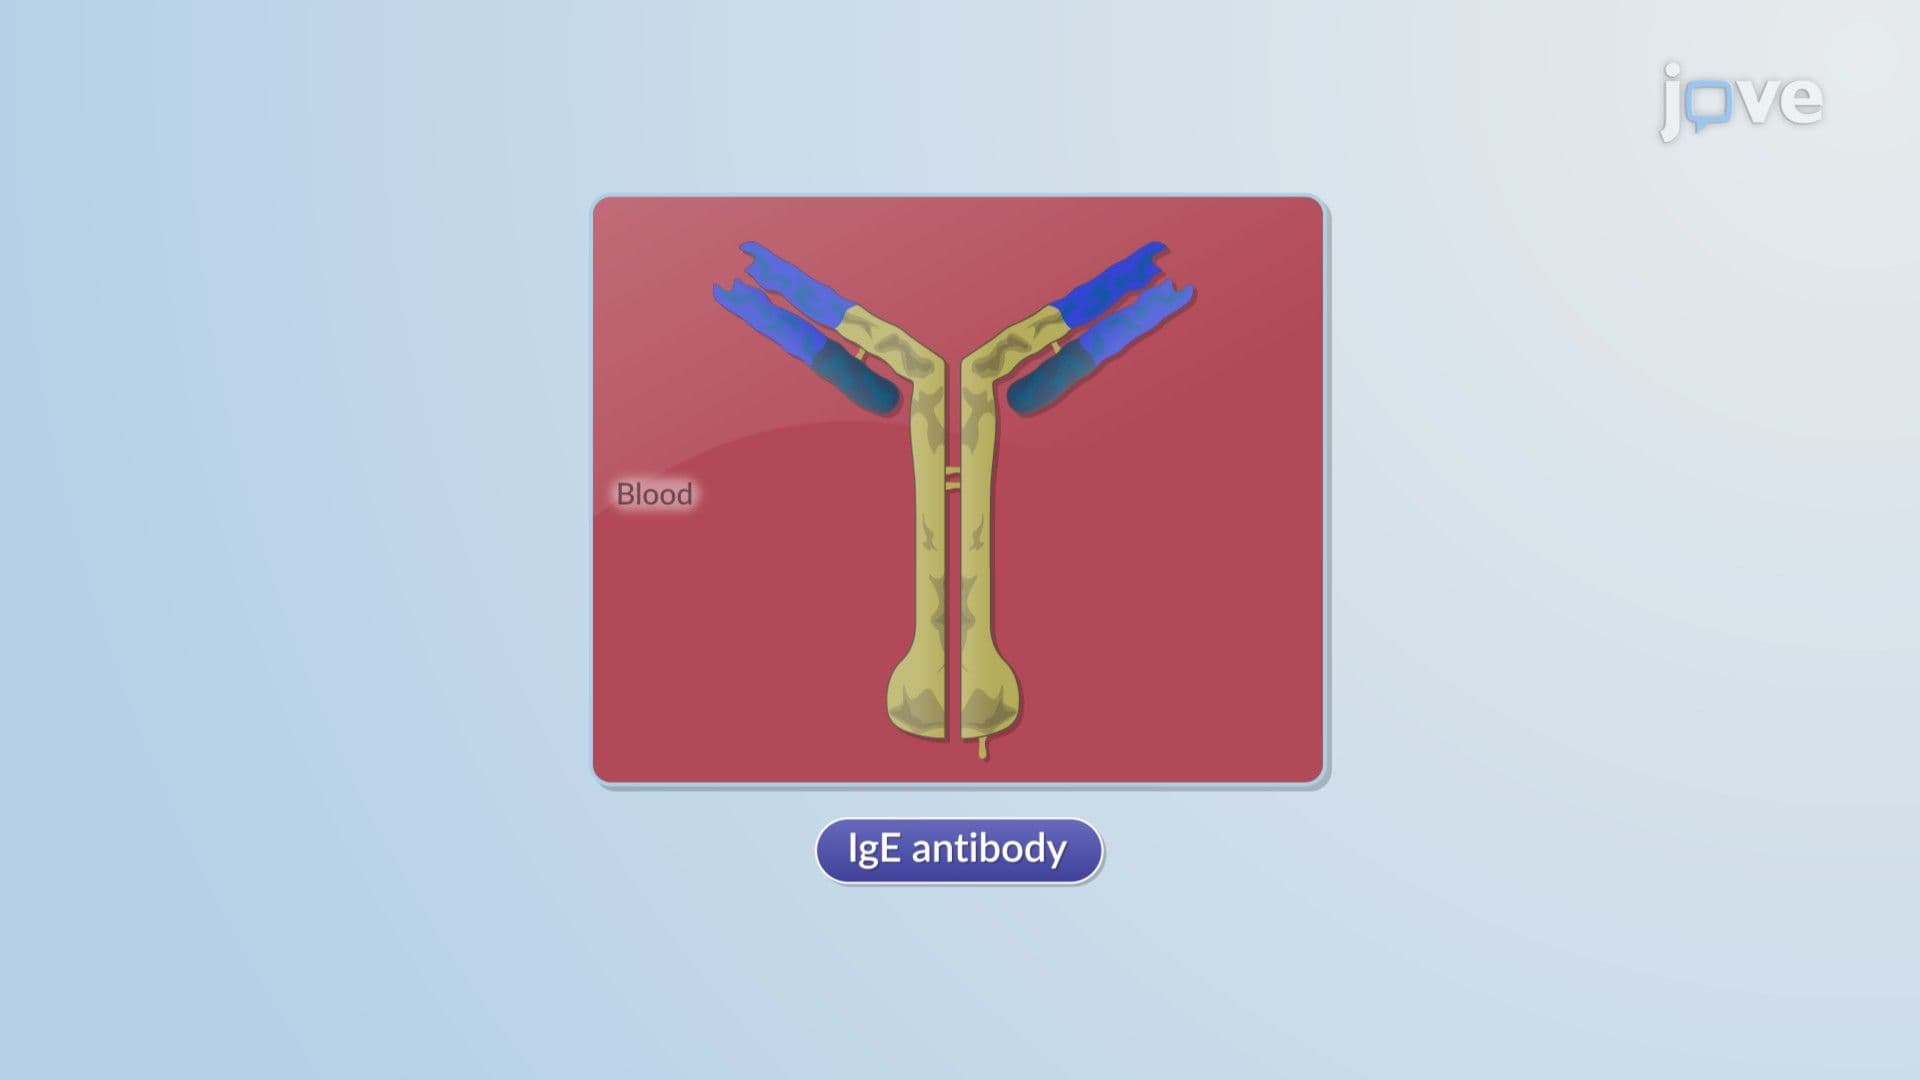
Anaphylaxis is a severe, life-threatening hypersensitivity reaction mediated by Immunoglobulin E (IgE) antibodies. When IgE binds to allergens, it triggers the release of mediators– histamine, leukotrienes, and prostaglandins from mast cells and basophils. These mediators cause vasodilation, edema, and inflammation, leading to various symptoms.The primary allergens causing anaphylaxis include food items (e.g., peanuts, shellfish), drugs (e.g., penicillin, asparaginase, corticotropin, heparin),...
 01:26
Pharmaceutical Poisoning: Treatment Strategies
Treatment strategies for poisoning are a critical aspect of emergency medicine, focusing on preventing the absorption of toxins and enhancing their elimination. When a poisoning incident occurs, the first response is to halt exposure and decontaminate the patient, particularly through gastrointestinal (GI) methods if the poison was ingested.Gastrointestinal Decontamination Techniques:Activated charcoal is the cornerstone of GI decontamination. It works through adsorption, binding the toxin to...