
タンパク質C欠損症患者におけるタンパク質C濃縮製剤の皮下投与を支持する薬物動態学的エビデンス
Zhaoyang Li1, Inmaculada C Sorribes2, Jennifer Schneider2
1Takeda Development Center Americas, Inc., Cambridge, Massachusetts, United States.

Background:
Protein C concentrate (Ceprotin®; Baxalta US Inc., a Takeda company, Cambridge, MA; Takeda Manufacturing Austria AG, Vienna, Austria) is approved for intravenous (IV) use in severe congenital protein C deficiency (SCPCD), with pharmacokinetic (PK)-guided dosing. Subcutaneous (SC) administration may reduce treatment burden, especially for pediatric and neonatal patients; however, the use of SC protein C concentrate has so far been empirical, and PK data are required to support dose optimization.
Objectives:
This study aimed to characterize the population PK (PopPK) of SC protein C concentrate in patients with SCPCD.
Methods:
A PopPK model was developed for SC protein C concentrate, based on a previously developed model for IV administration. Simulations were conducted across eight three-stage dosing scenarios that patterned the IV dosing regimens in the U.S. product label (initial dose [stage 1]: 60-120 IU/kg; subsequent three doses [stage 2]: 60-80 IU/kg every 6 hours; maintenance dose [stage 3]: 45-120 IU/kg every 12 hours). Additional simulations were performed across six one-stage dosing scenarios that were based on dosing reported in clinical practice (50-60 IU/kg every 12 hours, 200-350 IU/kg every 48 hours). Target maximum ( C max ) and trough ( C trough ) concentration levels used as references were 100 IU/dL and 25 IU/dL, respectively.
Results:
The dataset included 86 observations from 13 patients with SCPCD receiving SC protein C concentrate. Model-based simulations predicted that, after the first dose, 6-9% and 5-45% of patients in the three- and one-stage dosing scenarios, respectively, would attain C max >100 IU/dL. At steady state, ≥83% of patients were predicted to attain C trough >25 IU/dL for all scenarios. In three-stage dosing scenarios, while initial (stage 1 [dose 1]) and subsequent doses (stage 2 [doses 2-4]) determined speed to steady state, exposure at steady state was driven by the maintenance dose (stage 3 [dose 5 onwards]).
Conclusions:
The PopPK model was robust and described SC protein C concentrate PK data well. Evidence provided by model-based simulations supports the use of various SC dosing regimens across age groups in acute or prophylactic settings according to the intended protein C activity levels. A high loading dose may be required to rapidly attain target therapeutic concentrations.
関連する概念動画
 01:09
Hepatic Drug Clearance: Effect of Protein Binding
For low-extraction-ratio drugs that are less than 80% protein-bound, minor changes in protein binding...
 01:22
Nonlinear Pharmacokinetics: Bioavailability and Protein-Drug Binding
To quantify the extent of bioavailability, pharmacologists often use a parameter called .
 01:16
Protein-Drug Binding: Mechanism and Kinetics
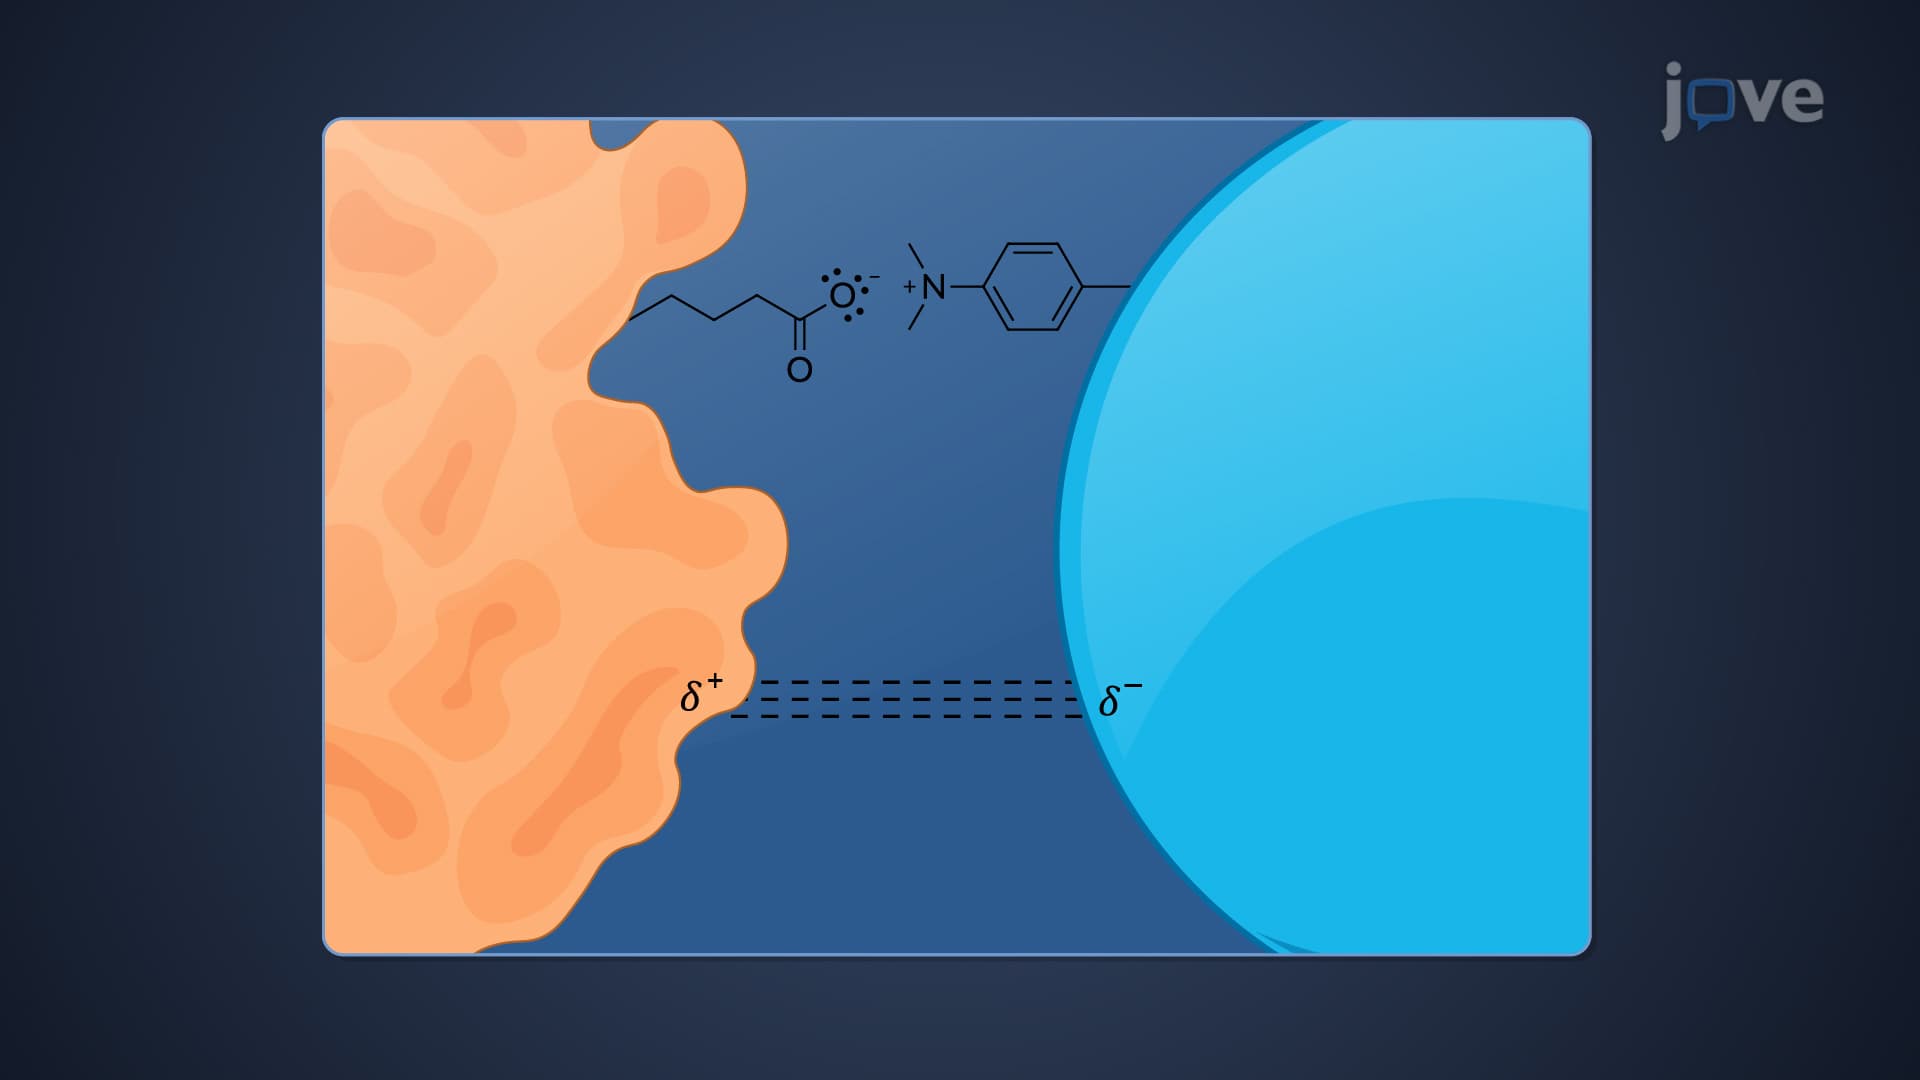
Various forces drive these interactions, including hydrogen bonds, hydrophobic interactions, ionic bonds, electrostatic interactions, and van der Waals forces. These bonds enable drugs to bind to specific sites on proteins,...
 01:23
Drug Concentrations: Measurements
Plasma...
 01:13
Physiological Pharmacokinetic Models: Assumption with Protein Binding
 01:29
Drug Distribution: Plasma Protein Binding