関連する実験動画
Updated: Jul 8, 2026
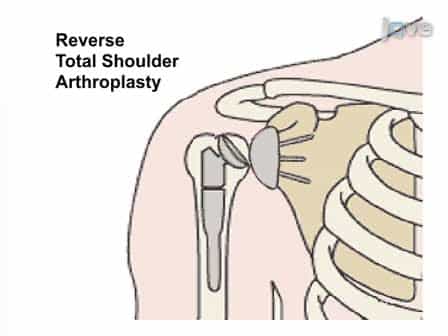
Reverse Total Shoulder Arthroplasty
Published on: July 5, 2011
後方肩関節不安定症:症例シリーズにおける提示と治療成績のスペクトラム
Sandeep Damaraju1, Austin R Gomindes1, Dylan Mistry1
1Trauma and Orthopedics, University Hospitals Birmingham NHS Foundation Trust, Birmingham, GBR.

Abstract:
Posterior shoulder dislocation is an uncommon condition, accounting for a minority of shoulder instability cases. It is more frequently encountered in high-level athletes and is often missed at initial presentation, which can lead to chronic instability and recurrent dislocations. Predisposing factors include congenital anatomical variations, capsular laxity, and acquired injuries such as trauma or tetanic muscle contractions during seizures or electrical shocks. Management strategies are broadly divided into conservative and surgical approaches. Nonoperative treatment focuses on strengthening the periscapular and rotator cuff musculature but has limited success in traumatic cases and in athletic patients, where long-term instability is more likely. Surgical options aim to address the underlying pathology and may be performed using open or arthroscopic techniques. Soft tissue procedures include labral repair and capsular plication, whereas bony procedures may involve corrective osteotomies in cases of congenital abnormalities or bone grafting to address reverse Hill-Sachs lesions resulting from humeral head impaction on the glenoid. We present a three-case series of posterior shoulder dislocations managed at a teaching hospital in the United Kingdom. This series highlights the spectrum of posterior shoulder instability, the multidisciplinary approach required, and the outcomes achieved with differing management strategies.
さらに関連する動画


関連する概念動画
 01:22
Mitral Valve Prolapse II: Assessment and Management
 01:23
Mitral Stenosis II: Clinical features and Diagnostic Tests
 01:25
Aortic Regurgitation III: Medical Management
 01:25
Dysrhythmias VII: Nursing Management of Dysrhythmias
 01:21
Aneurysm II: Clinical Manifestations and Diagnostic Studies
 01:12
Alterations in Muscle Tone ll