
高調性骨盤底機能障害のデータ駆動型診断と臨床的特徴
Sara R Till1, Andrew Schrepf2, Anne Arewasikporn2
1Department of Obstetrics and Gynecology, University of Michigan, 1500 E. Medical Center Dr. Ann Arbor, MI 48109.

Background:
Despite widespread agreement that high tone pelvic floor dysfunction (HTPFD) is highly prevalent among women with pelvic pain, there is no consensus regarding standardized assessment strategy or diagnostic criteria. Furthermore, there is scant primary data regarding clinical presentation of HTPFD and most existing literature related to symptoms is based on expert opinion rather than patient-reported data. The lack of consensus in diagnostic assessment and data regarding clinical presentation associated with this condition creates substantial barriers to improving clinical identification and evaluating efficacy of treatment strategies.
Objective:
To identify a pelvic myofascial tenderness score that corresponded to patient-reported reproduction of pain and to compare clinical presentation of patients with and without HTPFD.
Study Design:
Cross-sectional study of 612 patients presenting to a chronic pelvic pain referral center from July 2019 to January 2023. Patients complete comprehensive questionnaires prior to first visit and undergo standardized physical examination, including palpation of six pelvic muscle sites (bilateral pubococcygeus, iliococcygeus, obturator internus) at first visit. Receiver operating characteristic (ROC) curve analyses were performed to identify a pelvic myofascial tenderness score that corresponded to patient-reported pain reproduction on palpation of pelvic floor muscles. Comparative analyses were performed to explore differences in clinical presentation associated with HTPFD.
Results:
Summative score of >12/60 on palpation of pelvic floor muscles demonstrated good accuracy by ROC analyses (sensitivity 82.3%; specificity 79.1) for patient-reported pain reproduction and compared favorably to previously used methods for classifying HTPFD. Using >12/60 tenderness score as diagnostic threshold for HTPFD, 389 (63.6%) patients were categorized as having HTPFD and 223 (36.4%) as no HTPFD. Compared to patients without HTPFD, those with HTPFD were more likely to experience persistent pain with at least 14 pain days per month (odds ratio [OR] 2.32, 95% confidence interval [CI] 1.60, 3.35, p<.001). They were more likely to report pain exacerbation with physical activity, including exercise (OR 1.69, 95% CI 1.21, 2.32, p=.002) and walking (OR 1.85, 95% CI 1.32, 2.60, p<.001). Patients with HTPFD were more likely to describe pain as "heavy feeling in the pelvis" and report that pain radiated to other body regions and was associated with nausea and vomiting (all p<.001). Patients with HTPFD reported significant worse sexual function with more severe and consistent dyspareunia, pain occurring during and continuing 24 hours following intercourse, and were more likely to interrupt or avoid intercourse due to pain (all p<.001).
Conclusion:
HTPFD should be considered when patients report summative tenderness of >12/60 on palpation of six pelvic floor muscles. HTPFD is associated with more persistent pain that may radiate to other body regions and is exacerbated by physical activity. Dyspareunia and impaired sexual function appear to be hallmark symptoms of HTPFD.
さらに関連する動画
 03:49
Anogenital Distance and Perineal Measurements of the Pelvic Organ Prolapse POP Quantification System
Published on: September 20, 2018
 07:20
Intraoperative Detection of Subtle Endometriosis: A Novel Paradigm for Detection and Treatment of Pelvic Pain Associated with the Loss of Peritoneal Integrity
Published on: December 21, 2012
関連する概念動画
 01:26
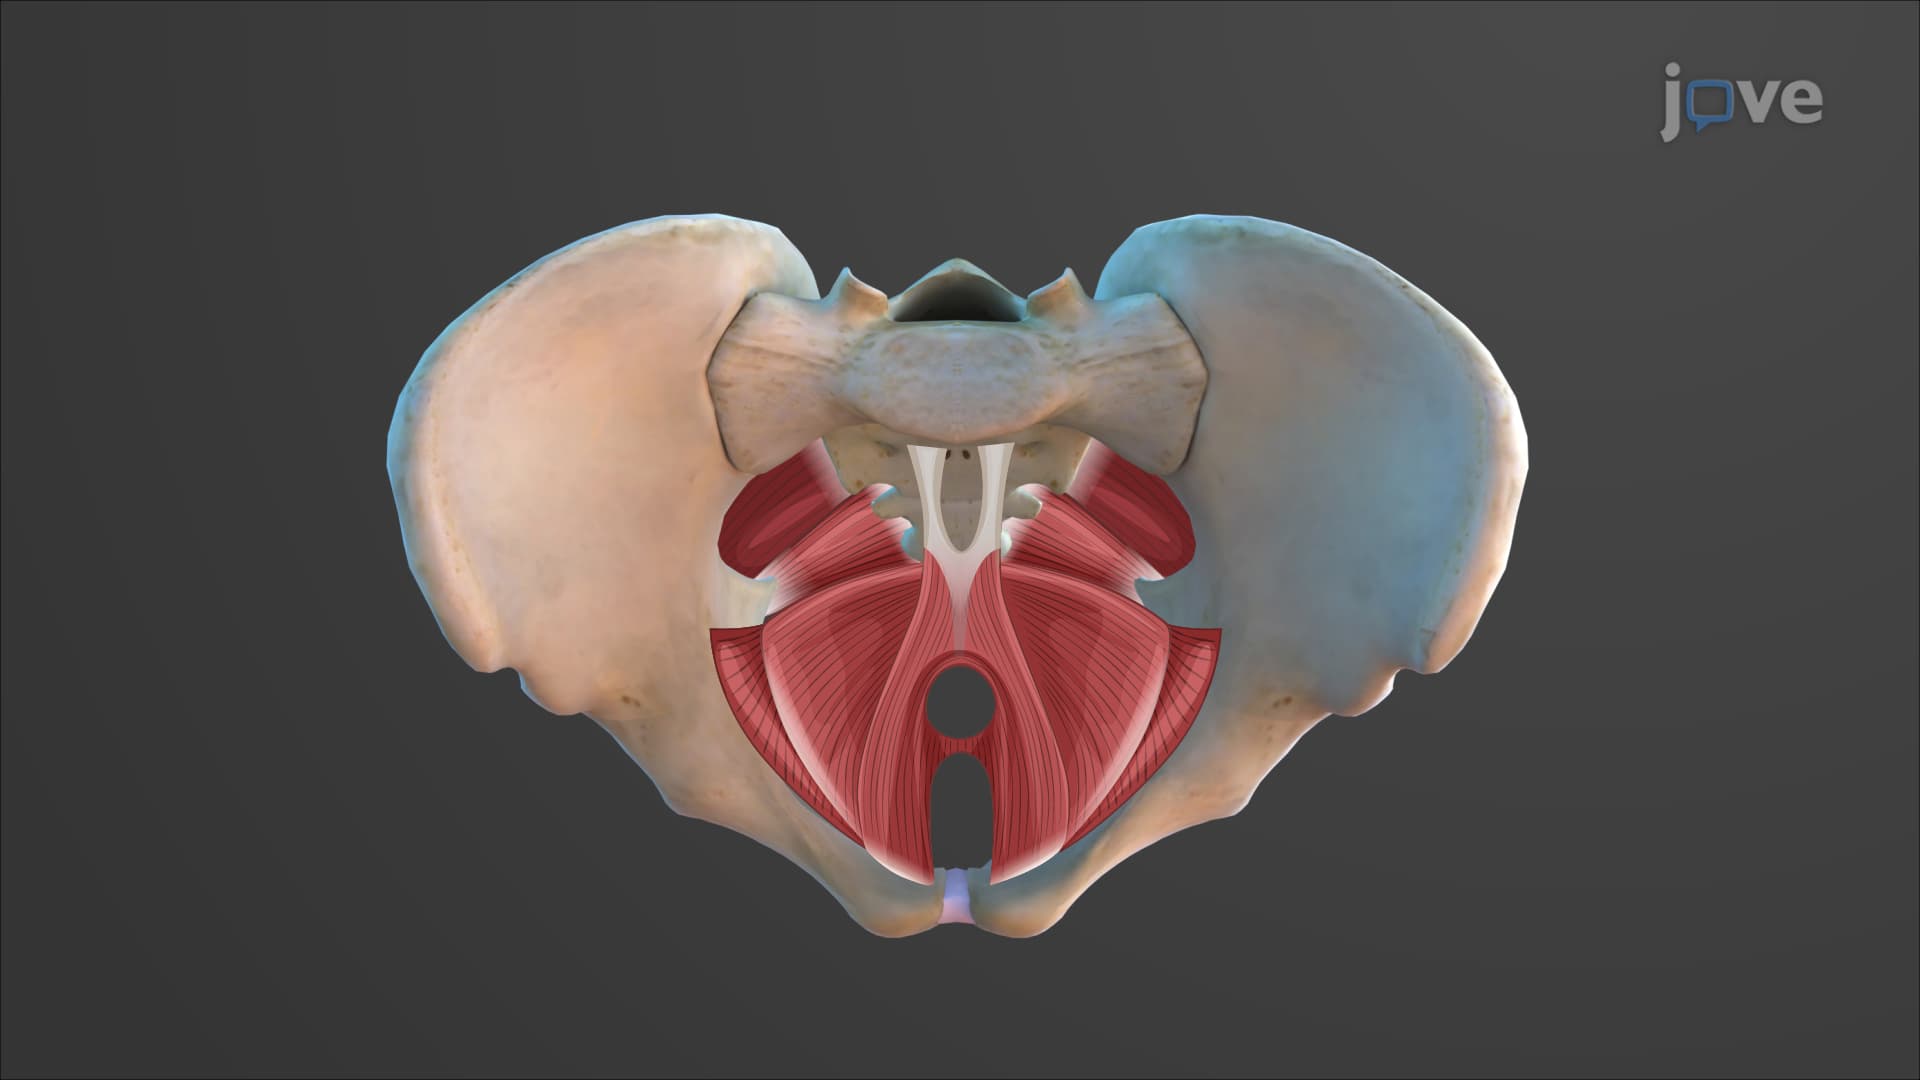
Muscles of the Pelvic Floor and Perineum
Perineal Layer
The perineum is a diamond-shaped area below the pelvic diaphragm, divided into an anterior urogenital triangle that contains the external genitals and a posterior anal triangle housing the anus. The urogenital...
 01:26
Urinary Tract Calculi II: Pathophysiology and Clinical Manifestations
 01:19
Urodynamic Studies: Uroflowmetry
 01:22
Imaging Studies VI: Voiding Cystourethrography and Cystography
 01:30
Irritable Bowel Syndrome II: Clinical Features and Diagnostic Evaluation
Irritable Bowel Syndrome (IBS) is classified into subtypes based on the predominant bowel habits as determined by the Bristol Stool Form Scale (BSFS). The subtypes are:
 01:23
Urinary Bladder
In males, the bladder is situated in front of the rectum, while in females, it is positioned anterior to the vagina and uterus. The bladder floor contains an inverted triangular area called the trigone, defined by the two ureteric...