鬱病は糖尿病性神経疾患に偽装したうつ病です
JAMA
|March 21, 1980

まとめ
この研究では,下肢における痛ましい糖尿病性神経病気が,しばしばうつ病の形態であることを発見しました. イミプラミンやアミトリプチリンなどの抗うつ薬は,患者の痛みとうつの両方を効果的に治療しました.
科学分野:
- 神経学 神経学とは
- 精神科医は精神病を患っている.
- 薬理学 薬理学とは
背景:
- 糖尿病性神経症は,糖尿病の一般的な合併症です.
- 痛ましい糖尿病性神経症は,患者の生活の質に大きな影響を与えます.
- うつ病はしばしば慢性疼痛状態と併発する.
研究 の 目的:
- 痛烈な糖尿病性神経症の患者のうつ病を評価するために.
- この状態に対する抗うつ剤の薬物療法の有効性を評価する.
主な方法:
- ダブルブラインドでコントロールされた研究が行われました.
- 疼痛性糖尿病性ニューロパシーを患った59人の患者が対象となった.
- 精神科のインタビューとクッファー・デトレテストのスコアは,うつ病の評価に使用されました.
- 治療には,イミプラミン水塩化物またはアミトリプチリン水塩化物が含まれていました.
主要な成果:
- すべての患者は実質的なうつ病を発症した.
- イミプラミンまたはアミトリプチリンによる治療は,10週間以内に下肢痛の完全な寛解をもたらしました.
- 同時にうつ病症状の緩和とうつ病テストスコアの正常化が見られた.
結論:
- 下肢の痛ましい糖尿病性神経症は,多くの場合,うつ病に相当します.
- イミプラミンとアミトリプチリンは,うつ病に関連した痛ましい糖尿病性神経疾患の効果的な治療法です.


関連する概念動画
 01:26
Type I Diabetes II: Pathophysiology
Type 1 diabetes mellitus arises from an immune-mediated destruction of pancreatic β-cells, resulting in an absolute deficiency of insulin. This process develops in genetically susceptible individuals when autoimmunity, environmental exposures, and immunologic dysregulation converge to trigger a targeted attack on the insulin-producing cells of the pancreas. The β-cells are located within the islets of Langerhans and are essential for regulating blood glucose by facilitating cellular uptake of...
 01:19
Type I Diabetes III: Clinical Manifestations
Type 1 diabetes mellitus typically presents with rapid-onset symptoms due to the body’s inability to utilize glucose in the absence of insulin. Since insulin is required for glucose uptake into cells, its deficiency leads to hyperglycemia and cellular energy deprivation, resulting in characteristic clinical features.Polyuria and PolydipsiaOne of the earliest, most prominent symptoms is polyuria (excessive urination). When blood glucose concentrations rise above the renal threshold, the kidneys...
 01:24
Type II Diabetes II: Pathophysiology
PathophysiologyType 2 diabetes mellitus (T2DM ) is a chronic metabolic disorder characterized by insulin resistance and progressive pancreatic β-cell dysfunction, leading to impaired glucose homeostasis. It results from interactions among genetic predisposition, environmental factors, and metabolic stressors, such as overnutrition and a sedentary lifestyle.Insulin Resistance and Glucose DysregulationEarly T2DM involves insulin resistance in skeletal muscle, adipose tissue, and the liver.
 01:25
Type II Diabetes Mellitus III: Clinical Manifestations and Diagnosis
Type 2 diabetes mellitus develops gradually and is often asymptomatic in early stages.Clinical ManifestationsWhen symptoms appear, they include fatigue, blurred vision, pruritus, delayed wound healing, and recurrent infections, particularly candidal infections. Peripheral neuropathy may present as numbness or tingling in the extremities. Classic hyperglycemia symptoms—polyuria, polydipsia, and polyphagia—are less common. Most patients are overweight and frequently have associated hypertension...
 01:31
Diabetic Foot Ulcer
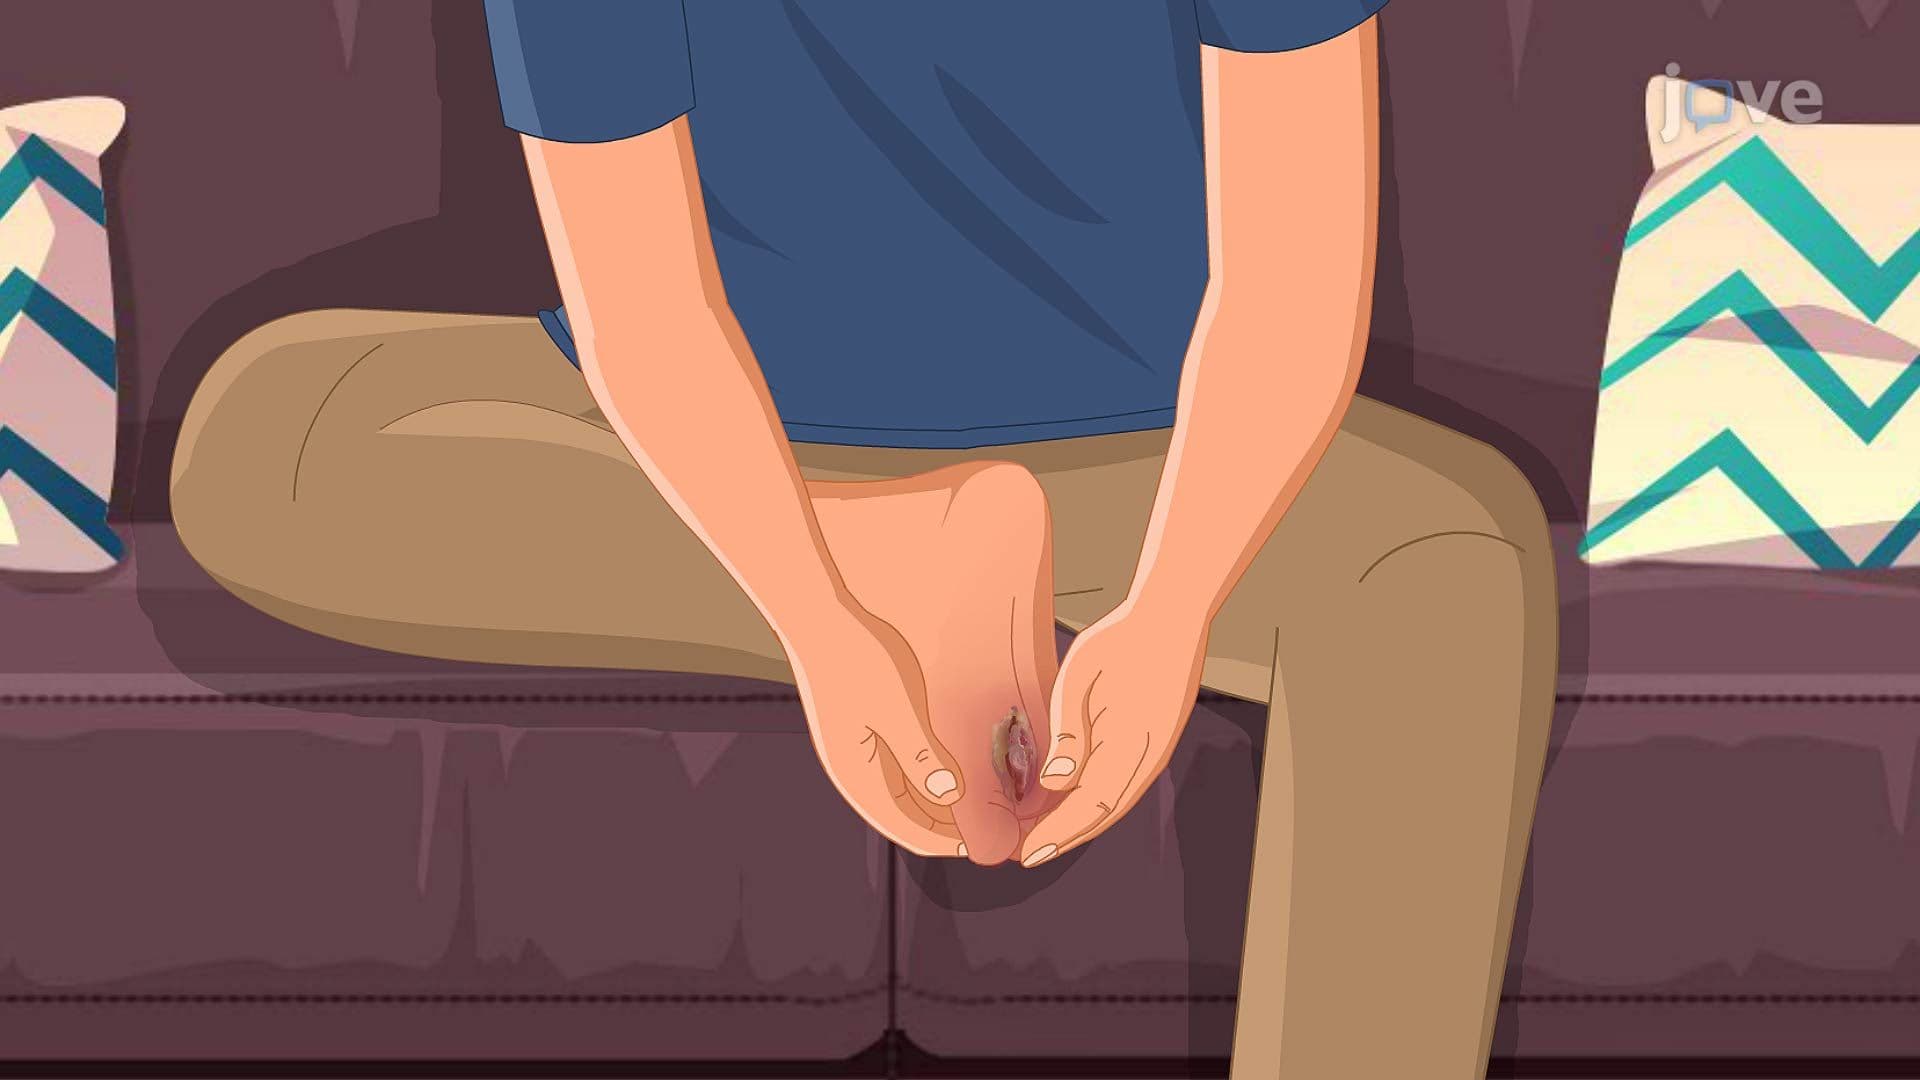
Definition A diabetic foot ulcer (DFU) is a chronic, non-healing wound that develops in individuals with diabetes. It typically occurs on pressure-bearing areas such as the heel, metatarsal heads, or hallux, and carries a high risk of infection and amputation.Pathophysiology • The development of DFUs can be explained by four interconnected mechanisms: neuropathy, ischemia, infection, and impaired wound healing. • Neuropathy is the most common factor. Sensory neuropathy reduces pain perception,...
 01:22
Diabetic Neuropathy
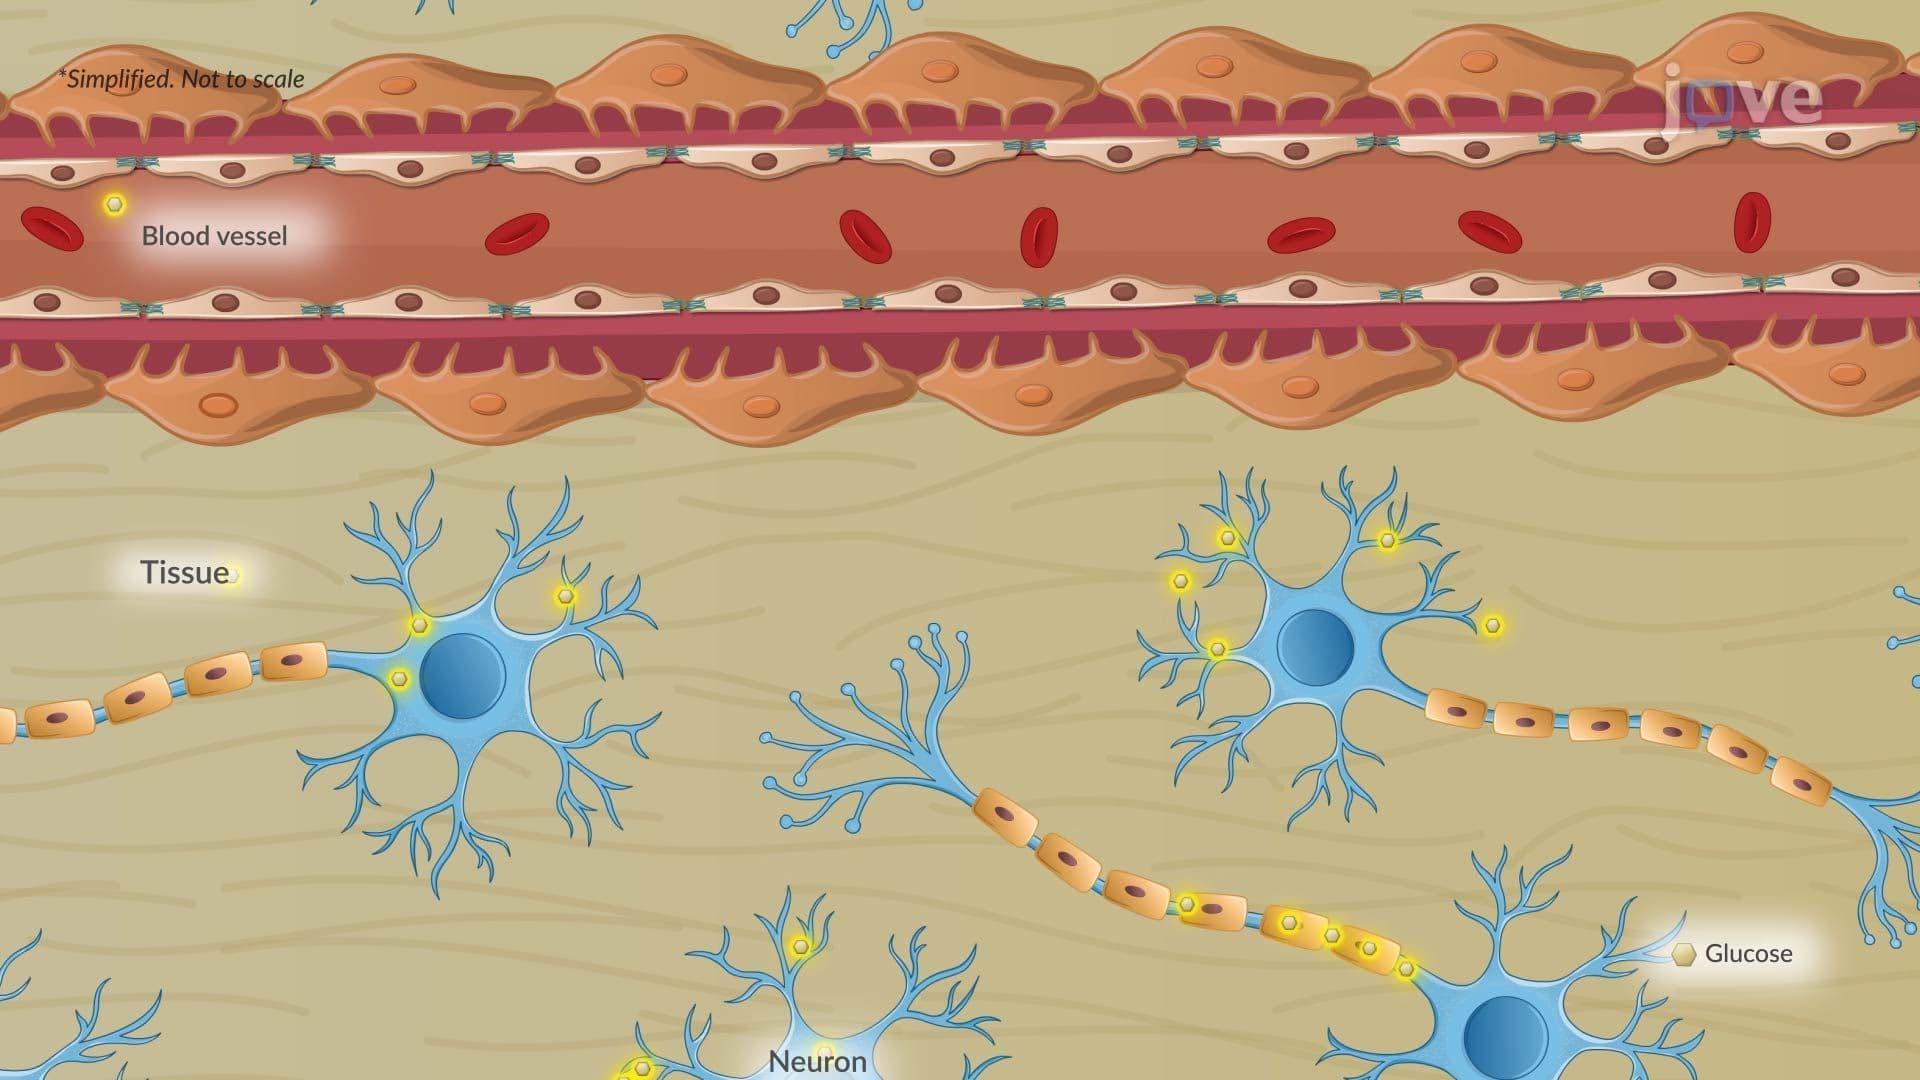
DefinitionDiabetic neuropathy is nerve damage caused by long-standing diabetes mellitus. It results directly from prolonged high blood sugar levels.PathophysiologyThe pathophysiology of diabetic neuropathy involves both metabolic and vascular disturbances triggered by chronic hyperglycemia.Metabolic injury: Elevated glucose levels activate the polyol pathway within nerve cells, leading to the accumulation of sorbitol and fructose. This increases oxidative stress, disrupts normal nerve...