関連する実験動画
Updated: Jul 24, 2026
05:18

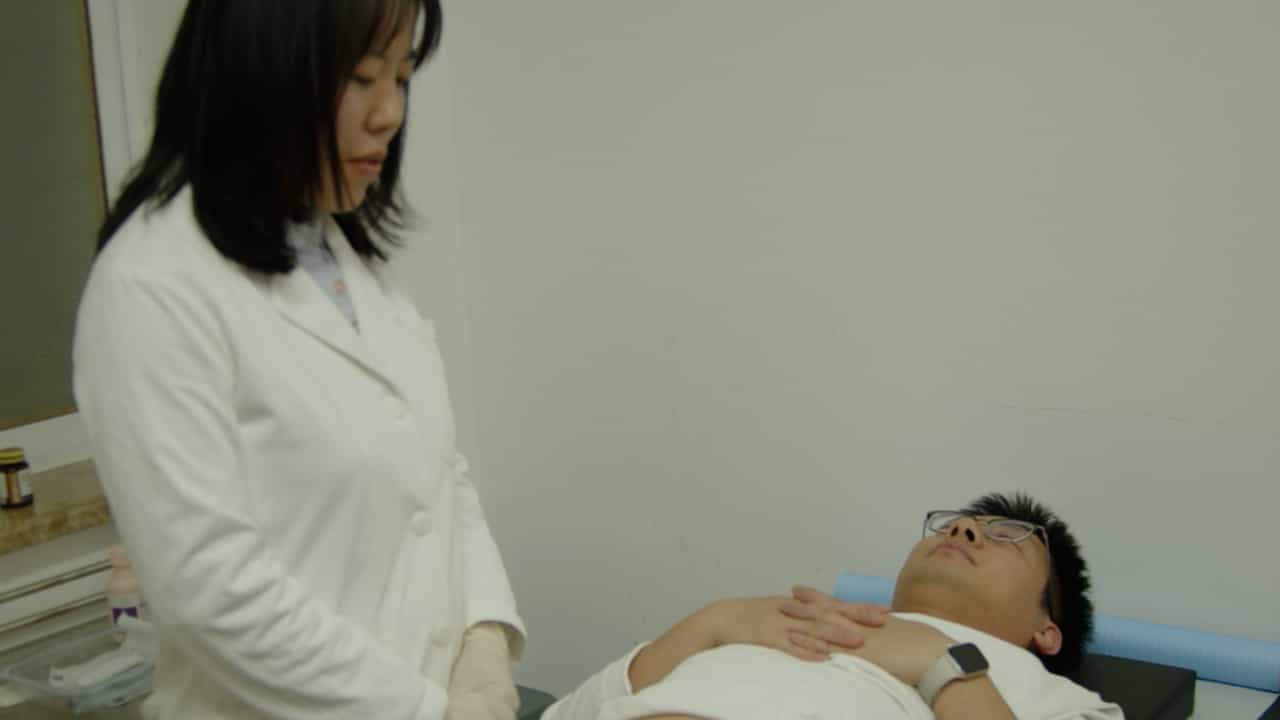
Acupoint Catgut Embedding Therapy for Abdominal Obesity Treatment
Published on: November 22, 2024
中央の肥満は"オメンタムのカッシング病"を反映しているのでしょうか
I J Bujalska1, S Kumar, P M Stewart
1Department of Medicine, University of Birmingham, Queen Elizabeth Hospital, Edgbaston, UK.
Lancet (London, England)
|April 26, 1997

まとめ
中央の肥満は代謝問題と関連しています. オメンタル脂肪細胞は,皮下脂肪細胞とは異なり,11β-ヒドロキシステロイド脱水素酶1 (11β-HSD1) を通して,不活性コルチゾンを活性コルチゾンに変換することができ,肥満を潜在的に説明します.
科学分野:
- 内分泌学 エンドックリノロジー
- メタボリックシンドロームとは
- アディポス組織生物学
背景:
- 中枢肥満は代謝機能障害と死亡率の増加と関連しています.
- コルチゾールと同様,グルココルチコイドは脂肪組織の調節に重要な役割を果たし,過剰に摂取すると中枢肥満を引き起こす可能性があります.
- 酵素11β-ヒドロキシステロイド脱水素酶 (11β-HSD) は,活性コルチゾールと不活性コルチゾンを相互変換することによって,活性コルチゾールのレベルを調節する.
研究 の 目的:
- 異なる脂肪組織貯蔵庫内のコルチゾールの代謝を調査する.
- 人間のオメンタルおよび皮下脂肪系ストロマル細胞における11のβ-HSDイソフォームの発現と活性を分析する.
主な方法:
- 培養されたオメンタルおよび皮下脂肪系ストロマル細胞は,選択腹腔外科手術を受けた16人の患者から得られた.
- これらの細胞培養で11のβ-HSD同型 (1および2) の発現と活性が分析されました.
- 細胞はコルチゾールとインスリンで処理され,酵素活性への影響を評価した.
主要な成果:
- 11β-HSD1同型のみが脂肪系ストロマ細胞で発現した.
- 11β-HSD1は,主たるオキソリデクタゼ活性 (コルチゾンをコルチゾールに変換する) を示し,これは,皮下脂肪と比較して,オメンタル脂肪において有意に高かった.
- コルチゾールとインスリンで治療されたオメンタル脂肪系ストロマル細胞は,11β-HSD1オキシ還元酵素の活性がさらに増加したことを示した.
結論:
- オメンタル脂肪からのアディポス・ストロマル細胞は,11β-HSD1経由でコルチゾンから活性コルチゾールを生成する能力を有しており,これは皮下脂肪では観察されていない機能です.
- オメンタル脂肪のコルチゾール生成能力は,コルチゾールとインスリンに曝露することで強化されます.
- これらの発見は,中央肥満に寄与する可能性があるオメンタル脂肪組織における局所的メカニズムを示唆し,潜在的にカッシング症候群の局所的形態を模倣する可能性がある.
関連する概念動画
 01:24
Obesity
The Body Mass Index (BMI) is a numerical value derived from a person's weight and height, used to categorize individuals into weight ranges. It is calculated using the formula: weight in kilograms divided by height in meters squared. Obesity is a health condition characterized by excessive accumulation of adipose tissue that poses health risks, often diagnosed with a BMI ≥ 30. This excess fat storage occurs when surplus dietary calories are converted into triglycerides and stored in adipocytes...
 01:25
Pharmacokinetics in Obese Patients: Drug Absorption and Distribution
Obesity significantly alters the pharmacokinetic processes of drug absorption and distribution, presenting unique challenges in medical treatment. The increased fat tissue and decreased lean muscle in obese individuals can significantly affect how drugs are absorbed into the body and distributed across different tissues. This alteration can lead to variances in the effectiveness and safety of medications, necessitating adjustments in dosing or drug selection for obese patients.One notable...
 01:20
Pharmacokinetics in Obese Patients: Drug Metabolism and Excretion
Drug metabolism, a critical process in the liver, involves two primary phases: Phase I reactions and Phase II conjugation. Obesity introduces significant alterations in this metabolic process, primarily due to fatty infiltration of the liver, leading to conditions such as nonalcoholic fatty liver disease (NAFLD). This condition can modify the activities of both Phase I and II enzymes, impacting how drugs are metabolized in obese patients.Phase I metabolism sees variable effects across...
 01:26
Cushing Syndrome I: Introduction
Cushing syndrome refers to the collection of clinical manifestations that arise when tissues are exposed to excessive amounts of cortisol or cortisol-like medications over an extended period. Cortisol, a glucocorticoid produced by the adrenal cortex, regulates metabolism, immune responses, and the body’s adaptation to stress. When its concentration remains chronically elevated, these physiological pathways become dysregulated, resulting in the characteristic features of the syndrome.Exogenous...
 01:19
Cushing Syndrome II: Pathophysiology
Cortisol production is normally governed by the hypothalamic–pituitary–adrenal (HPA) axis, which maintains hormonal balance through tightly regulated feedback mechanisms. Disruption of this regulatory system is central to the development of Cushing syndrome, whether the excess cortisol originates from external medications or internal pathology. Persistent cortisol elevation alters metabolism, immune function, and endocrine signaling, producing the characteristic clinical features of the...
 01:21
Chronic Pancreatitis II: Pathophysiology
Chronic pancreatitis is a progressive and irreversible inflammation of the pancreas, most often caused by long-term alcohol abuse, but it can also be related to ductal obstruction, smoking, or genetic factors.Chronic pancreatitis occurs when the pancreas is repeatedly exposed to harmful agents like alcohol, smoking, ductal obstruction, or genetic predisposition. These factors lead to the release of toxic metabolites and inflammatory cytokines, sustaining chronic inflammation in the pancreatic...