
中性原胺哈根多恩 (NPH) 胰岛素在钢笔中的悬浮不足
P M Jehle1, C Micheler, D R Jehle
1Division of Nephrology, University Hospital Ulm, Germany. peter.jehle@medizin.uni-ulm.de
Lancet (London, England)
|November 24, 1999

概括
大多数患者在笔中不充分混合中性原胺海格多恩 (NPH) 胰岛素,导致悬浮错误. 建议进行适当的混合,至少20个翻转周期,以改善糖尿病控制和减少低血糖症.
科学领域:
- 内分泌学 在内分泌学.
- 制药科学 制药科学
- 糖尿病管理 糖尿病管理
背景情况:
- 中性原胺海格多恩 (NPH) 胰岛素是一种广泛使用的通过胰岛素笔传递的中间作用胰岛素配方.
- 笔中的NPH胰岛素存在于两相溶液中,需要适当的重悬浮才能准确剂量.
- 错误的复悬浮可能导致输送胰岛素度的显著变化.
研究的目的:
- 评估使用胰岛素笔的患者对NPH胰岛素再悬浮的准确性.
- 调查NPH胰岛素悬浮错误与糖尿病患者的血糖控制之间的关联.
- 为了确定NPH胰岛素在笔子中的最佳混合技术.
主要方法:
- 109名患有糖尿病的患者在用光学系统测量卡中的NPH胰岛素含量.
- 通过问卷评估患者的胰岛素悬浮习惯.
- 患者接受了标准化的教育,通过滚动和倾倒钢笔20次来重新悬浮NPH胰岛素.
- 在3-6个月的时间里,对一小部分患者重复进行了子分析和问卷调查.
主要成果:
- 只有9%的患者进行了足够的混合 (超过十个翻转循环).
- 65%的盒子显示NPH胰岛素含量变化超过20%.
- 在教育后改善的NPH胰岛素暂停与低血糖发作显著减少相关 (p<0.05).
- 机械混合研究表明,至少需要20个循环才能完全重新悬浮.
结论:
- 在糖尿病患者中,NPH胰岛素在笔中的不充分复 suspension 是一个普遍的问题.
- 对于有效的NPH胰岛素再悬浮,建议至少进行20个翻转循环.
- 纠正悬浮错误可能有助于改善糖尿病管理,降低低血糖的风险.


相关概念视频
 01:25
Insulin: Biosynthesis, Chemistry, and Preparation
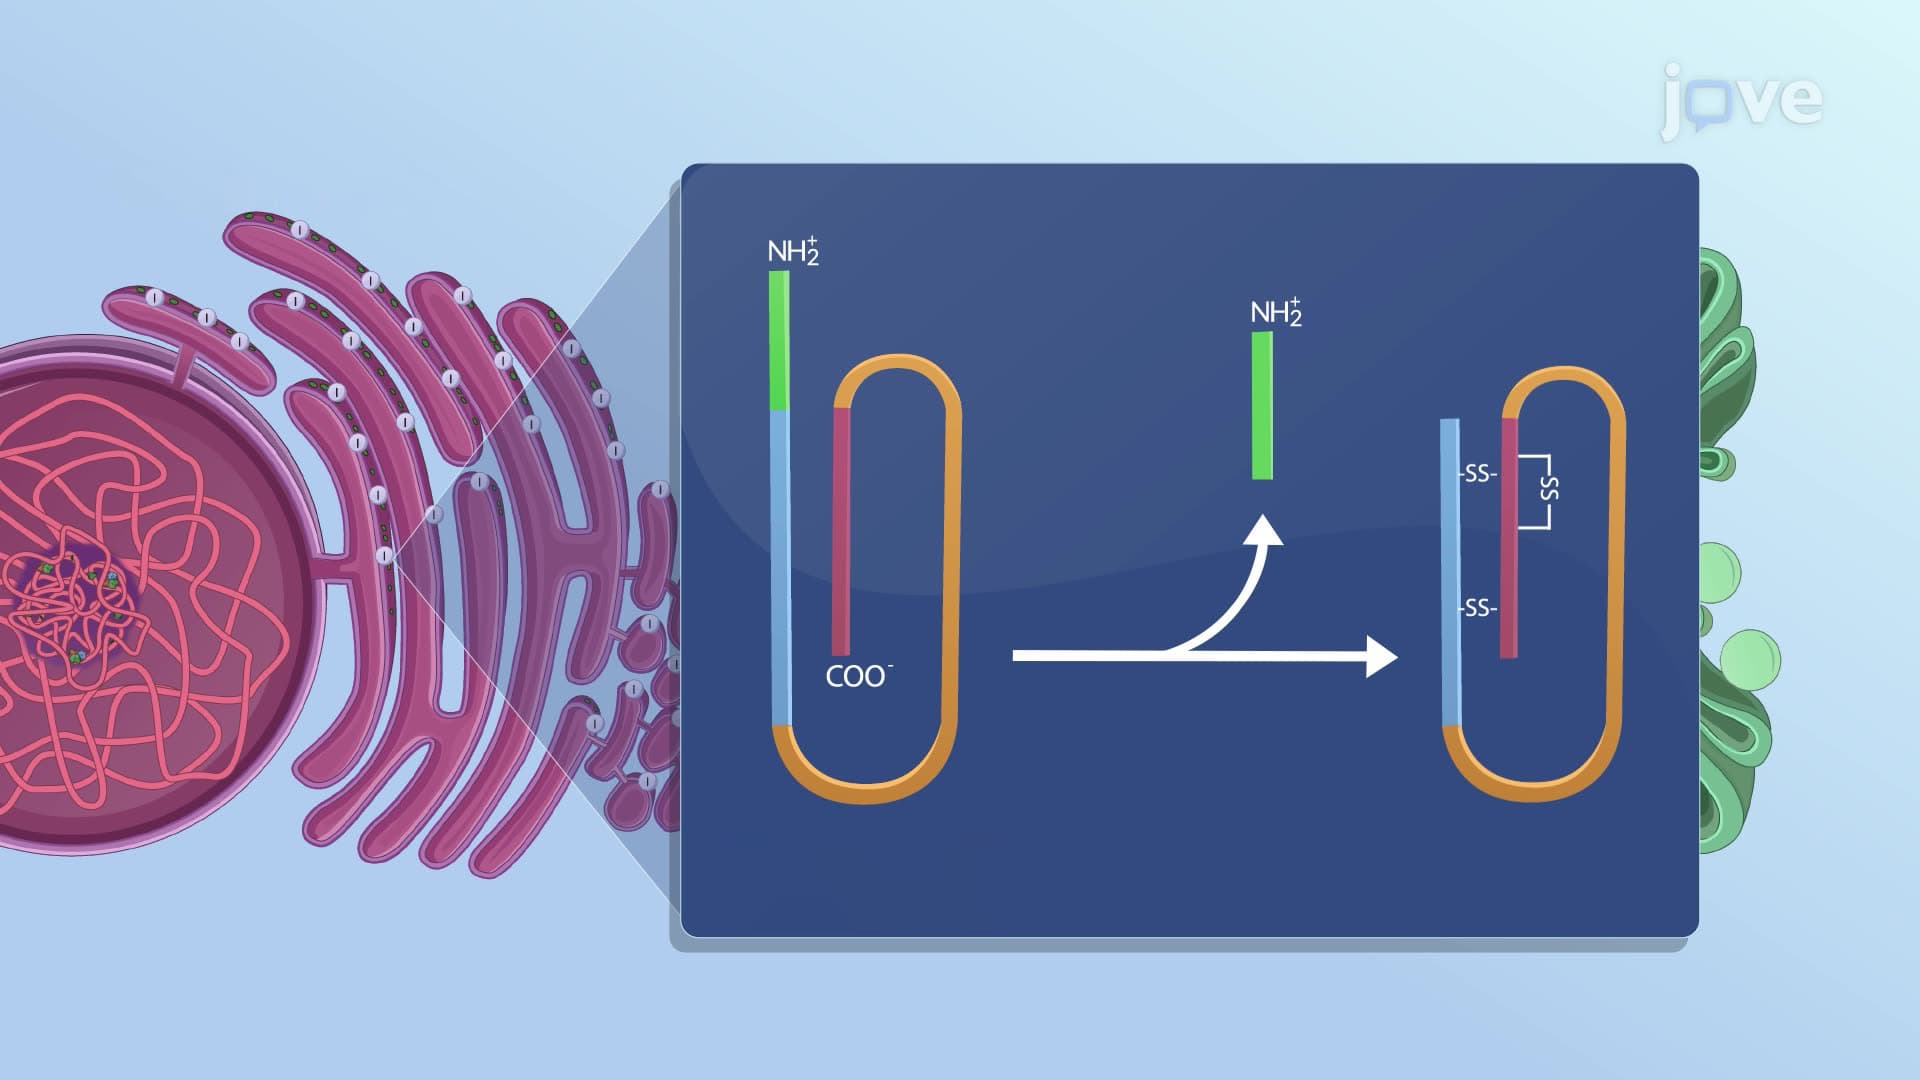
The endoplasmic reticulum (ER) of pancreatic β-cells synthesizes preproinsulin, which consists of a signal peptide, A and B chains, and a C-peptide. Preproinsulin is then cleaved and folded into proinsulin, which translocates to the Golgi apparatus for sorting and packaging into secretory granules. In these granules, enzymatic clipping generates insulin and C-peptide.
Damage or functional impairment of β-cells inhibits insulin production, leading to diabetes. Diabetes treatment primarily uses...
Damage or functional impairment of β-cells inhibits insulin production, leading to diabetes. Diabetes treatment primarily uses...
 01:27
Insulin Formulations: Types and Delivery
Insulin preparations are categorized by their duration of action into short-acting and long-acting types. Two strategies are used to modify insulin's absorption and pharmacokinetic profile: slowing the absorption post-subcutaneous injection, or altering human insulin's amino acid sequence or protein structure. These changes retain the insulin's ability to bind to the insulin receptor, but alter its behavior in solution or after injection.
Short-acting insulins are divided into rapid-acting...
Short-acting insulins are divided into rapid-acting...
 01:16
Insulin: Dosing Regimen and Adverse Effects
Insulin-replacement therapy usually includes both long-acting insulin (basal) and short-acting insulin (to cater to postprandial needs). In a diverse group of type 1 diabetes patients, the average daily insulin dose is typically 0.5-0.7 units/kg body weight. However, obese patients and pubertal adolescents may need more due to insulin resistance.
The basal dose constitutes about 40%-50% of the total daily dose, with the rest as premeal insulin. The mealtime insulin dose should mirror...
The basal dose constitutes about 40%-50% of the total daily dose, with the rest as premeal insulin. The mealtime insulin dose should mirror...
 01:06
Oral Hypoglycemic Agents: Glinides
Repaglinide (Prandin) and Nateglinide (Starlix), known as glinides, are oral insulin secretagogues that stimulate insulin release from pancreatic β cells by closing the ATP-sensitive potassium channels (KATP channel). Repaglinide controls insulin release from pancreatic β cells by managing potassium efflux. It shares two binding sites with sulfonylureas and also has a unique site, indicating overlapping mechanisms of action. With a rapid onset and a 4-7 hour duration, it effectively manages...
 01:15
Hypoglycemia and Glucagon
Without prolonged fasting, healthy individuals maintain blood glucose levels above 3.5 mM due to a well-adapted neuroendocrine counterregulatory system that effectively prevents acute hypoglycemia, a potentially life-threatening condition. The primary clinical scenarios for hypoglycemia encompass diabetes treatment, inappropriate production of endogenous insulin or insulin-like substances by tumors, and the use of glucose-lowering agents in non-diabetic individuals. Notably, hypoglycemia in the...
 01:26
Hypoglycemia
Hypoglycemia is a blood glucose level below 70 mg/dL. It commonly occurs in individuals using insulin or insulin-secreting drugs, but may also arise in non-diabetic conditions. People with type 1 diabetes are at the highest risk because they depend on exogenous insulin. People with type 2 diabetes are also at risk, especially when treated with insulin or medications such as sulfonylureas, which increase insulin release regardless of blood glucose levels. It develops when insulin levels exceed...