相关实验视频
Updated: Jul 14, 2026

08:50

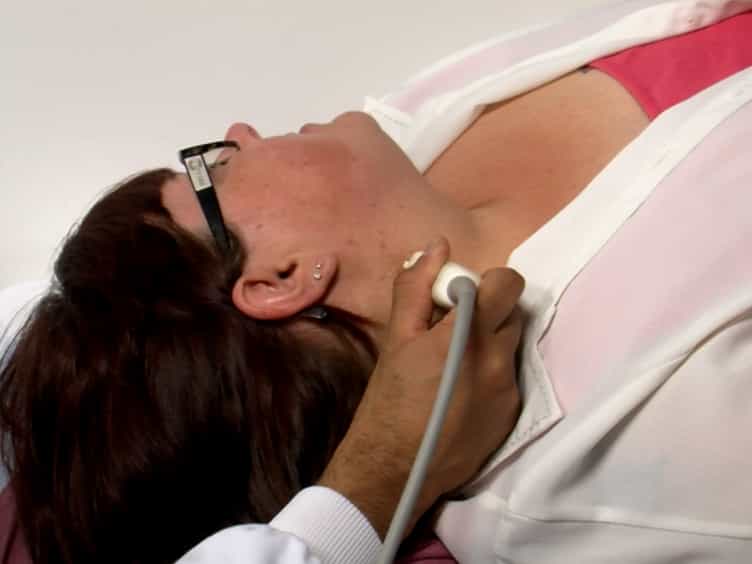
Assessment of Vascular Function in Patients With Chronic Kidney Disease
Published on: June 16, 2014
类风湿性关节炎与大动脉脉冲波速度的增加有关,这种速度由抗瘤缩因子-α疗法减少
Kaisa M Mäki-Petäjä1, Frances C Hall, Anthony D Booth
1Clinical Pharmacology Unit, University of Cambridge, Addenbrooke's Hospital, Box 110, Cambridge CB2 2QQ, United Kingdom.
Circulation
|September 6, 2006

概括
类风湿性关节炎 (RA) 患者有更硬的动脉,增加心血管风险. 抗瘤坏死因子-α (TNF-α) 治疗有效降低了这种大动脉硬度,这表明炎症控制对RA患者有好处.
科学领域:
- 心血管医学 心血管医学
- 类风湿病学 类风湿病学
- 血管生物学 血管生物学
背景情况:
- 类风湿性关节炎 (RA) 与更高的心血管风险有关,部分原因是大动脉硬度增加.
- 大动脉硬是心血管死亡率的独立预测因素.
- 传统的风险因素并不能完全解释RA中心血管风险增加的原因.
研究的目的:
- 为了确定甲状腺硬度是否在RA患者中升高.
- 为了研究 RA 炎症和大动脉硬之间的关系.
- 为了测试抗瘤坏死因子-α (TNF-α) 治疗是否可以减少大动脉硬度.
主要方法:
- 大动脉脉冲波速度 (PWV) 和增强指数测量了77名RA患者和142名对照人群.
- 评估了炎症标志物和疾病活性.
- 抗TNF-α治疗对PWV和内皮功能的影响在9名RA患者的12周内进行了评估.
主要成果:
- 与健康个体相比,RA患者的大动脉PWV显著增加 (P = 0.005).
- 大动脉PWV与年龄,平均动脉压和C反应性蛋白水平独立相关.
- 抗TNF-α疗法显著降低了大动脉PWV (P < 0.001),并改善了内皮功能.
结论:
- 风湿性关节炎与大动脉硬度增加有关,与当前的炎症有关.
- 这种增加的大动脉硬度似乎可以通过有效的炎症控制来逆转.
- 抗TNF-α疗法使大动脉硬性正常化,这表明了降低RA心血管风险的策略.

相关概念视频
 01:30
Antihypertensive Drugs: Angiotensin-Converting Enzyme Inhibitors
Angiotensin-converting enzyme (ACE), a vital component of the renin-angiotensin-aldosterone system, is abundant in lung endothelial cells. ACE converts the inactive decapeptide, angiotensin I, into the active octapeptide, angiotensin II. This potent vasoconstrictor narrows blood vessels, increasing resistance to blood flow and elevating blood pressure. Angiotensin II also stimulates aldosterone production, encouraging kidney cells to reabsorb more sodium and water from urine, thereby increasing...
 01:16
Vascular Spasm
The vascular phase, also known as vasospasm, is the initial stage of hemostasis, crucial for preventing excessive bleeding when a blood vessel is injured. After a vessel is cut, nerves in the damaged area trigger pain and other sensory impulses. Simultaneously, the smooth muscles in the vessel wall contract, resulting in a vascular spasm. This contraction reduces the vessel's diameter at the injury site, slowing or stopping blood loss through the vessel wall. Vascular spasms typically last for...
 01:17
Autoregulation of Blood Flow
Autoregulation mechanisms are characterized by their inherent capacity for self-regulation without necessitating specific nervous stimulation or endocrine control. These mechanisms facilitate the adjustment of blood flow and, therefore, perfusion specific to each tissue region. This self-regulation encompasses chemical signals and myogenic controls.
Chemical Signaling in Autoregulation
Chemical signaling operates at the precapillary sphincter level, inciting either contraction or relaxation.
Chemical Signaling in Autoregulation
Chemical signaling operates at the precapillary sphincter level, inciting either contraction or relaxation.
 01:25
Aortic Regurgitation III: Medical Management
Aortic regurgitation (AR) is when the aortic valve does not close or seal properly, leading to backward blood circulation from the aorta into the left ventricle during diastole. Common causes of AR include rheumatic heart disease, congenital valve defects, and aortic root dilation. Managing AR requires a multifaceted approach to alleviate symptoms, preserve left ventricular function, and address the underlying cause of the regurgitation. Patients with symptomatic AR or significant left...
 01:29
Hypertension II: Pathophysiology
Hypertension is a chronic condition in which the blood's force against artery walls is excessively high, posing risks such as heart disease. The condition's underlying mechanisms involve complex interactions among the cardiovascular, kidney, and autonomic nervous systems.Renin-Angiotensin-Aldosterone System (RAAS): This system significantly influences blood pressure regulation. When blood pressure decreases, the kidneys secrete renin. This enzyme transforms angiotensinogen, a plasma protein,...
 01:21
Peripheral Arterial Disease II: Clinical Manifestations and Diagnostic Evaluation
Clinical manifestationsPeripheral Arterial Disease (PAD) manifests through a range of symptoms, from the characteristic intermittent claudication to atypical presentations and severe complications in advanced stages. Intermittent claudication, a hallmark symptom of PAD, presents as exercise-induced muscle pain that typically resolves within minutes of rest. This pain is reproducible and stems from inadequate blood flow, leading to the accumulation of lactic acid produced during anaerobic...