在小鼠中,A1-腺酸受体的过度表达会导致心脏形态和功能的不良但可逆变化
相关实验视频
Updated: Jun 23, 2026
08:00
Ambulatory ECG Recording in Mice
Published on: May 28, 2010
Hajime Funakoshi1, Tung O Chan, Julie C Good
1Center for Translational Medicine, Department of Medicine, Jefferson Medical College, Philadelphia, PA 19107, USA.
Circulation
|November 8, 2006

概括
过度表达心脏中的腺受体 (ARs) 可能导致扩张性心肌病和死亡. 然而,延迟A1-AR表达到成年后会减少但不能消除心脏病理,为心力衰竭提供了洞察力.
科学领域:
- 心血管生物学 心血管生物学
- 分子心脏病学分子心脏病学
- 腺素受体信号传导
背景情况:
- 腺受体 (ARs),特别是A1-AR和A3-AR,与腺介导的心脏保护有关.
- 矛盾的是,A1-AR和A3-AR过度表达与心脏表型变化相关.
- 在心脏重塑中AR信号的时间动态需要进一步研究.
研究的目的:
- 为了研究A1-AR信号传输和心脏重塑之间的时间关系.
- 以心脏特异的方式评估受控A1-AR过度表达的影响.
主要方法:
- 使用心脏特异性,四环素调节的促进剂对小鼠控制的A1-AR过度表达.
- 在构成性和延迟的A1-AR诱导下检查的表型,生存率,心脏功能和基因表达.
- 评估了A1-AR诱导中止对心脏功能障碍的影响.
主要成果:
- 构成性A1-AR过度表达导致扩张性心肌病,心室功能减弱,心率下降,并在6-12周内死亡.
- 延迟A1-AR表达到成年期改善了生存率 (>90%在30周),并预防了即时的心脏功能障碍.
- 晚期A1-AR诱导仍然导致轻度心肌病变,加速增大,在压力过载下扩张,Akt酸化和纤维化降低.
结论:
- 强大的,构成性A1-AR过度表达诱导扩张性心肌病.
- 延迟A1-AR表达改善,但不能完全预防心脏病理.
- 可诱导的A1-AR小鼠模型为心力衰竭中的腺信号提供了洞察力,以及选择性与非选择性AR激活的后果.


相关概念视频
 01:27
Adrenergic Receptors (Adrenoceptors): Classification
Adrenergic receptors, or adrenoceptors, respond to the autonomic neurotransmitter noradrenaline and other endogenous catecholamine agonists. They are classified into two main families, α and β, based on their pharmacological response and are further subdivided depending on their location, elicited response, and affinity to specific agonists or antagonists.
α-Adrenoceptors
α-Adrenoceptors are classified into two main subtypes: α1 and α2. The α1 adrenoceptors, which are found on postsynaptic...
α-Adrenoceptors
α-Adrenoceptors are classified into two main subtypes: α1 and α2. The α1 adrenoceptors, which are found on postsynaptic...
 01:31
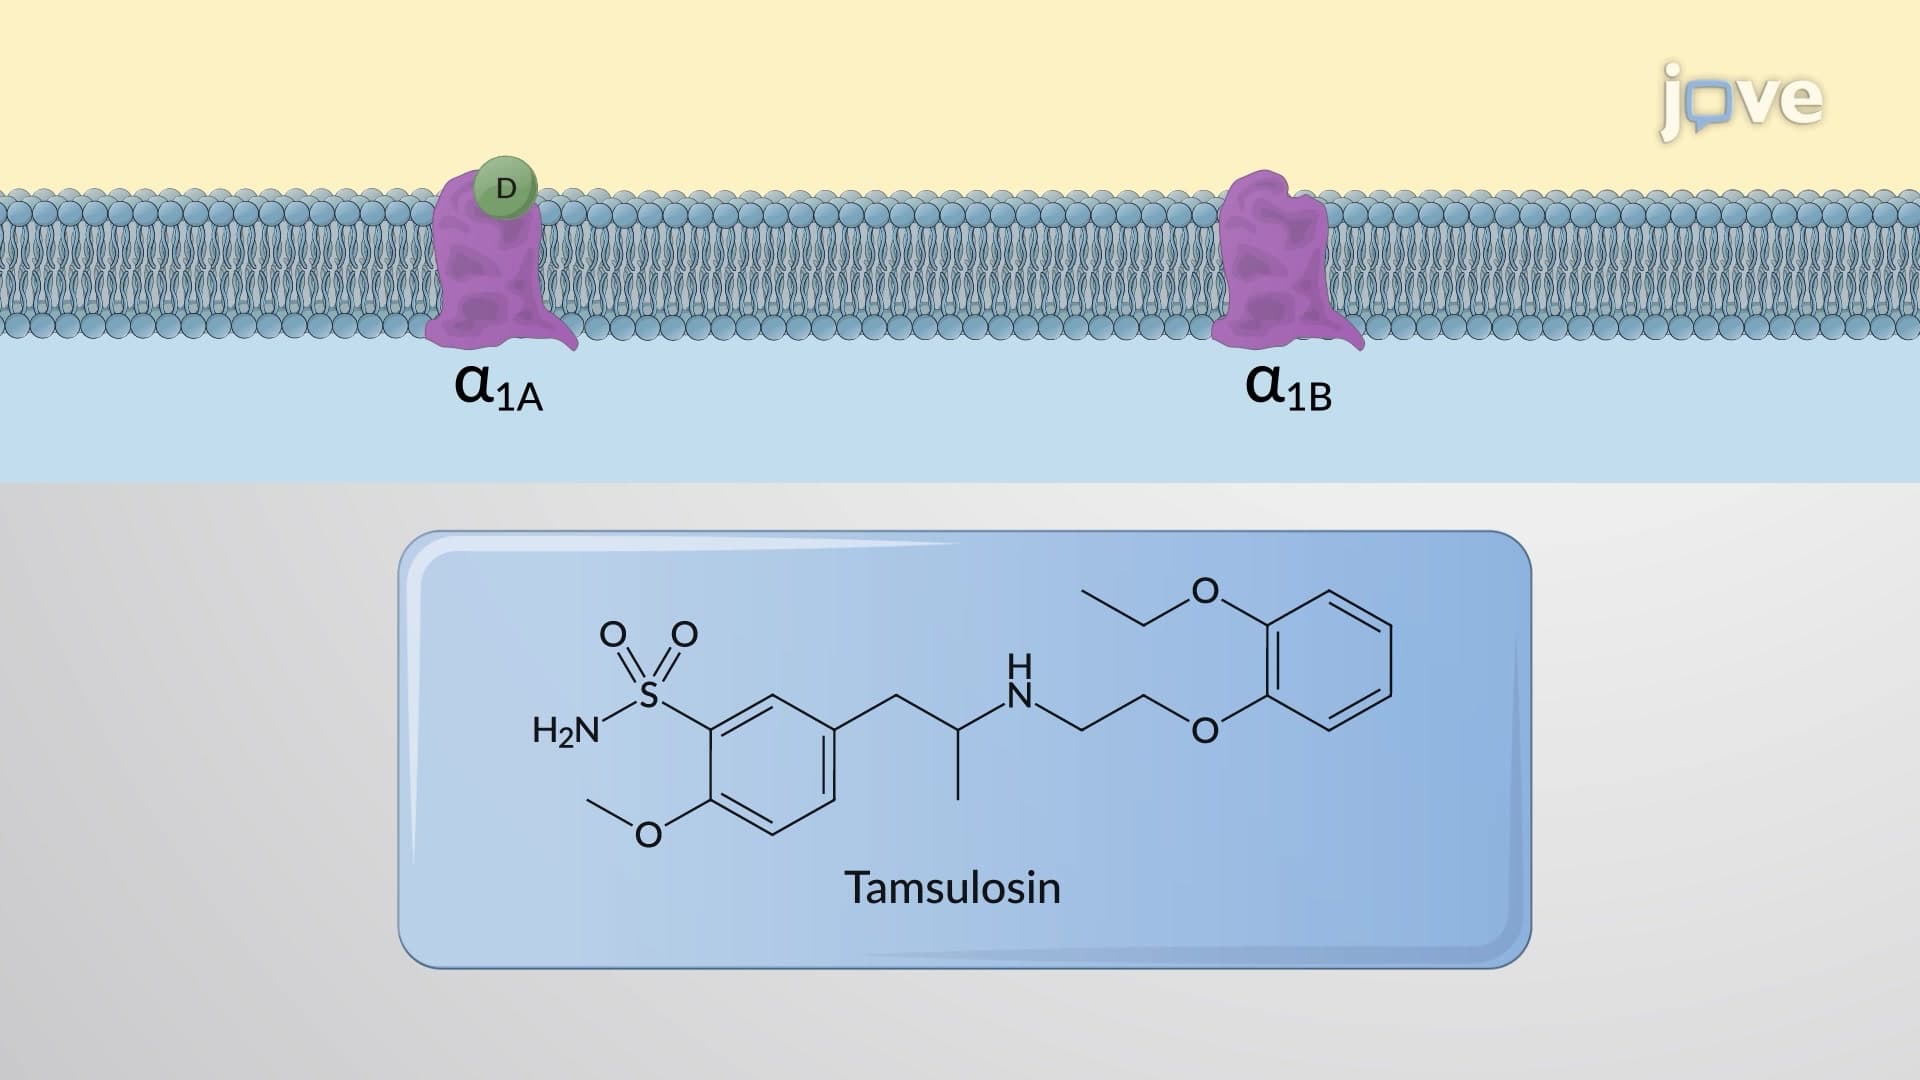
Adrenergic Receptors: ɑ Subtype
Adrenoceptors are classified into α and ꞵ classes based on their potencies to catecholamine agonists. α-adrenoceptors show the following order of catecholamine potency:
Adrenaline ≥ Noradrenaline >> Isoprenaline
α-adrenoceptors are further divided into α1 and α2-adrenoceptors.
α1-Adrenoceptors: These receptors are located postsynaptically on the effector organs and cause constriction of smooth muscle mediated by activation of phospholipase C—inositol-1,4,5-trisphosphate...
 01:26
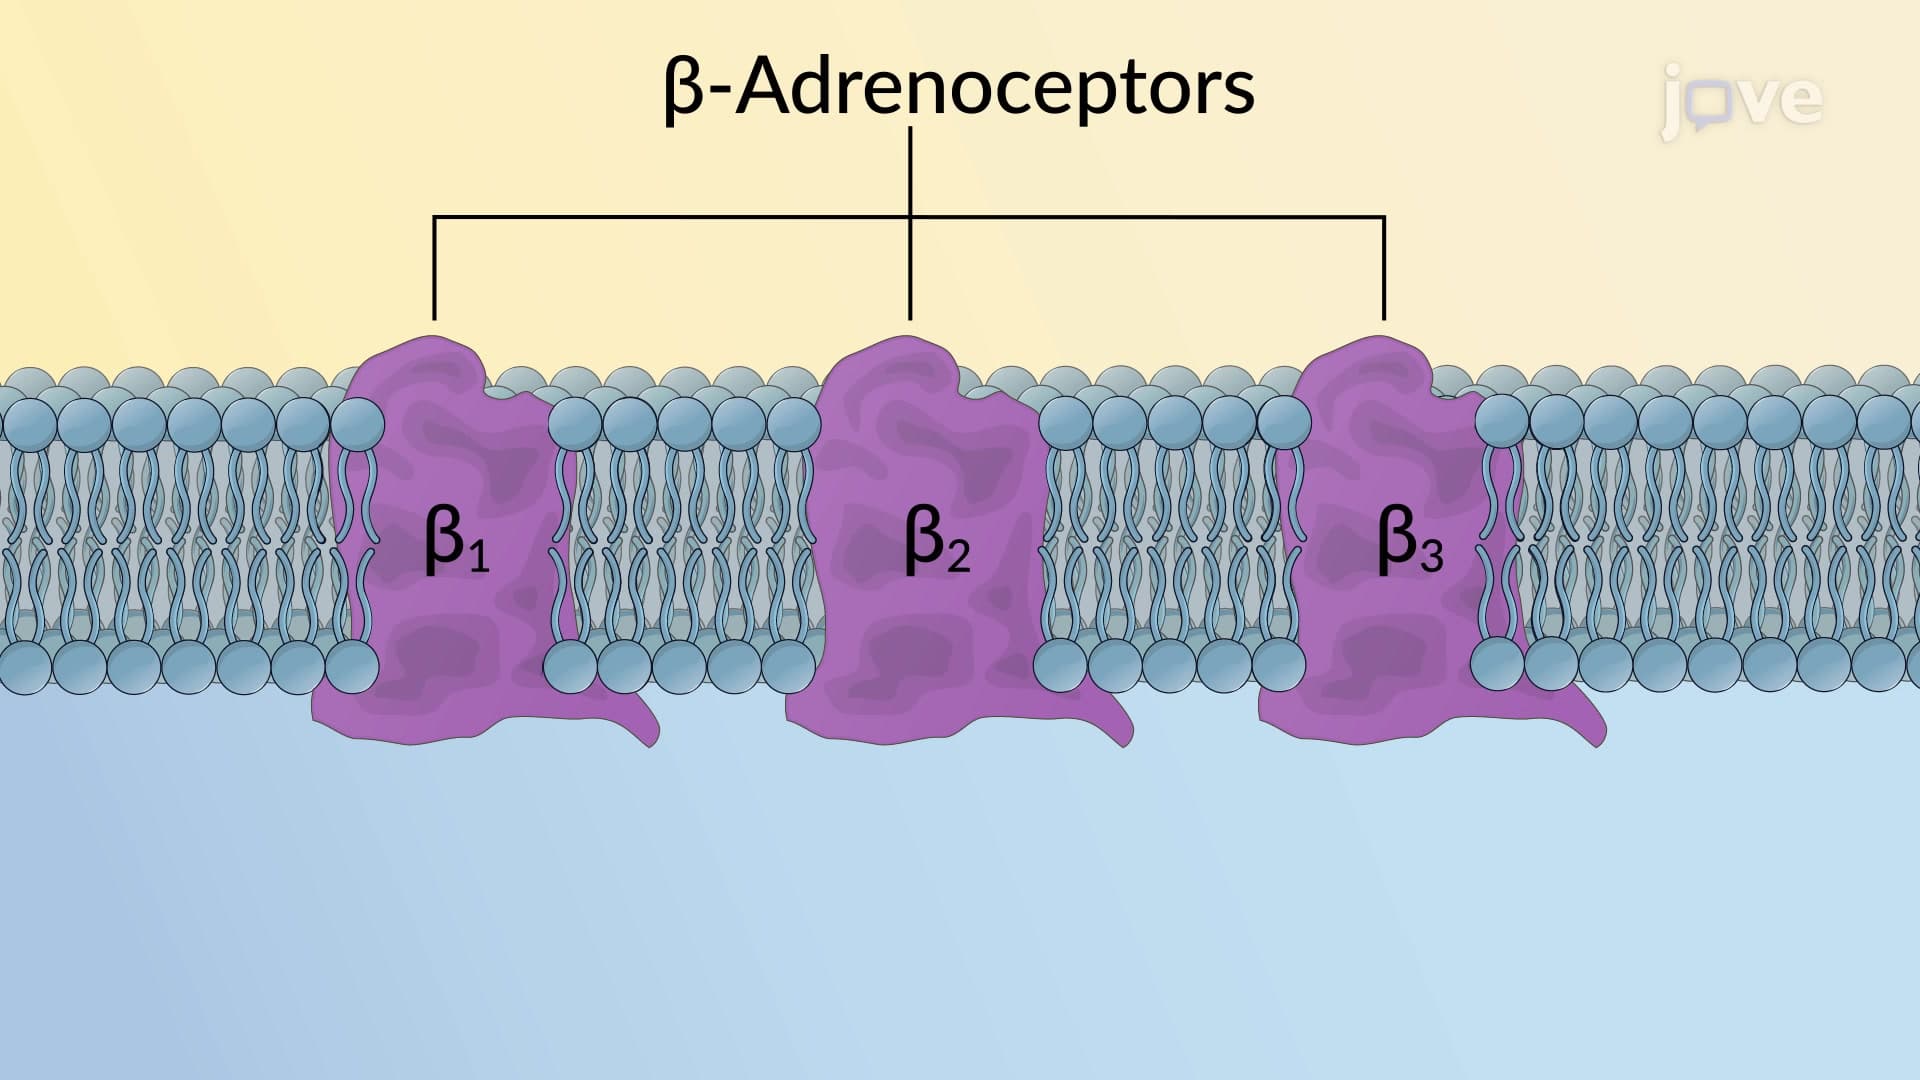
Adrenergic Receptors: β Subtype
β-adrenoceptors have varied sensitivities towards adrenaline, noradrenaline, and isoprenaline. The order of agonist potency is as follows:
Isoprenaline > Adrenaline > Noradrenaline
Neurotransmitter binding to these receptors causes activation of adenylyl cyclase resulting in increased concentrations of cAMP and modulation of calcium ion channels within the cell. They are further classified into β1, β2, and β3 subtypes.
β1-adrenoceptors: β1-adrenoceptors have equal affinities for...
 01:22
Adrenergic Antagonists: Pharmacological Actions of ɑ-Receptor Blockers
α-Adrenergic antagonists, known as α-blockers, exert their effects by inhibiting α-adrenoceptors, leading to specific physiological actions. α1-blockers and α2-blockers have distinct pharmacological actions and therapeutic applications.
α1-blockers: These drugs inhibit α1-adrenoceptors on smooth muscle cells, resulting in vasodilation. This vasodilation lowers blood pressure, making α1-blockers valuable in treating hypertension. Additionally, α1-blockers effectively address urinary obstruction...
α1-blockers: These drugs inhibit α1-adrenoceptors on smooth muscle cells, resulting in vasodilation. This vasodilation lowers blood pressure, making α1-blockers valuable in treating hypertension. Additionally, α1-blockers effectively address urinary obstruction...
 01:26
Heart Failure Drugs: Inhibitors of Renin-Angiotensin System
The activation of the sympathetic nervous system and the renin-angiotensin-aldosterone system (RAAS) contributes to cardiac remodeling, and inhibiting the RAAS is a pharmacological target in heart failure management. As a result, neurohumoral modulation is a crucial treatment principle for managing heart failure. This approach involves using medications like ACE inhibitors (ACEIs), angiotensin receptor blockers (ARBs), β-blockers, mineralocorticoid receptor antagonists (MRAs), and neutral...
 01:29
Heart Failure II: Pathophysiology
Systolic Heart Failure and Compensatory MechanismsSystolic heart failure (also termed HFrEF, Heart Failure with Reduced Ejection Fraction) is the most prevalent type of heart filure. It results in a decreased volume of blood being pumped from the ventricle. The aortic arch and carotid sinuses have baroreceptors that detect reduced blood pressure, triggering the sympathetic nervous system (SNS) to release epinephrine and norepinephrine. Initially, this response aims to boost heart rate and...