相关实验视频
Updated: Jan 8, 2026

01:27

Pulmonary Embolism III: Nursing Management
Published on: June 19, 2025
320
由于托尔类受体复杂蛋白质的功能模仿而产生的过敏性
Aurelien Trompette1, Senad Divanovic, Alberto Visintin
1Division of Molecular Immunology, Cincinnati Children's Hospital Medical Center and the University of Cincinnati College of Medicine, Cincinnati, Ohio 45229, USA.
Nature
|December 9, 2008

概括
室内灰尘的过敏原Derp2像辅助剂一样起作用,通过与托尔类受体4 (TLR4) 途径相互作用,触发过敏性喘. 这表明,脂质结合蛋白通常可能因其辅助性质而引起过敏.
科学领域:
- 免疫学 免疫学 免疫学
- 分子生物学分子生物学
- 过敏学 过敏学
背景情况:
- 气体过敏是由于对环境蛋白质的免疫过度反应引起的.
- 为什么某些蛋白质会引起过敏的具体原因尚未完全理解.
- 主要的室内灰尘虫过敏原Derp2与MD-2具有结构上的相似性,这是Toll-like受体4 (TLR4) 信号复合体的关键组成部分.
研究的目的:
- 研究Derp 2在Toll-like受体4 (TLR4) 途径中的功能性作用.
- 确定Der p 2是否具有导致过敏的自助剂性质.
- 探索MD-2-类蛋白质和脂质结合在过敏性方面的更广泛影响.
主要方法:
- 评估了Derp2与TLR4复合体的功能相互作用.
- 测试了Der p 2在没有MD-2的情况下重构脂聚糖 (LPS) 驱动的TLR4信号的能力.
- 在小鼠 (野生型,MD-2缺陷和TLR4缺陷) 中使用Derp 2敏感化和挑战诱导实验性过敏喘.
主要成果:
- 在功能上,derp2与TLR4复合体相互作用,模仿MD-2的作用.
- Derp 2可以促进LPS驱动的TLR4信号,独立于MD-2.
- 在野生型和MD-2缺乏的小鼠中,暴露于Derp 2的气道引起过敏性喘,但在TLR4缺乏的小鼠中并非如此.
结论:
- 皮肤p2具有自助剂性质,通过适应性免疫反应来解释其向.
- 这些发现表明,脂质结合蛋白的内在辅助活性,包括它们的脂质载荷,可能是过敏性的一种一般机制.
- 其他已知过敏原的MD-2-类蛋白也可能通过类似的辅助机制发挥其作用.
相关概念视频
 01:27
Pulmonary Embolism III: Nursing Management
320
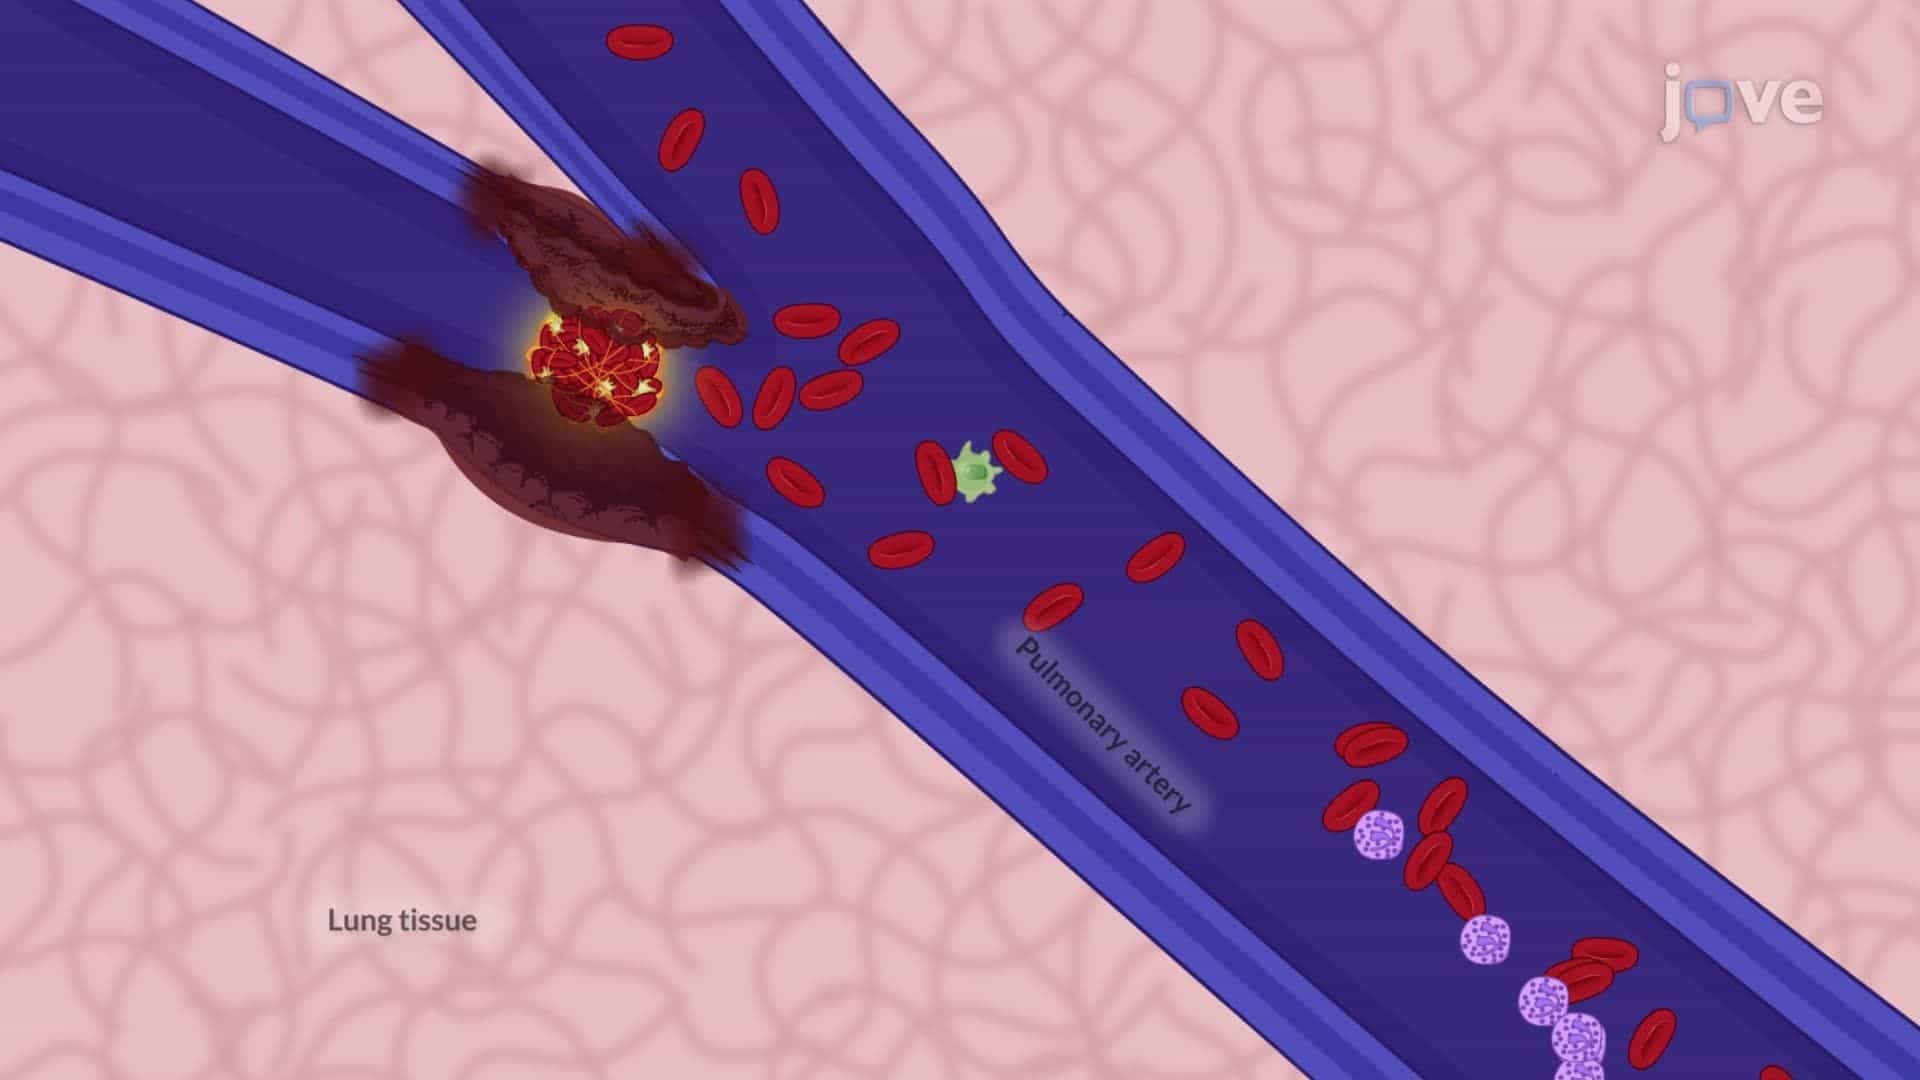
A pulmonary embolism occurs when a thrombus, amniotic fluid, tumor tissue, fat, or air embolus blocks one or more pulmonary arteries. Effective nursing management and patient education are crucial for improving outcomes and preventing recurrence.Nursing management starts with obtaining a comprehensive patient history, particularly noting any history of deep vein thrombosis (DVT). Assess for clinical manifestations, including dyspnea, chest pain, crackles, heart murmurs, and signs of right-sided...
320
 01:29
Pulmonary Embolism II: Diagnostic Studies and Interprofessional Care
277
Diagnosing Pulmonary EmbolismDiagnosing pulmonary embolism (PE) involves clinical assessment and advanced imaging tests. The preferred diagnostic tool is the spiral (helical) CT scan or CT angiography (CTA), which uses intravenous contrast media to visualize the pulmonary vasculature and identify emboli.A ventilation-perfusion (V/Q) scan is an alternative for patients unable to receive contrast media. This scan includes both perfusion and ventilation scanning. Perfusion scanning involves...
277
 01:29
Pulmonary Embolism I: Introduction
464
Pulmonary embolism (PE) occurs when a thrombus, fat or air embolus, amniotic fluid, or tumor tissue blocks one or more pulmonary arteries. These blockages originate in the venous system or the right side of the heart.EtiologyPE primarily arises from deep vein thrombosis (DVT) and other hypercoagulable states, such as inherited thrombophilias. Additional etiological factors include venous stasis, commonly seen in obesity, and endothelial injury from surgery and trauma. Less common causes include...
464
 01:29
Venous Thrombosis III: Interprofessional Care
262
Venous thrombosis requires effective prevention and treatment strategies to improve patient outcomes and reduce potential complications.Prevention StrategiesHealthcare providers must prioritize preventing venous thromboembolism (VTE) for all adult patients upon admission. Interventions depend on bleeding and thrombosis risk, medical history, current medications, diagnoses, planned procedures, and patient preferences. Patients on bed rest should change positions every two hours and, if not...
262
 01:27
Pneumothorax-II
852
Pneumothorax is a medical condition defined by the buildup of air in the pleural space between the lungs and the chest wall. This accumulation of air can lead to partial or complete lung collapse, resulting in a range of clinical manifestations. Understanding the clinical presentation and effective management strategies is crucial for healthcare professionals in providing timely and appropriate care to individuals with pneumothorax.
Clinical Manifestations:
Clinical Manifestations:
852
 01:29
Chronic Obstructive Pulmonary Disease-V: Management
3.1K
Managing Chronic Obstructive Pulmonary Disease (COPD) involves a multifaceted approach to reduce symptoms, prevent exacerbations, improve overall health status, and slow disease progression. Key strategies include lifestyle modifications, pharmacotherapy, supportive therapies, and, in some cases, surgery. Here is an overview of the primary COPD management strategies:
Smoking Cessation
Smoking Cessation
3.1K