
糖尿病高血糖症激活了CaMKII和心律失常,通过O-链 glycosylation
Jeffrey R Erickson1, Laetitia Pereira, Lianguo Wang
1Department of Pharmacology, University of California, Davis, Davis, California 95616, USA.
Nature
|October 1, 2013

概括
高血糖 (高血糖) 通过O-链接的N-乙糖胺 (O-GlcNAc) 来改变Ca2+/卡尔莫杜林依赖蛋白激酶II (CaMKII). 这种修改促进了CaMKII的激活,导致糖尿病患者的心脏和大脑功能障碍.
科学领域:
- 生物化学 生物化学
- 分子生物学分子生物学
- 心血管科学 心血管科学
背景情况:
- 卡二+/卡尔莫杜林依赖蛋白激酶II (CaMKII) 在心脏和神经元功能中起着至关重要的作用.
- 慢性CaMKII激活与心力衰竭等病理状况有关.
- 糖尿病是心血管和神经退行性疾病的重要危险因素.
研究的目的:
- 研究一种新的机制,将CaMKII和糖尿病中的高血糖信号连接起来.
- 阐明O链接N-乙糖胺 (O-GlcNAc) 修饰在高血糖症期间CaMKII活性中的作用.
- 确定这种途径对糖尿病心脏病理生理学的贡献.
主要方法:
- 在人类,老鼠和小鼠模型中研究了O-GlcNAc的CaMKII修饰.
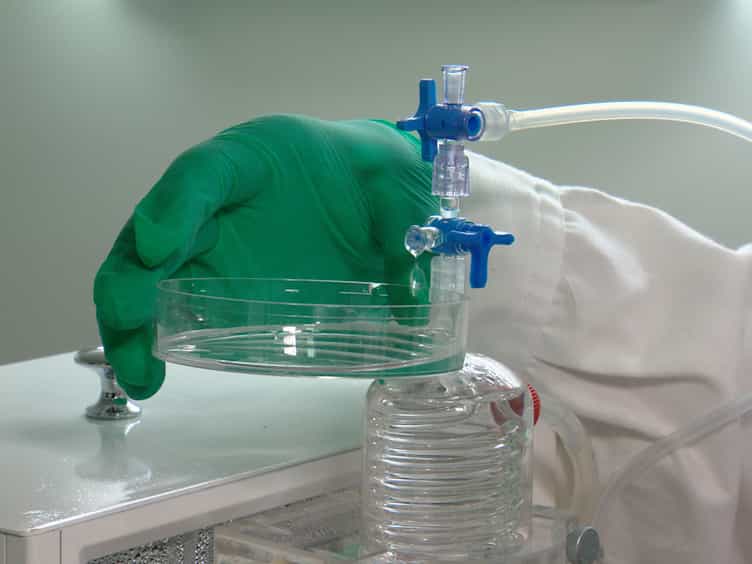
- 在高葡萄糖条件下,评估了心肌细胞中的CaMKII激活和质网膜Ca2+) 释放.
- 利用了O-GlcNAc信号的药理抑制和CaMKIIδ.的遗传移除.
- 在完整的输血心脏和糖尿病动物模型中检查了心律失常.
主要成果:
- 急性高血糖症诱导O-GlcNAc对CaMKII在Ser279的修饰,导致自主激活.
- 在糖尿病患者和老鼠的心脏和大脑中,O-GlcNAc修饰的CaMKII水平升高.
- 增加的葡萄糖增强了心肌细胞中依赖于CaMKII的自发Ca2+释放,导致心脏功能障碍和心律失常.
- 对CaMKIIδ的药理抑制或遗传除可以防止这些高血糖引起的效应.
- 糖尿病动物的心律失常会因高葡萄糖而加剧,而O-GlcNAc阻塞则会抑制.
结论:
- CaMKII的O-GlcNAc修饰代表了一种由高血糖症激活的新信号通路.
- 这种修改有助于糖尿病的心脏和神经元病理生理学.
- 针对O-GlcNAc信号可能为影响心脏和大脑的糖尿病并发症提供治疗策略.


相关概念视频
 01:09
GPCRs Regulate Adenylyl Cylase Activity
6.9K
Some GPCRs transmit signals through adenylyl cyclase (AC), a transmembrane enzyme. AC helps synthesize second messenger cyclic adenosine monophosphate (cAMP). AC catalyzes cyclization reaction and converts ATP to cAMP by releasing a pyrophosphate. The pyrophosphate is further hydrolyzed to phosphate by the enzyme pyrophosphatase, which drives cAMP synthesis to completion. However, cAMP is rapidly degraded to 5′ AMP by the enzymes phosphodiesterase (PDE), preventing overstimulation of...
6.9K
 01:25
cAMP-dependent Protein Kinase Pathways
7.3K
Cyclic Adenosine Monophosphate (cAMP) is an essential second messenger that activates protein kinase A (PKA) and regulates various biological processes. A single epinephrine molecule binds to GPCR and activates several heterotrimeric G proteins, each stimulating multiple adenylyl cyclase, amplifying the signal, and synthesizing large numbers of cAMP molecules. Small changes in cAMP concentration affect PKA activity. The binding of four cAMP molecules induces a conformational change in PKA,...
7.3K
 01:26
Type I Diabetes II: Pathophysiology
75
Type 1 diabetes mellitus arises from an immune-mediated destruction of pancreatic β-cells, resulting in an absolute deficiency of insulin. This process develops in genetically susceptible individuals when autoimmunity, environmental exposures, and immunologic dysregulation converge to trigger a targeted attack on the insulin-producing cells of the pancreas. The β-cells are located within the islets of Langerhans and are essential for regulating blood glucose by facilitating cellular...
75
 01:24
Type II Diabetes II: Pathophysiology
28
PathophysiologyType 2 diabetes mellitus (T2DM ) is a chronic metabolic disorder characterized by insulin resistance and progressive pancreatic β-cell dysfunction, leading to impaired glucose homeostasis. It results from interactions among genetic predisposition, environmental factors, and metabolic stressors, such as overnutrition and a sedentary lifestyle.Insulin Resistance and Glucose DysregulationEarly T2DM involves insulin resistance in skeletal muscle, adipose tissue, and the liver.
28
 01:29
Hyperglycemia
25
Hyperglycemia is an abnormally high blood glucose level. It is diagnosed by fasting glucose ≥126 mg/dL, 2-hour oral glucose tolerance test (or OGTT) ≥200 mg/dL, random glucose ≥200 mg/dL with symptoms, or HbA1c ≥6.5%. However, HbA1c results may be unreliable in certain conditions, such as anemia or hemoglobinopathies, and the diagnosis should be confirmed unless classic symptoms are present. Postprandial hyperglycemia is typically considered significant when glucose...
25
 01:22
Diabetic Ketoacidosis ll: Pathophysiology
30
Diabetic ketoacidosis (DKA) is a metabolic emergency characterized by hyperglycemia, ketonemia, and metabolic acidosis. It results from severe insulin deficiency and an excess of counterregulatory hormones, leading to uncontrolled lipolysis, ketogenesis, and widespread electrolyte and fluid disturbances.Pathophysiology The central event in DKA is a profound loss of insulin action. Without insulin, glucose uptake in insulin-dependent tissues is impaired, while hepatic glucose production...
30