
阿特拉库里姆与Cis-Atracurium对于儿科患者的喉放松和血液动力学稳定:一个随机的双盲研究
Arshad Nadirsha1, Nandkishore Agrawal1, Habib Md R Karim1
1Anaesthesiology, Critical Care, and Pain Medicine, All India Institute of Medical Sciences, Raipur, IND.
Cureus
|July 26, 2023

概括
与儿童的cis-atracurium相比,Atracurium为喉腔镜和内内管管道提供了更好的条件. 虽然cis-atracurium提供了更好的血液动力学稳定性,但atracurium导致了显著更优秀的输管治疗结果.
科学领域:
- 麻醉学 麻醉学
- 儿科麻醉 儿科麻醉
- 药理学 药理学是指药理学的学科.
背景情况:
- 在成年人中,对 atracurium 和 cis-atracurium 的等效剂量已显示出可变的疗效,用于喉腔镜检查和内内输管 (LETI).
- 关于这些神经肌肉阻断剂在儿童群体中对LETI的比较有效性的数据有限.
研究的目的:
- 为了比较等效剂量 atracurium 和 cis-atracurium 在儿童中达到最佳 LETI 条件时的疗效.
- 评估和比较血液动力学稳定性和儿科LETI期间与两种药物相关的不良事件.
主要方法:
- 一项随机,双盲,并行手臂研究,涉及104名3-12岁儿童.
- 参与者接受了2ED95阿特拉克 (0.5mg/kg) 或2ED95 cis-atracurium (0.1mg/kg).
- 使用三分级评价LETI质量;监测血液动力学和不良事件.
主要成果:
- 优秀的LETI条件与阿特拉库 (53.8%) 相比,与cis-atracurium (19.2%) (p<0.001) 显著高.
- 这两种药物都减弱了喉腔镜诱导的交感激增,但血动力恢复到基线的速度更快,与cis-atracurium (72分钟) (p<0.001) 相比,atracurium (7分钟) 更快.
- 在 atracurium 组中发生了一例冲;在 cis-atracurium 组中没有发现冲或显著不良事件.
结论:
- 与cis-atracurium (0.1mg/kg) 相比,atracurium (0.5mg/kg) 在3-12岁儿童中提供了明显更好的"优良的LETI条件".
- 在血液动力维护和减少不良事件方面,cis-atracurium提供了轻微的优势,但在实现最佳输管条件方面,atracurium更优越.

相关概念视频
 01:31
Skeletal Muscle Relaxants: Therapeutic Uses
515
Skeletal muscle relaxants are used to relax muscle tone and alleviate painful muscle contractions. However, the choice of skeletal muscle relaxants depends on the duration of the surgical procedure in order to minimize potential side effects. Skeletal muscle relaxants like neuromuscular blocking agents [NMBAs] are commonly employed as adjuvants alongside general anesthetics in clinical settings. NMBAs are also used to maintain controlled ventilation during surgery of the larynx or pharynx...
515
 01:21
Skeletal Muscle Relaxants: Adverse Effects
401
Skeletal muscle relaxants are widely used for muscle paralysis and relieving pain following any muscle injury or stiffness. However, depending on the drug type, they can have adverse effects that range from mild to severe. Usually, nondepolarizing neuromuscular blockers have minimal side effects. For example, drugs like d-tubocurarine, cisatracurium, and rocuronium cause hypotension, whereas drugs like baclofen, when stopped abruptly, can lead to the recurrence of spastic conditions.
Unlike...
Unlike...
401
 01:19
Depolarizing Blockers: Pharmocokinetics
353
Depolarizing blockers are administered through intravenous injection. Succinylcholine is the most common choice of depolarizing blockers in emergency clinical practices. Although they have a rapid onset, they readily diffuse away from the motor end plate into the extracellular fluid. They are metabolized by enzymes such as liver butyrylcholinesterase and plasma pseudocholinesterases. This produces a short duration of action, typically 5-10 minutes long, unlike nondepolarizing blockers, which...
353
 01:09
Peripherally and Centrally Acting Muscle Relaxants: A Comparison
3.4K
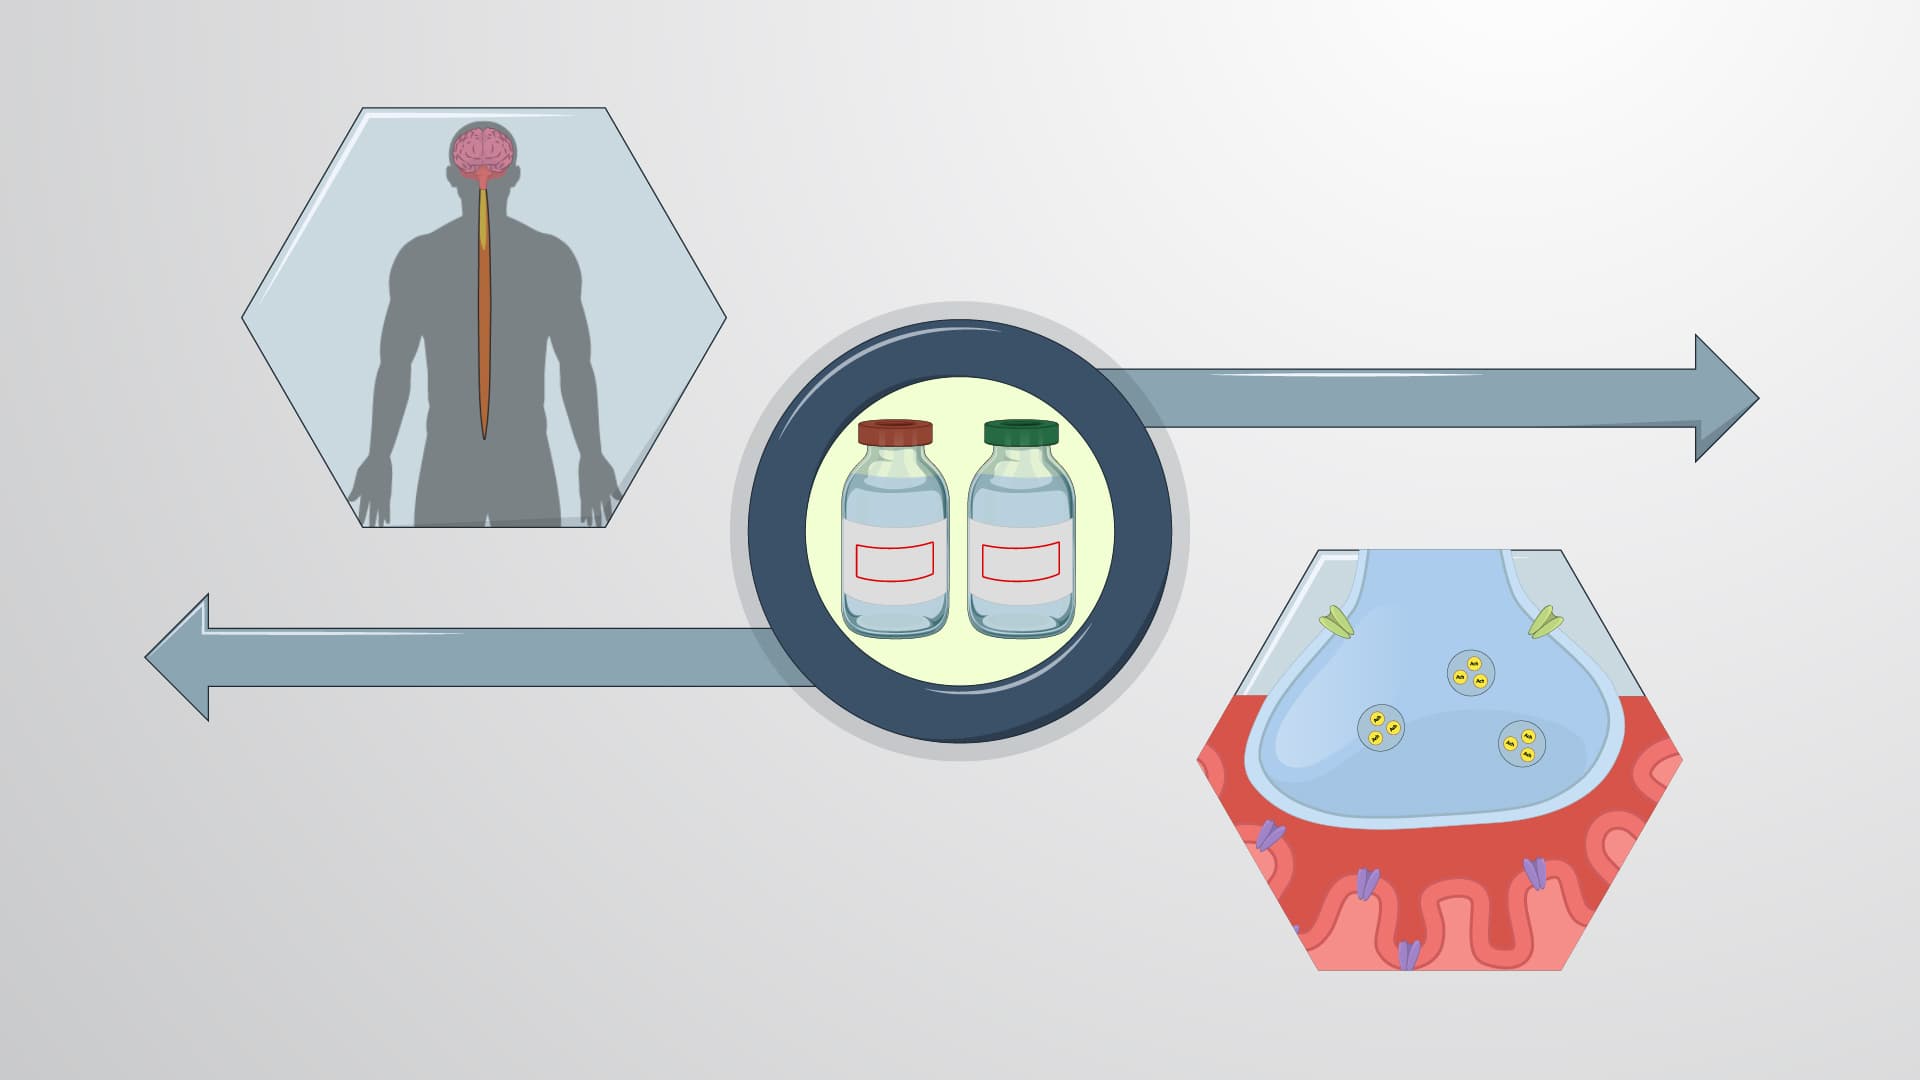
Skeletal muscle relaxants can target the central nervous system [CNS] to reduce muscle tension or act directly at the neuromuscular junction to induce temporary paralysis. These two classes of muscle relaxants are called centrally acting muscle relaxants and peripherally acting muscle relaxants. They differ in their action, mechanism, administration route, and clinical uses.
Centrally acting muscle relaxants can be further divided into spasmolytic and antispasmodic drugs. Spasmolytic...
Centrally acting muscle relaxants can be further divided into spasmolytic and antispasmodic drugs. Spasmolytic...
3.4K
 01:27
Nondepolarizing (Competitive) Neuromuscular Blockers: Pharmacological Actions
458
Nondepolarizing neuromuscular blockers prevent the membrane depolarization of muscle cells and inhibit muscle contraction. These are usually administered with anesthetics to achieve complete muscle relaxation. Upon administration, these drugs first block the small, rapidly contracting muscles of the face and hands, followed by the larger muscles of the trunk and the intercostal muscles. The diaphragm is the last muscle to be affected.
Although all competitive neuromuscular blockers are designed...
Although all competitive neuromuscular blockers are designed...
458
 01:11
Nondepolarizing (Competitive) Neuromuscular Blockers: Pharmacokinetics
478
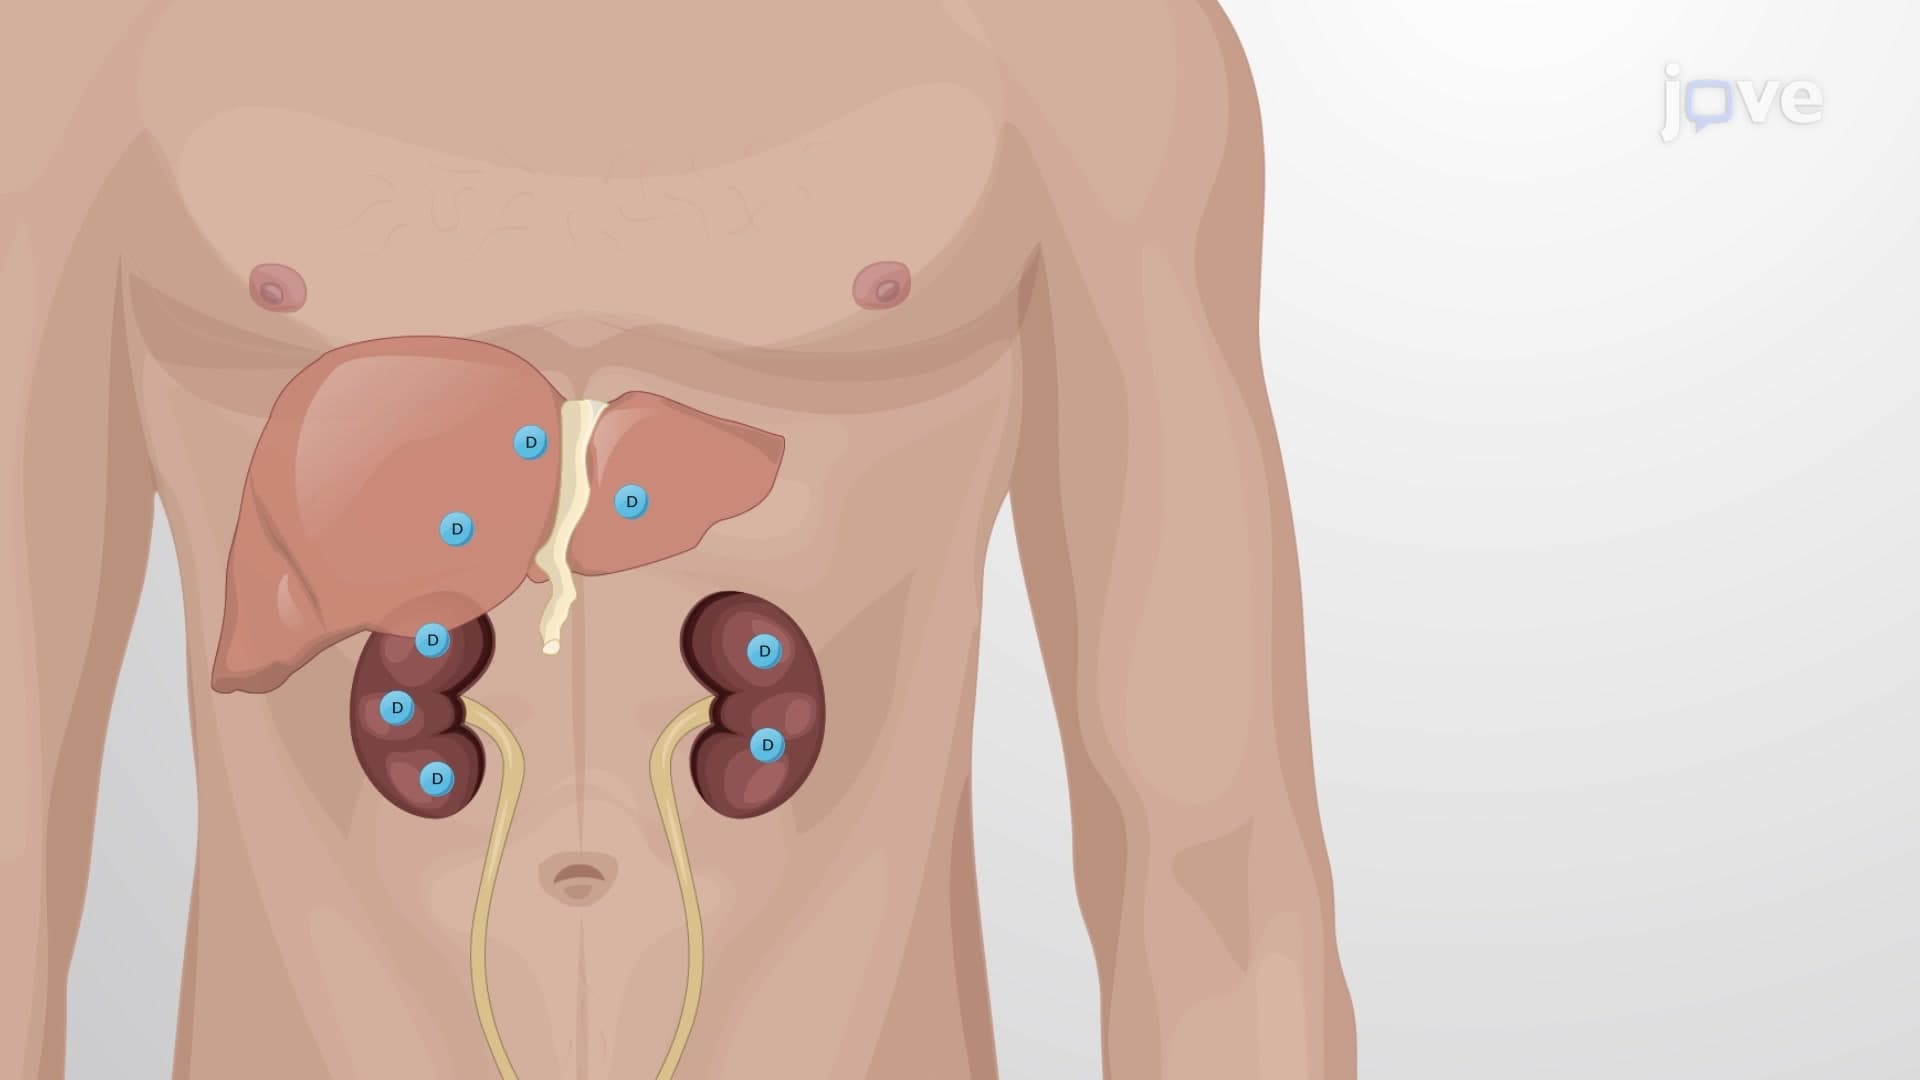
All neuromuscular blocking agents are injected intravenously because they are poorly absorbed from the GI tract. Rapid onset is achieved with intravenous administration, although absorption is also adequate from an intramuscular injection. Since these agents are highly ionized, they do not readily penetrate cell membranes or cross the blood-brain barrier.
Instead, they are transported by the blood to different tissues. Muscles with a greater blood supply (arteries) and blood flow receive more...
Instead, they are transported by the blood to different tissues. Muscles with a greater blood supply (arteries) and blood flow receive more...
478