由于SARS-CoV-2感染而导致呼吸衰竭的机械通风患者的长期放射性肺部变化
Mircea Stoian1, Adina Roman2, Alina Boeriu2
1Department of Anesthesiology and Intensive Care, George Emil Palade University of Medicine, Pharmacy, Sciences and Technology of Târgu Mureș, 540139 Targu Mures, Romania.
Biomedicines
|October 28, 2023

概括
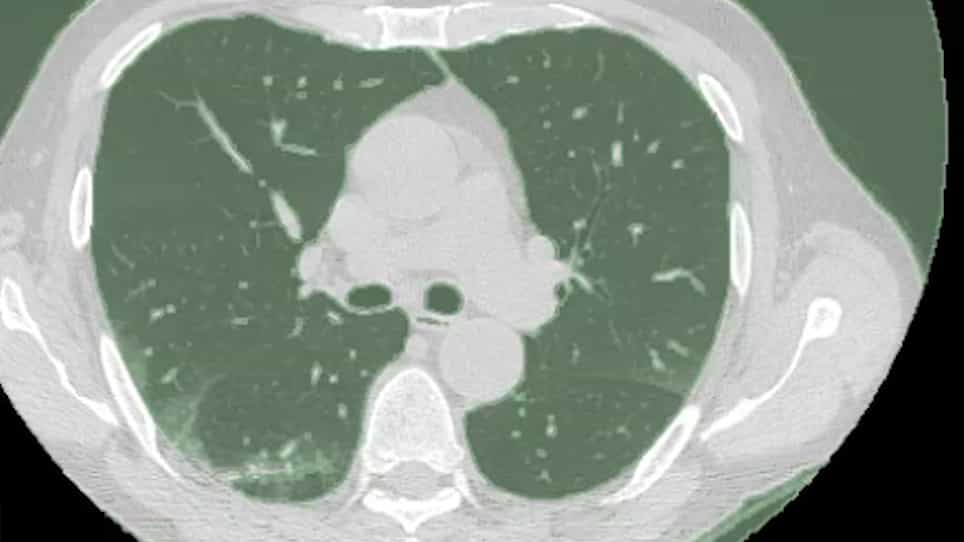
需要机械通风的COVID-19幸存者可能会患上肺纤维化. 这项研究没有发现通风类型和CT扫描变化之间的联系,但注意到与费里丁,代谢综合征和前素水平的关联.
科学领域:
- 关键护理医学 关键护理医学
- 肺部病理学 肺部病理学
- 放射学 放射学是一门学科.
背景情况:
- 在全球范围内,COVID-19已经造成了数百万人的死亡.
- 机械通风改善了重症COVID-19患者的生存率.
- 长期的并发症,如肺纤维化是令人担忧的.
研究的目的:
- 分析机械通风和COVID-19患者的放射性变化之间的关联.
- 根据通风策略和患者特征,研究临床差异.
- 为了评估6个月后的肺纤维化发病率.
主要方法:
- 54名ICU COVID-19患者的前性研究.
- 在6个月的随访期对胸部CT扫描进行分析.
- 通风方法 (IMV/NIMV) 与放射学和准临床数据的相关性.
主要成果:
- 通风类型和6个月后的放射性变化之间没有显著的关联.
- 在IMV和第一天的费里水平之间存在显著的关联 (p=0.034).
- 在PaO2/FiO2比率和代谢综合征 (p=0.03) 和前素 (p=0.01) 之间存在显著的关联.
- 很大一部分患者在6个月后发展为肺纤维化.
结论:
- 肺纤维化是ICU COVID-19幸存者的常见后果.
- 动态监测和放射性评估对于接受氧气或通风的患者至关重要.
- 需要进一步研究长期肺纤维化治疗的替代疗法.

相关概念视频
 01:30
Radiological Investigation II: MRI and Ventilation Perfusion Scan
131
Description
Magnetic Resonance Imaging (MRI) and Ventilation Perfusion Scans are two radiological investigations that offer detailed diagnostic images of the body, particularly lung structures.
MRI
MRI uses magnetic fields and radiofrequency signals to distinguish between normal and abnormal tissues. This technology provides a more detailed diagnostic image than CT scans, enabling it to characterize pulmonary nodules, stage bronchogenic carcinoma, and evaluate inflammatory activity in...
131
 01:27
Pneumothorax-II
170
Pneumothorax is a medical condition defined by the buildup of air in the pleural space between the lungs and the chest wall. This accumulation of air can lead to partial or complete lung collapse, resulting in a range of clinical manifestations. Understanding the clinical presentation and effective management strategies is crucial for healthcare professionals in providing timely and appropriate care to individuals with pneumothorax.
Clinical Manifestations:
Clinical Manifestations:
170
 01:21
Acute Respiratory Failure-II
249
Type I Respiratory Failure, or hypoxemic respiratory failure, occurs when the partial pressure of oxygen (PaO2) in arterial blood falls below 60 mmHg while breathing room air without a corresponding increase in arterial carbon dioxide levels (PaCO2). This condition highlights a significant impairment in the lungs' capacity to oxygenate the blood.
The underlying physiological abnormalities that contribute to hypoxemic respiratory failure include:
The underlying physiological abnormalities that contribute to hypoxemic respiratory failure include:
249
 01:30
Acute Respiratory Failure-III
190
Hypercapnic respiratory failure, also known as Type 2 or ventilatory respiratory failure, is a severe condition characterized by the body's inability to effectively remove carbon dioxide (CO2) from the bloodstream. It leads to an arterial CO2 pressure (PaCO2) exceeding 45 mmHg and a blood pH above 7.35. This situation indicates that the body's ventilatory demand, or the ventilation needed to maintain normal PaCO2 levels, surpasses its supply or the maximum gas flow achievable without...
190
 01:23
Acute Respiratory Failure-IV
160
Respiratory failure can manifest suddenly or gradually, characterized by a rapid decline in PaO2 and a rapid rise in PaCO2. This situation indicates a severe respiratory problem that may quickly become a life-threatening emergency. One of the early signs of hypoxemic Acute Respiratory Failure (ARF) is a change in mental status due to the brain's sensitivity to oxygen levels and changes in acid-base balance. Symptoms such as restlessness, confusion, and agitation suggest inadequate oxygen...
160
 01:29
Acute Respiratory Failure-V
143
The treatment for acute respiratory failure varies based on factors like the underlying cause, overall health, and severity. A collaborative healthcare team is essential for early detection, often through arterial blood gas analysis. Identifying the cause is the primary goal, with treatment strategies adjusted for ventilation/perfusion (V/Q) mismatch, shunting, or diffusion impairment.
Ensure that patients are monitored continuously for their response to therapy, including changes in...
Ensure that patients are monitored continuously for their response to therapy, including changes in...
143