克洛米芬酸盐加莱特醇与单独的克洛米芬酸盐用于卵巢诱导在不孕妇女有排卵功能障碍:一个随机对照试验
Pattraporn Chera-Aree1, Sirikul Tanpong2, Isarin Thanaboonyawat2
1Infertility and Reproductive Biology Unit, Department of Obstetrics and Gynecology, Faculty of Medicine Siriraj Hospital, Mahidol University, 2 Wanglang Road, Bangkoknoi, Bangkok, 10700, Thailand. pattraporn.che@mahidol.ac.th.
BMC women's health
|November 14, 2023

概括
这项研究发现,结合克洛米芬酸盐 (CC) 和莱特醇,与单独的CC相比,在患有排卵功能障碍的不孕女性中,并没有显著改善排卵率. 需要进一步的研究来证实这些发现.
科学领域:
- 生殖内分泌学 生殖内分泌学
- 临床试验研究 临床试验研究
- 不孕症治疗 不孕症治疗
背景情况:
- 排卵功能障碍是不孕不育的常见原因之一.
- 克洛米芬酸盐 (CC) 和莱特是经常使用的排卵诱导剂.
- 将组合疗法与单一疗法进行比较对于优化治疗至关重要.
研究的目的:
- 为了比较克洛米芬酸盐 (CC) 加莱特与单独的CC对排卵诱导的疗效.
- 为了评估排卵率,周期特征和患有排卵功能障碍的不孕女性的受孕率.
主要方法:
- 一项随机对照试验,涉及100名患有排卵功能障碍的18-40岁不孕女性.
- 参与者被随机分配,从周期第3至第7天接受单独的CC (50毫克) +莱特 (2.5毫克) 或CC (50毫克).
- 排卵主要通过血清孕激素水平 (>3 ng/mL) 来评估.
主要成果:
- 结合组的排卵率为78%,单独使用CC组的排卵率为70%,没有统计学上显著的差异 (P > 0.05).
- 两组之间没有观察到子宫内膜厚度或主导毛囊数量的显著差异.
- 在任何治疗臂中都没有报告任何严重不良事件.
结论:
- 与单独的CC相比,CC和莱特醇的组合在诱导排卵的过程中没有显著的优势,对于排卵功能障碍的女性来说,在单个周期内诱导排卵.
- 该研究的有限样本大小用于活产分析,需要进一步调查.
- 需要进行额外的研究来验证和扩展这些发现.
相关概念视频
 01:28
Infertility in Females
325
Female infertility is defined as the inability to conceive after a year of regular, unprotected intercourse and affects about 10–15% of couples worldwide. The primary cause of female infertility is ovulatory disorders, which hinder the release of eggs. These disorders can be classified as hypothalamic amenorrhea, polycystic ovarian syndrome (PCOS), premature ovarian failure, and hyperprolactinemic anovulation disorders.
Endometriosis, a condition characterized by abnormal growth of...
Endometriosis, a condition characterized by abnormal growth of...
325
 01:24
In Vitro Fertilization
301
In vitro fertilization (IVF) is a form of assisted reproductive technology where an egg is fertilized with sperm in a controlled laboratory environment before transferring the resulting embryo into the uterus. This process is designed to help individuals and couples experiencing difficulties conceiving.
The IVF process begins with ovarian stimulation, during which reproductive endocrinologists prescribe hormonal medications to stimulate the ovaries to produce multiple eggs instead of the single...
The IVF process begins with ovarian stimulation, during which reproductive endocrinologists prescribe hormonal medications to stimulate the ovaries to produce multiple eggs instead of the single...
301
 01:27
Ovarian Cycle
1.3K
The menstrual cycle includes a critical component known as the ovarian cycle, which undergoes two main phases each month—the follicular phase and the luteal phase. The follicular phase is variable and averaging around 14 days. Ovulation, triggered by a surge in luteinizing hormone (LH), marks the transition between the two phases. The second phase, the luteal phase, is relatively consistent, lasting approximately 14 days, and is marked by the activity of the corpus luteum. While a cycle...
1.3K
 02:07
Oogenesis
63.8K
In human women, oogenesis produces one mature egg cell or ovum for every precursor cell that enters meiosis. This process differs in two unique ways from the equivalent procedure of spermatogenesis in males. First, meiotic divisions during oogenesis are asymmetric, meaning that a large oocyte (containing most of the cytoplasm) and minor polar body are produced as a result of meiosis I, and again following meiosis II. Since only oocytes will go on to form embryos if fertilized, this unequal...
63.8K
 01:57
Meiosis II
183.5K
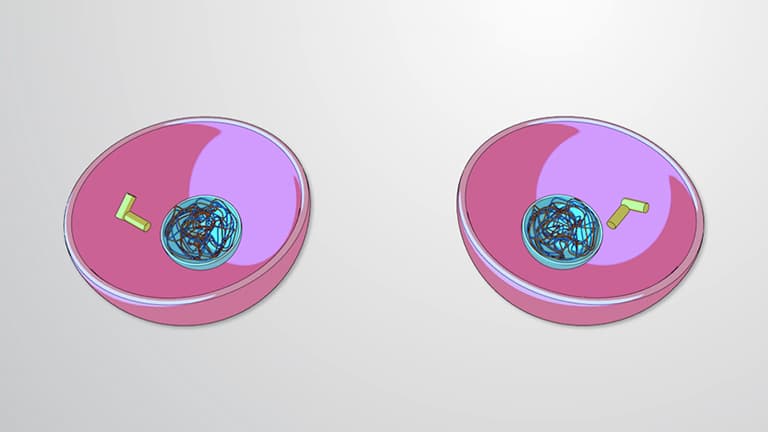
Meiosis II is the second and final stage of meiosis. It relies on the haploid cells produced during meiosis I, each of which contain only 23 chromosomes—one from each homologous initial pair. Importantly, each chromosome in these cells is composed of two joined copies, and when these cells enter meiosis II, the goal is to separate such sister chromatids using the same microtubule-based network employed in other division processes. The result of meiosis II is two haploid cells, each...
183.5K
 01:30
Hormonal Control of the Ovarian Cycle
536
The ovarian cycle is meticulously regulated by the hypothalamic-pituitary-gonadal axis. This cycle orchestrates the release of a mature oocyte, essential for reproduction.
Before puberty, the hypothalamus releases GnRH in a low frequency, low amplitude pulsatile manner. This along with the immature hypothalamic-pituitary-gonadal axis activity, results in low estrogen levels and the absence of a fully functional ovarian cycle. At puberty, GnRH secretion increases in both frequency and...
Before puberty, the hypothalamus releases GnRH in a low frequency, low amplitude pulsatile manner. This along with the immature hypothalamic-pituitary-gonadal axis activity, results in low estrogen levels and the absence of a fully functional ovarian cycle. At puberty, GnRH secretion increases in both frequency and...
536