

对于反射性辅心性昏迷的心脏神经衰变:中期的安全性,有效性和患者的接受度
Piotr Kulakowski1, Jakub Baran1, Agnieszka Sikorska1
1Centre of Postgraduate Medical Education, Department of Cardiology, Grochowski Hospital, Warsaw, Poland.
Heart rhythm
|November 30, 2023

概括
心脏神经衰竭 (CNA) 提供了超过80%的中期疗效,用于反射辅助性失眠,没有急性并发症. 虽然鼻高心率是一个常见的问题,但患者接受率仍然很高,这使得CNA成为一种有价值的治疗选择.
科学领域:
- 心脏病学 心脏病学
- 电子生理学 电子生理学
- 自主神经系统的自主神经系统
背景情况:
- 反射辅助性昏迷对当前的治疗方法构成了挑战.
- 心脏神经衰变 (CNA) 显示出有希望的结果,但缺乏中期安全性和疗效数据.
- 了解CNA的长期结果对于患者管理至关重要.
研究的目的:
- 评估心脏神经衰竭 (CNA) 的中期安全性和有效性.
- 为了评估患者接受CNA的反射辅助性失眠.
- 提供关于CNA的耐用性和潜在并发症的数据.
主要方法:
- 未来的观察性单中心研究.
- 连续115名患有反射性缩性昏迷的患者接受了CNA.
- 最低1年的随访,随访时间中位数为28个月.
主要成果:
- 83%的患者在中期随访时仍然没有昏迷.
- 在复发病例中,昏迷负担显著降低 (P = .015).
- 最常见的并发症是鼻节律加速 (27%),7%通过药物治疗;96%的患者接受.
结论:
- 心脏神经衰竭 (CNA) 在反射性辅助性中显示出高的中期疗效 (>80%).
- 没有急性并发症,患者接受率非常高.
- 不适当的鼻高心率是主要的慢性并发症,在大多数情况下是可以控制的.


相关概念视频
 01:24
Antiarrhythmic Drugs: Class II Agents as β-Adrenergic Blockers
747
Adrenergic stimulation generally impacts cardiac rate and rhythm. Specifically, stimulation of the β-adrenoceptors triggers an increase in intracellular calcium ion influx and pacemaker currents, which may cause arrhythmias. Catecholamines like adrenaline also demonstrate β2-adrenoceptor-mediated hypokalemia, impacting cardiac action potential and disrupting the normal cardiac rhythm. Class II antiarrhythmic drugs are β-adrenoceptor antagonists or β-blockers, which...
747
 01:26
Heart Failure Drugs: Inhibitors of Renin-Angiotensin System
436
The activation of the sympathetic nervous system and the renin-angiotensin-aldosterone system (RAAS) contributes to cardiac remodeling, and inhibiting the RAAS is a pharmacological target in heart failure management. As a result, neurohumoral modulation is a crucial treatment principle for managing heart failure. This approach involves using medications like ACE inhibitors (ACEIs), angiotensin receptor blockers (ARBs), β-blockers, mineralocorticoid receptor antagonists (MRAs), and neutral...
436
 01:22
Antiarrhythmic Drugs: Class I Agents as Sodium Channel Blockers
1.4K
Class I antiarrhythmic drugs are used to treat various types of arrhythmias or irregular heart rhythms. These drugs block the sodium (Na+) channels in the cardiac cells, thereby affecting the movement of electrical impulses across the heart. Class I antiarrhythmic drugs are divided into three subgroups: Class IA, Class IB, and Class IC, each with distinct mechanisms of action and effects on the heart.
Class 1A Antiarrhythmic Drugs: These drugs work by moderately blocking sodium channels,...
Class 1A Antiarrhythmic Drugs: These drugs work by moderately blocking sodium channels,...
1.4K
 01:30
Cardiac Action Potential
1.5K
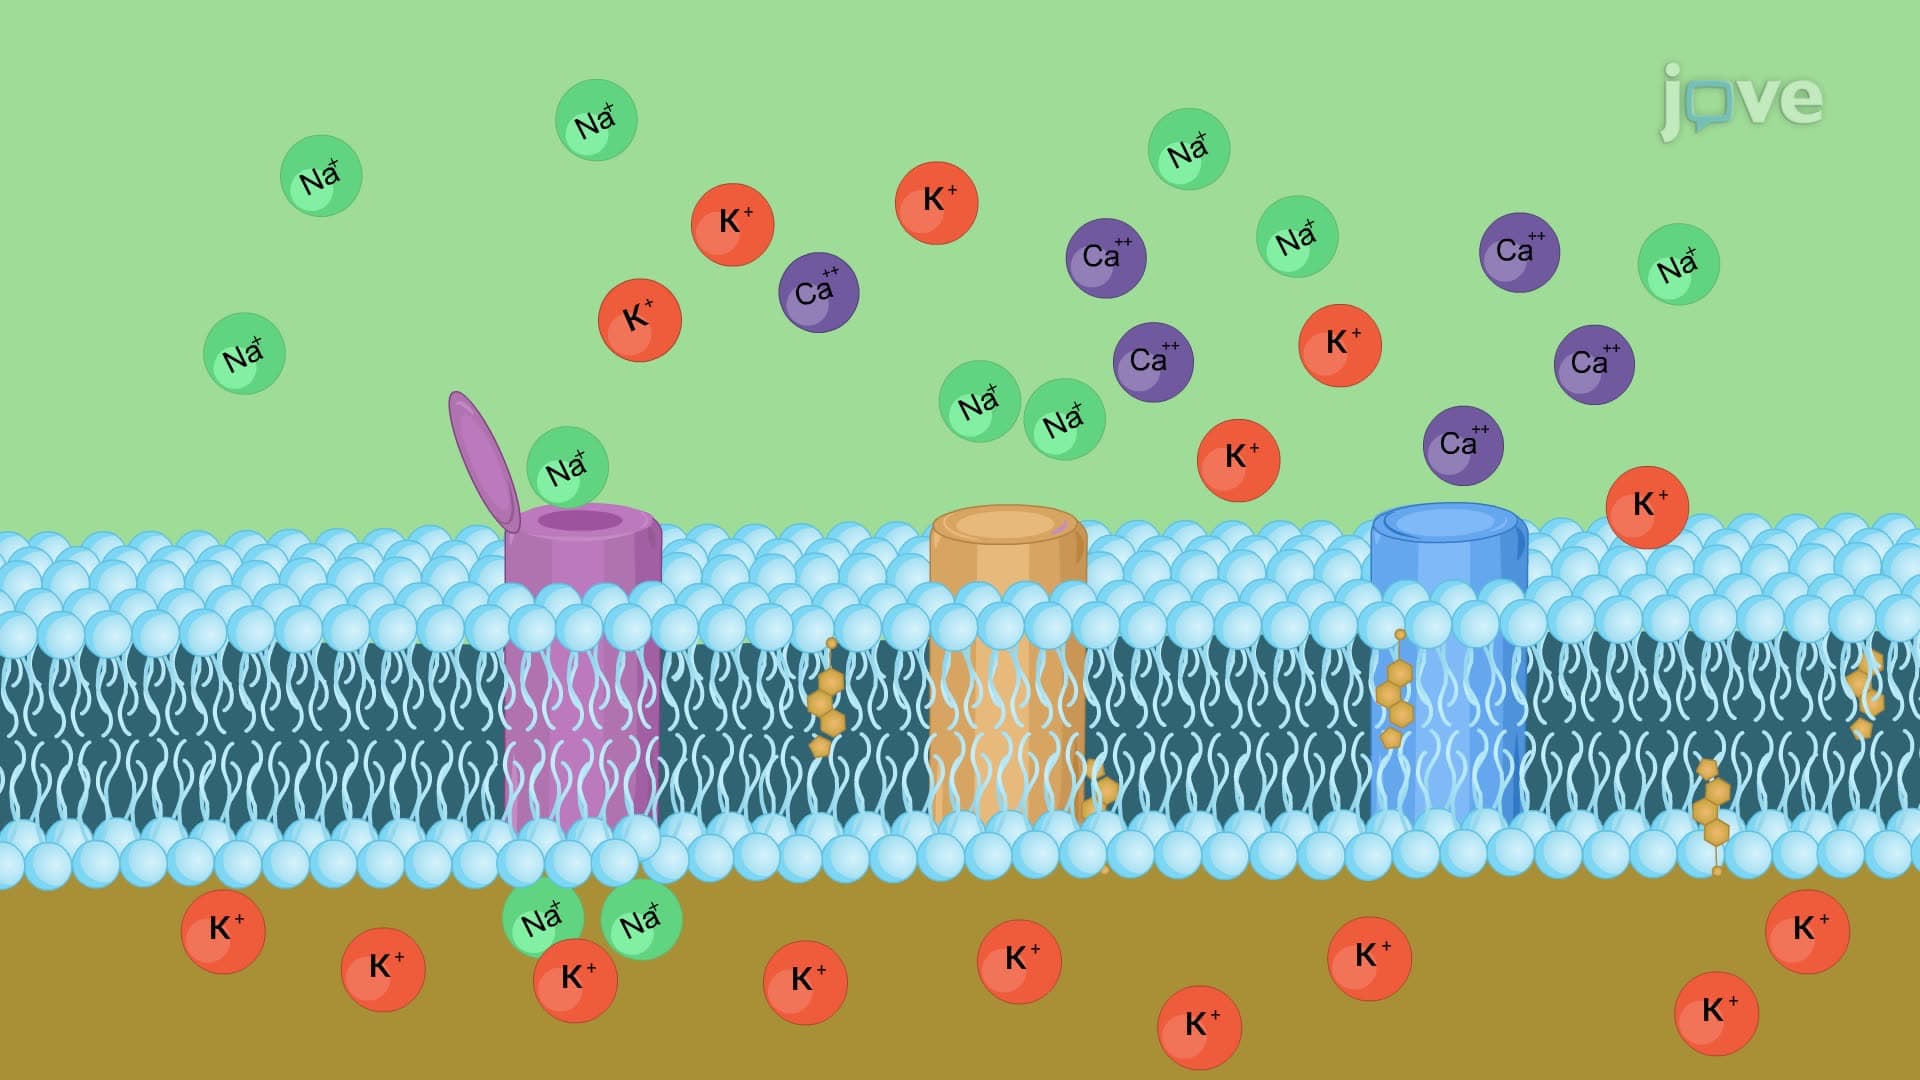
Cardiac action potentials are essential for proper heart function, enabling the rhythmic contractions needed for adequate blood circulation. Nodal cells and Purkinje fibers, specialized for electrical conduction, generate these action potentials.
The cardiac action potential process involves a series of phases characterized by the movement of ions across the cardiac cell membranes, leading to the depolarization and repolarization of the cardiac myocytes.
Ionic Basis of Cardiac Action Potentials
The cardiac action potential process involves a series of phases characterized by the movement of ions across the cardiac cell membranes, leading to the depolarization and repolarization of the cardiac myocytes.
Ionic Basis of Cardiac Action Potentials
1.5K
 01:25
ECG Interpretation of Arrhythmias II: Atrial, Junctional and Ventricular Arrhythmias
21
Arrhythmia is a condition characterized by an irregular heart rhythm, with ECG changes that differ based on its origin and nature. The types of arrhythmias discussed below include atrial, junctional, and ventricular arrhythmias.Atrial ArrhythmiasPremature Atrial Complexes (PACs): PACs are early atrial beats caused by stress, caffeine, alcohol, electrolyte imbalances, hypoxia, hyperthyroidism, or certain medications (e.g., bronchodilators and decongestants). The ECG shows early P waves with an...
21
 01:25
Antianginal Drugs: Calcium Channel Blockers and Ranolazine
533
Angina pectoris, a primary symptom of ischemic heart disease, requires careful pharmacological interventions. In this context, calcium channel blockers (CCBs) and ranolazine have emerged as crucial pharmacotherapeutic agents, providing deep insights into the complexities of angina management.
CCBs, a diverse class that includes dihydropyridines (nifedipine) and diphenylalkylamines (verapamil and diltiazem), exert their effect by blocking calcium channels in cardiac and smooth muscle cells. This...
CCBs, a diverse class that includes dihydropyridines (nifedipine) and diphenylalkylamines (verapamil and diltiazem), exert their effect by blocking calcium channels in cardiac and smooth muscle cells. This...
533