相关实验视频
Updated: Jul 25, 2026
07:24
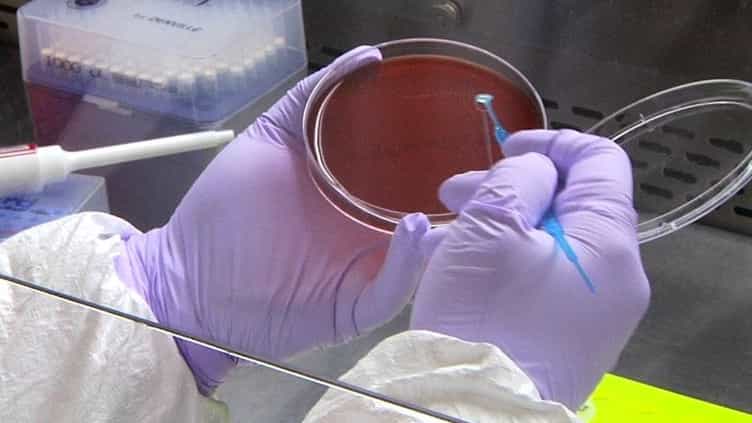
Pseudomonas aeruginosa Induced Lung Injury Model
Published on: October 29, 2014
18.5K
肺部和肺外模型的结血症相关的急性肺损伤的比较
1The Second Clinical College of Guangzhou University of Chinese Medicine, Guangzhou, Guangdong, China.
Physiological research
|January 12, 2024

概括
在老鼠体内灌注脂多糖 (LPS) 提供了与败血症相关的急性肺损伤 (ALI) 的稳定和可重复模型. 这种方法优于结绑定和刺穿或静脉内射LPS注射来研究ALI机制.
科学领域:
- 败血症的研究研究.
- 肺部医学 肺部医学
- 动物建模动物建模
背景情况:
- 败血症相关的急性肺损伤 (ALI) 是败血症的一个关键并发症.
- 开发稳定和可再生的动物模型对于了解ALI病原和测试干预措施至关重要.
- 现有的模型,包括结和刺穿 (CLP) 和静脉输入脂多糖 (LPS) 给药,对肺损伤机制的一致性和相关性有局限性.
研究的目的:
- 为了比较不同老鼠模型的稳定性和可重复性,毒症诱导的ALI.
- 确定最佳的动物模型来研究与败血症相关的ALI.
- 在各种败血症模型中评估肺与肺外损伤机制.
主要方法:
- 成年雄性Sprague-Dawley大鼠接受了结和穿孔 (CLP1,CLP2),静脉内LPS (IV-LPS10,IV-LPS20) 或内内LPS (IT-LPS10,IT-LPS20) 插入.
- 每个模型都包括了虚假组.
- 在7天内评估了生存率.
- 支气管洗液 (BALF) 和肺组织在建模后4,24和48小时收集,以分析炎症标志物 (IL-6,TNF-alpha),蛋白质度,MPO活性,HMGB1表达和组织病理学.
主要成果:
- 在LPS (IT-LPS) 内部灌注导致明显的肺组织病理学和炎症性排泄.
- 与IV-LPS和IT-LPS20组相比,IT-LPS10组的生存率更高.
- 在CLP和IV-LPS组中没有观察到显著的肺损伤,尽管一些组的死亡率很高.
- IT-LPS模型在诱导ALI时表现出更大的稳定性和可重复性.
结论:
- 与肺外模型相比,LPS的内灌注是一种更稳定和可重复的模型,用于诱导与败血症相关的ALI.
- 这种模型允许直接调查败血症中肺损伤机制.
- 使用IT-LPS模型进行进一步的研究是有必要的,以阐明ALI的病原性和开发有效的治疗方法.

相关概念视频
 01:21
Acute Respiratory Failure-I
Acute respiratory failure is a condition characterized by the inability of the lungs to perform their primary function: gas exchange. This failure leads to insufficient oxygen levels (hypoxemia) in the blood, elevated carbon dioxide levels (hypercapnia), or both, causing critical impairment in organ function.
Definition: It is defined by specific criteria based on blood gas measurements. Hypoxemia happens when the partial pressure of oxygen (PaO2) falls below 60 mmHg. At the same time,...
Definition: It is defined by specific criteria based on blood gas measurements. Hypoxemia happens when the partial pressure of oxygen (PaO2) falls below 60 mmHg. At the same time,...
 01:26
Flail Chest-II
Managing flail chest, a condition characterized by a segment of the chest wall moving independently from the rest of the thoracic cage, requires a comprehensive approach. It includes a thorough assessment of the patient's condition, a diagnostic evaluation to determine the extent of the injury, and the implementation of appropriate medical interventions tailored to the individual's needs.
Assessment:
1. Clinical Evaluation:
History:
Assessment:
1. Clinical Evaluation:
History:
 01:26
Pneumothorax-I
A pneumothorax is a condition where air builds up in the space between the lung and the chest wall, causing the lung to collapse. This condition arises when air enters the space between the parietal and visceral pleura, disrupting the negative pressure essential for lung inflation. This can lead to a partial or complete collapse of the lung.
Pneumothorax can be even further classified as spontaneous, traumatic, and tension pneumothorax.
Pneumothorax can be even further classified as spontaneous, traumatic, and tension pneumothorax.
 01:27
Pneumothorax-II
Pneumothorax is a medical condition defined by the buildup of air in the pleural space between the lungs and the chest wall. This accumulation of air can lead to partial or complete lung collapse, resulting in a range of clinical manifestations. Understanding the clinical presentation and effective management strategies is crucial for healthcare professionals in providing timely and appropriate care to individuals with pneumothorax.
Clinical Manifestations:
Clinical Manifestations:
 01:08
Pneumothorax II: Pathophysiology
Pneumothorax means the presence of air in the pleural space — the thin potential gap between the visceral and parietal pleura. This condition disrupts the normal pressure balance that keeps the lungs inflated, leading to partial or complete collapse of the affected lung.Normal physiologyUnder normal conditions, the pleural space maintains a slightly negative intrapleural pressure, which keeps the lungs expanded against the chest wall. This negative pressure creates a delicate balance between...