扩散加权成像显示,在异常性脑内高血压中,淋巴清除功能受损
相关实验视频
Updated: Jul 1, 2026
10:13
Cannula Implantation into the Cisterna Magna of Rodents
Published on: May 23, 2018
44.9K
Derrek Schartz1, Alan Finkelstein2, Nhat Hoang2
1From the Department of Imaging Sciences (D.S., A.F., N.H., G.S., J.Z.), University of Rochester Medical Center, Rochester, New York derrek_schartz@urmc.rochester.edu.
AJNR. American journal of neuroradiology
|January 18, 2024

概括
异常性内高血压 (IIH) 患者表现出淋巴清除受损,这是疾病严重程度的关键指标. 先进的扩散计量成像可以帮助诊断IIH并监测治疗的有效性.
科学领域:
- 神经学 神经学
- 放射学 放射学是一门学科.
- 生物医学成像技术 生物医学成像技术
背景情况:
- 绝症性内高血压 (IIH) 的确切原因尚未完全理解.
- 一个主要的理论表明,大脑淋巴清除受损导致IIH.
- 目前用于量化人类大脑淋巴活动的方法是有限的.
研究的目的:
- 用先进的扩散权重成像 (DWI) 来评估IIH患者的淋巴清除.
- 在IIH中调查淋巴清除和临床严重程度之间的关系.
- 探索DWI衍生参数作为IIH的潜在诊断和监测工具.
主要方法:
- 扩散计量成像 (DWI) 用于评估在特定的大脑路径上的扩散性.
- 扩散性作为一个替代标志物用于淋巴功能.
- 患有IIH的患者 (n=99) 与健康的对照人群 (n=6) 相比较,将淋巴清除与临床指标 (如 papilledema等级和开口压力) 相关联.
主要成果:
- 与健康对照组相比,IIH患者的淋巴清除显著减少.
- 在IIH患者中,减少淋巴清除和增加 papilledema 等级之间发现了显著的关联.
- 健康对照组和IIH患有低度 papilledema的患者的淋巴清除比患有高度 papilledema的患者更高.
结论:
- 患有IIH的患者表现出淋巴清除受损,与临床疾病严重程度直接相关.
- 从DWI衍生的指标为诊断IIH和评估治疗反应提供了一个有希望的方法.
- 这项研究强调了先进的成像技术在理解IIH病理生理学的有用性.

相关概念视频
 01:14
Increased Intracranial Pressure l: Introduction
Intracranial hypertension is a sustained elevation of intracranial pressure (ICP) above 22 mm Hg. In supine adults, normal ICP is ~7–15 mm Hg.The rigid, nonexpandable cranium contains three components—brain tissue, blood, and cerebrospinal fluid (CSF)—that total ~1,700 mL in a typical adult: 1,400 mL brain (~80%), 150 mL blood (~10%), and 150 mL CSF (~10%). According to the Monro–Kellie doctrine, total intracranial volume is effectively fixed. When one component expands, CSF and venous blood...
 01:29
Increased Intracranial Pressure ll: Pathophysiology
Increased intracranial pressure (ICP) refers to a potentially life-threatening rise in pressure inside the skull. This usually happens when there is a major change in the volume of brain tissue, blood, or cerebrospinal fluid (CSF) — the three components inside the skull. According to the Monro-Kellie doctrine, if the volume of one component increases, the volumes of the other components must decrease to maintain normal pressure. If this does not happen, ICP rises.The process often begins with...
 01:19
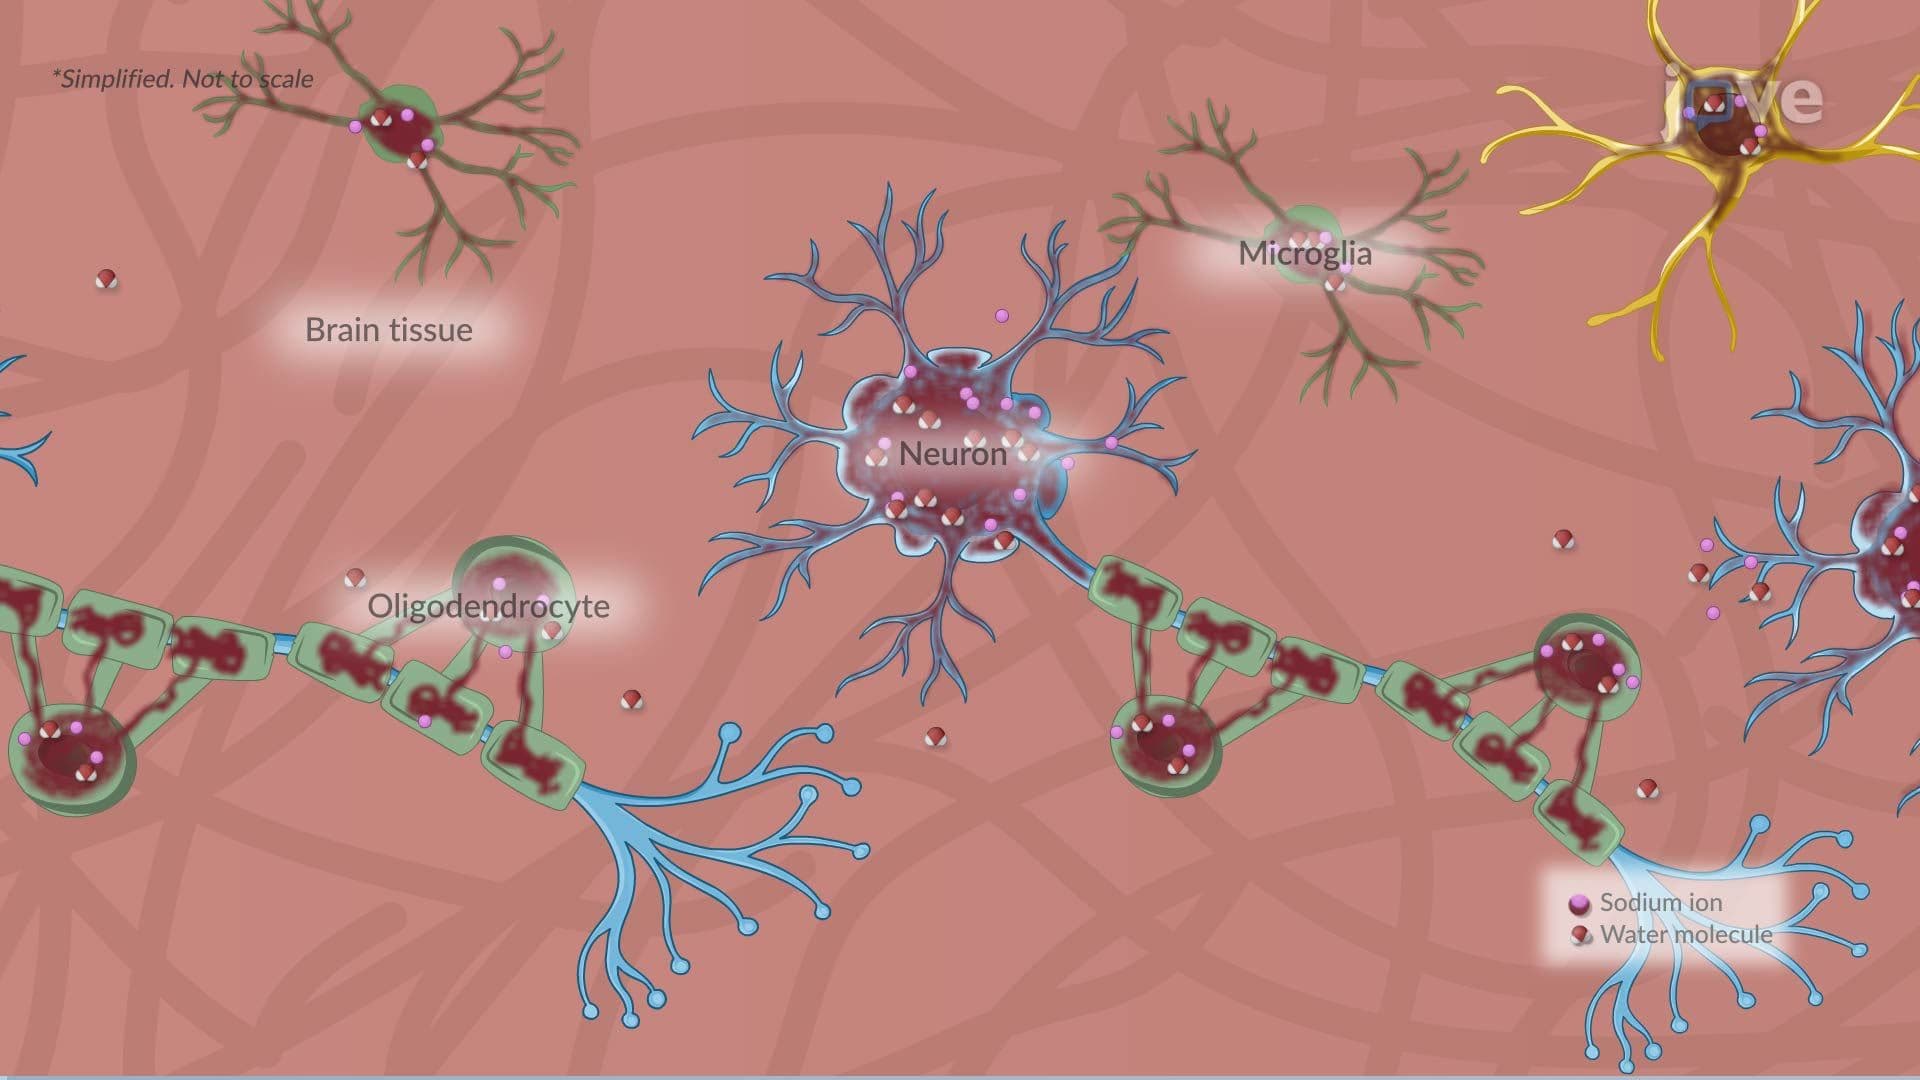
Cerebral Edema l: Introduction
Cerebral edema is a pathological increase in brain water content that disrupts intracranial pressure regulation and impairs neurological function. Because the cranial vault is rigid, even modest increases in tissue volume can compromise cerebral perfusion, distort neural structures, and initiate secondary injury. Cerebral edema develops through four principal mechanisms: vasogenic, cytotoxic, interstitial, and ionic.Vasogenic EdemaVasogenic edema arises from disruption of the blood–brain...
 01:22
Cerebral Edema ll: Pathophysiology
Vasogenic edema is a major form of cerebral edema characterized by abnormal accumulation of fluid in the brain’s extracellular space due to disruption of the blood–brain barrier (BBB). The BBB is a specialized structure composed of endothelial cells connected by tight junctions, supported by astrocytic endfeet and a basement membrane. Under normal conditions, it tightly regulates the movement of ions, proteins, and solutes between the bloodstream and brain parenchyma. When this barrier loses...
 01:21
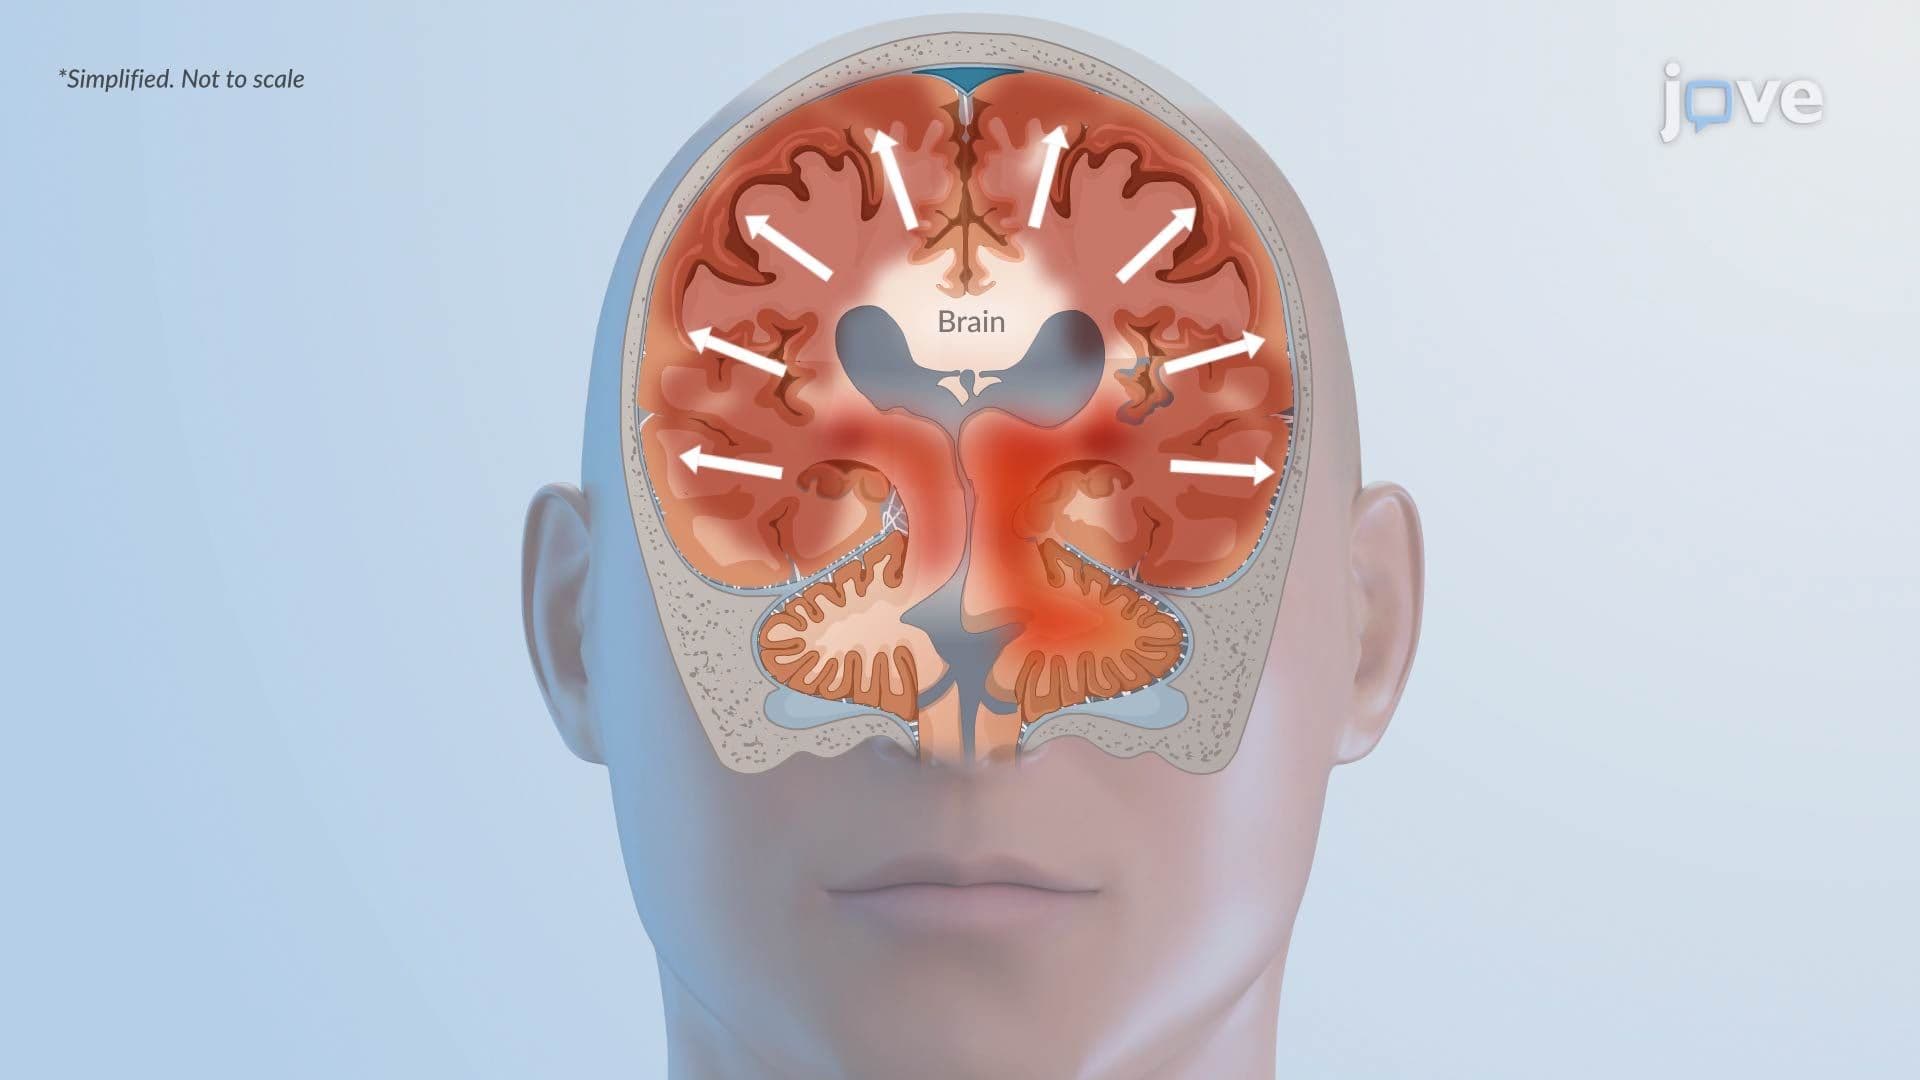
Cytotoxic Edema: Pathophysiology
Cytotoxic edema is a form of cerebral edema characterized by intracellular swelling of neurons, astrocytes, and other glial cells. It develops when the mechanisms responsible for maintaining ionic gradients across the cell membrane become impaired. Under normal physiological conditions, the sodium–potassium ATPase actively transports sodium ions out of the cell and potassium ions into the cell, preserving osmotic balance and enabling electrical signaling. This pump requires a continuous supply...