大脑胀与心脏病发作大小:一个有问题的评论

J Marc Simard1,2,3, Bradley Wilhelmy1, Natalya Tsymbalyuk1
1Department of Neurosurgery, University of Maryland School of Medicine, Baltimore, MD 21201, USA.
Brain sciences
|March 28, 2024

概括
脑中风后的大脑胀是预测结果的关键因素,但目前的治疗方法有限. 新的研究侧重于独立于心脏病发作大小的机制,为治疗大脑胀提供了更好的治疗方法的希望.
科学领域:
- 神经科学是一个神经科学.
- 神经学 神经学
- 病理学 病理学 病理学
背景情况:
- 大脑胀是影响人类中风患者神经结果和死亡率的关键因素.
- 现有的治疗大脑胀的方法很少,因为对其潜在机制的理解有限.
- 临床前中风研究主要侧重于减少心脏病发作的大小,对治疗中风后脑胀的翻译价值有限.
研究的目的:
- 为了突出显示大脑胀是中风中的一个独特的病理实体,与心脏病发作大小分开.
- 审查研究大脑胀机制的新方法,独立于心脏病发作大小的减少.
- 为了确定治疗后缺血性脑胀的潜在治疗点.
主要方法:
- 对中风模型中的大脑保护现有文献的综述.
- 对专注于不同于心脏病发作大小的大脑胀机制的研究进行分析.
- 评估新型研究方法的翻译相关性.
主要成果:
- 人类的大脑胀通常在心脏病发作大小稳定后的几天内表现出来,需要独立于心脏病发作大小减小的治疗.
- 大脑和胀是独特的病理过程,具有独特的分子和细胞驱动因素.
- 研究方法的进步使得研究大脑胀的研究能够独立于心脏病发作的大小.
结论:
- 针对独立于心脏病发作大小的大脑胀机制对于开发有效的中风治疗方法至关重要.
- 了解大脑胀作为一个独特的病理实体,为治疗干预开辟了新的途径.
- 审查的新方法为管理后缺血性脑胀提供了显著的翻译潜力.
相关概念视频
 01:15
Ischemic Stroke ll: Pathophysiology
68
An ischemic stroke occurs when a cerebral blood vessel becomes obstructed, most often by a thrombus or embolus, interrupting the delivery of oxygen and glucose to brain tissue. Because neurons rely on continuous aerobic metabolism, energy failure begins within minutes of reduced perfusion. The region receiving the least blood flow becomes the infarct core, an area of irreversible cellular death. Surrounding this core lies the penumbra, a zone of hypoperfused but still viable tissue that is...
68
 01:29
Hemorrhagic Stroke ll: Pathophysiology
52
A hemorrhagic stroke develops when a cerebral blood vessel ruptures, allowing blood to escape into the surrounding brain tissue, as in intracerebral hemorrhage (ICH), or into the subarachnoid space, as in subarachnoid hemorrhage (SAH). Because the skull is a rigid compartment, the sudden presence of extravascular blood rapidly increases intracranial pressure and compresses adjacent neural structures, leading to immediate tissue injury and impaired cerebral perfusion.Mass Effect and Primary...
52
 01:29
Increased Intracranial Pressure ll: Pathophysiology
39
Increased intracranial pressure (ICP) refers to a potentially life-threatening rise in pressure inside the skull. This usually happens when there is a major change in the volume of brain tissue, blood, or cerebrospinal fluid (CSF) — the three components inside the skull. According to the Monro-Kellie doctrine, if the volume of one component increases, the volumes of the other components must decrease to maintain normal pressure. If this does not happen, ICP rises.The process often begins...
39
 01:19
Cerebral Edema l: Introduction
34
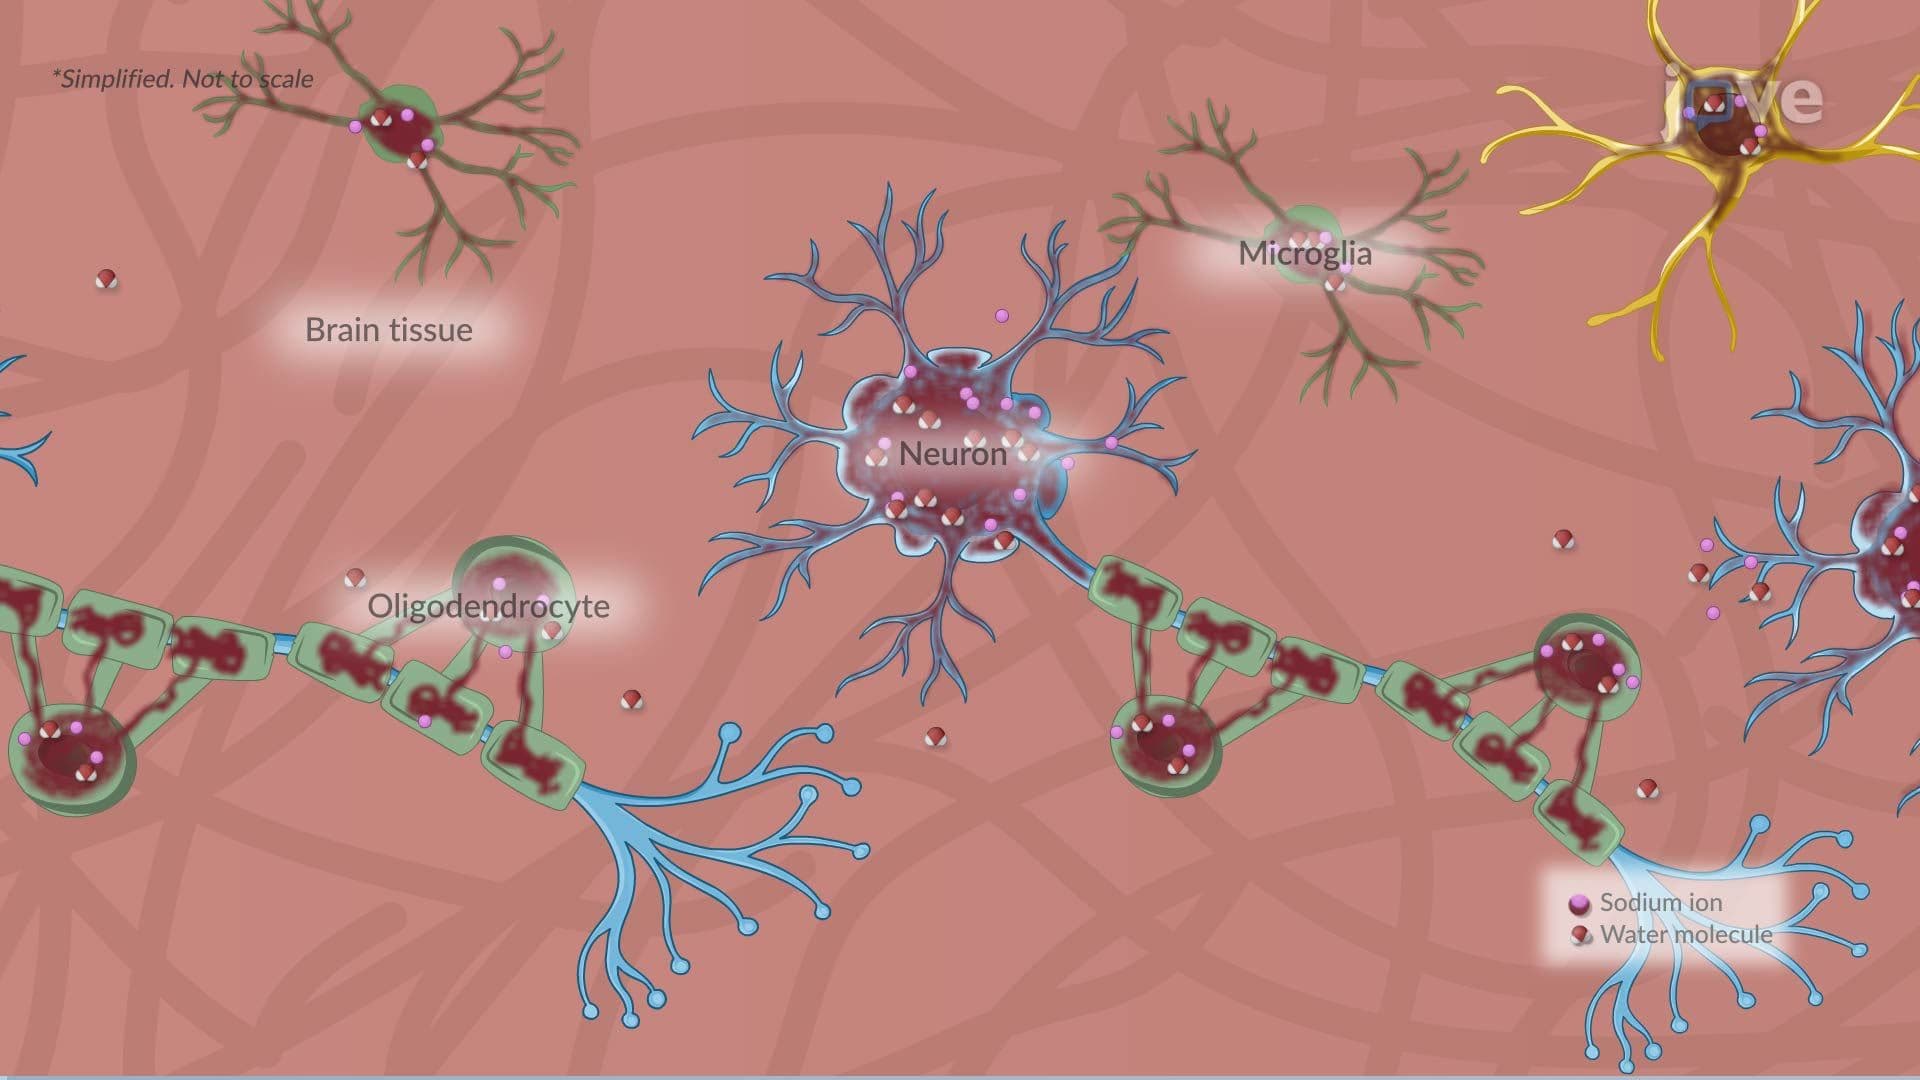
Cerebral edema is a pathological increase in brain water content that disrupts intracranial pressure regulation and impairs neurological function. Because the cranial vault is rigid, even modest increases in tissue volume can compromise cerebral perfusion, distort neural structures, and initiate secondary injury. Cerebral edema develops through four principal mechanisms: vasogenic, cytotoxic, interstitial, and ionic.Vasogenic EdemaVasogenic edema arises from disruption of the blood–brain...
34
 01:22
Cerebral Edema ll: Pathophysiology
31
Vasogenic edema is a major form of cerebral edema characterized by abnormal accumulation of fluid in the brain’s extracellular space due to disruption of the blood–brain barrier (BBB). The BBB is a specialized structure composed of endothelial cells connected by tight junctions, supported by astrocytic endfeet and a basement membrane. Under normal conditions, it tightly regulates the movement of ions, proteins, and solutes between the bloodstream and brain parenchyma. When this...
31
 01:21
Cytotoxic Edema: Pathophysiology
31
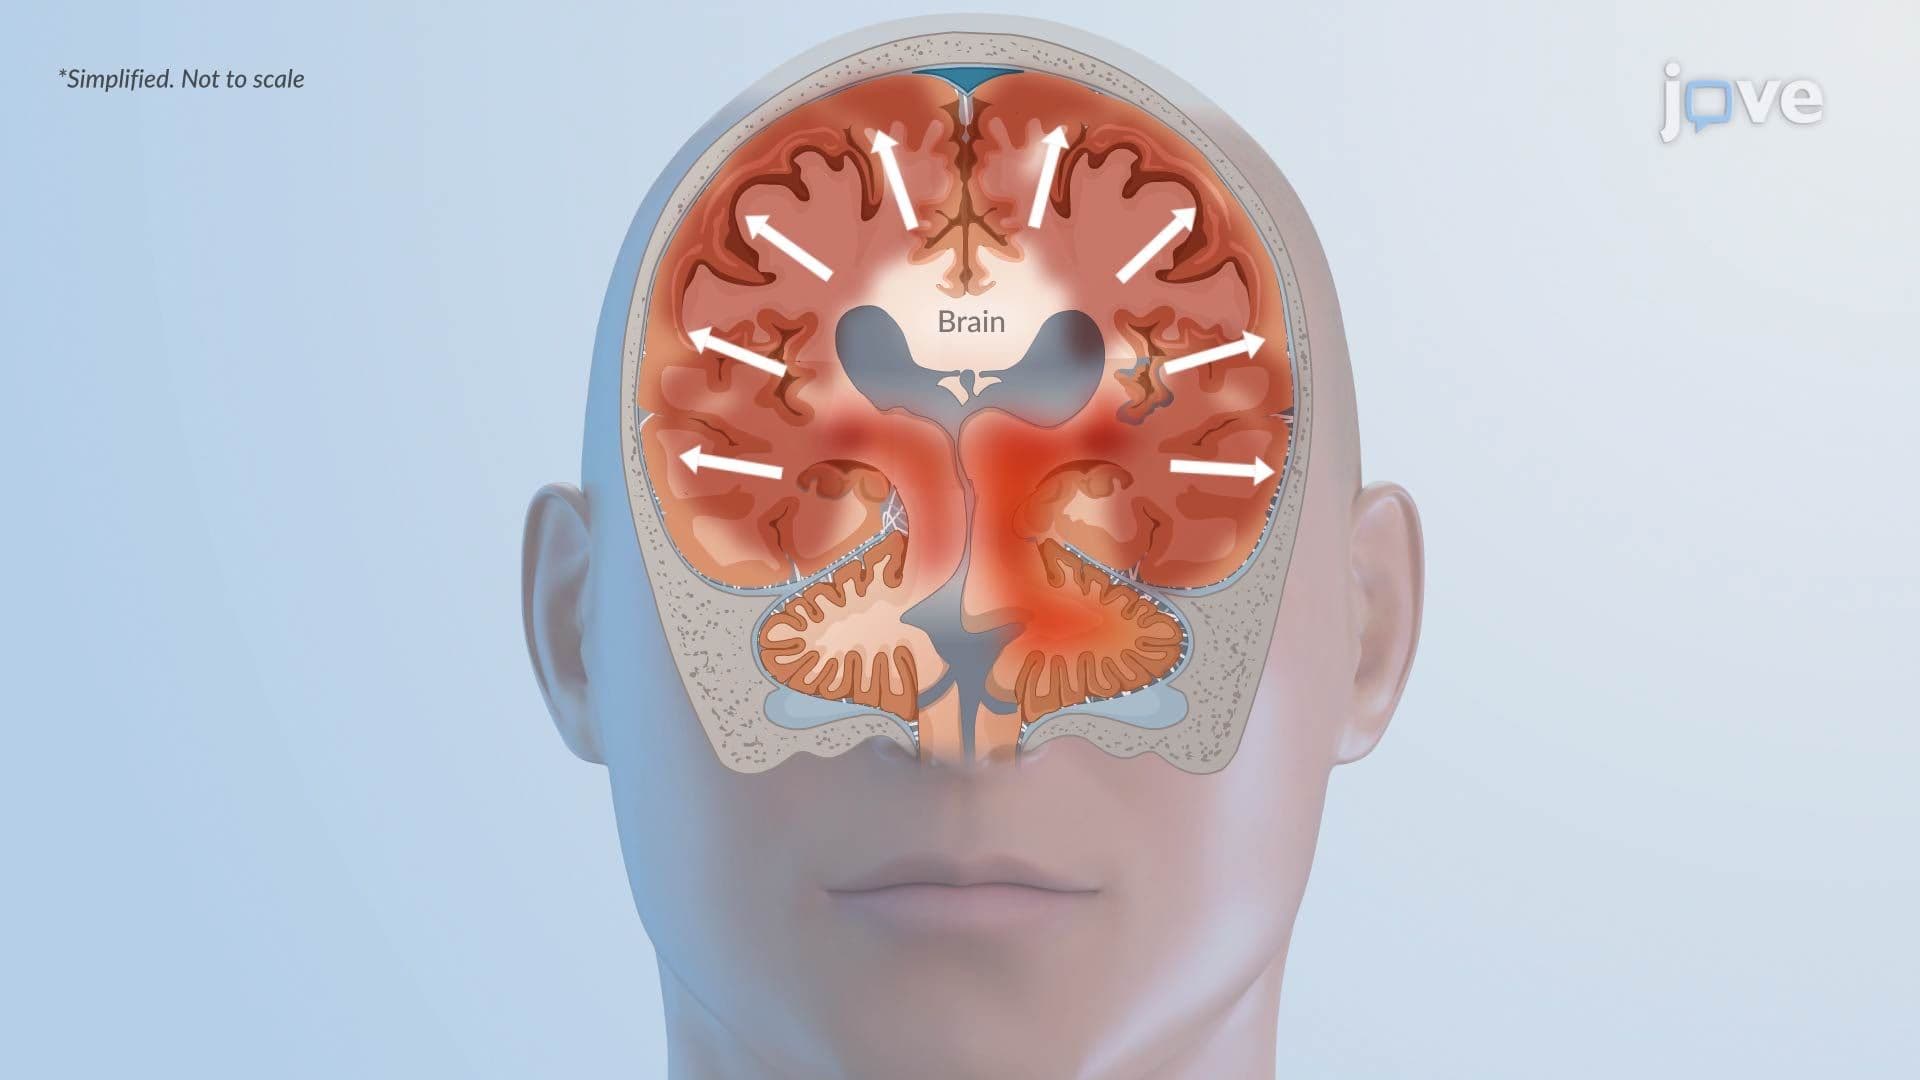
Cytotoxic edema is a form of cerebral edema characterized by intracellular swelling of neurons, astrocytes, and other glial cells. It develops when the mechanisms responsible for maintaining ionic gradients across the cell membrane become impaired. Under normal physiological conditions, the sodium–potassium ATPase actively transports sodium ions out of the cell and potassium ions into the cell, preserving osmotic balance and enabling electrical signaling. This pump requires a continuous...
31