

对不同比例的达黄 () - 陶伦 () 草药对之间的药理学差异的差异代谢物分析
Wang Xiang1, Huang Jianping1, Wang Yupeng2
1Department of Key Laboratory of "Qin Pharmaceutical" Research and Development, Shaanxi University of Traditional Chinese Medicine, Xianyang 712046, China.

概括
大黄 (Radix et Rhizoma Rhei Palmati) - 陶伦 (Semen Persicae) 药物治疗热和血液静止综合征的最佳比例为1:1. 不同的比例会显著影响治疗的疗效,因为代谢物形状不同.
科学领域:
- 药理学 药理学是指药理学的学科.
- 代谢学 代谢学 代谢学
- 传统中国医药 传统中国医药
背景情况:
- 大黄 (Radix et Rhizoma Rhei Palmati) 和陶 (Semen Persicae) 是传统中医药配方中的关键成分.
- 大黄-陶伦 (DT) 药物的疗效可以根据其成分草药的比例而有所不同.
- 了解这些疗效差异的物质基础对于临床应用至关重要.
研究的目的:
- 调查不同比例的大黄 (Radix et Rhizoma Rhei Palmati) - 陶 (Semen Persicae) 药物的不同疗效的物质基础.
- 确定关键的代谢物和代谢途径,与DT药物的治疗作用相关.
主要方法:
- 使用气体染色学-飞行时间质谱法 (GC-TOF/MS) 进行非目标代谢学分析.
- 分析的DT样本具有三种不同的Dahuang (DH) 与Taoren (TR) 的比例:1:1 (A组),2:3 (B组) 和3:2 (C组).
- 确定了差异性代谢物和相关的代谢途径.
主要成果:
- 在所有样本中检测到总共240种主要代谢物.
- 确定了41种不同代谢物,分布在9个代谢途径中.
- 四个关键途径,包括氨基酸生物合成 (氨酸,氨酸,氨酸,氨酸),黄类生物合成,不和脂肪酸生物合成和糖解/糖生成,与治疗热和血液静止综合征的疗效密切相关.
结论:
- 根据它们的成分比率,大黄-陶伦 (DT) 药物的疗效存在显著差异.
- 治疗热和血液静止综合征的最佳比率被确定为1:1 (大黄:陶伦).
- 代谢分析提供了对DT药物疗效的物质基础的见解.

相关概念视频
 01:16
Bioequivalence: Overview
Pharmaceutical equivalents, by definition, are drug products with the same active ingredient in the same quantities, encapsulated in identical dosage forms, and intended for the same administration routes. These pharmaceutical equivalents are deemed bioequivalent if the bioavailability of the active entity in the drug preparations is similar. Moreover, pharmaceutical equivalents demonstrating bioequivalence are also regarded as therapeutically equivalent. This means that when used as directed,...
 01:16
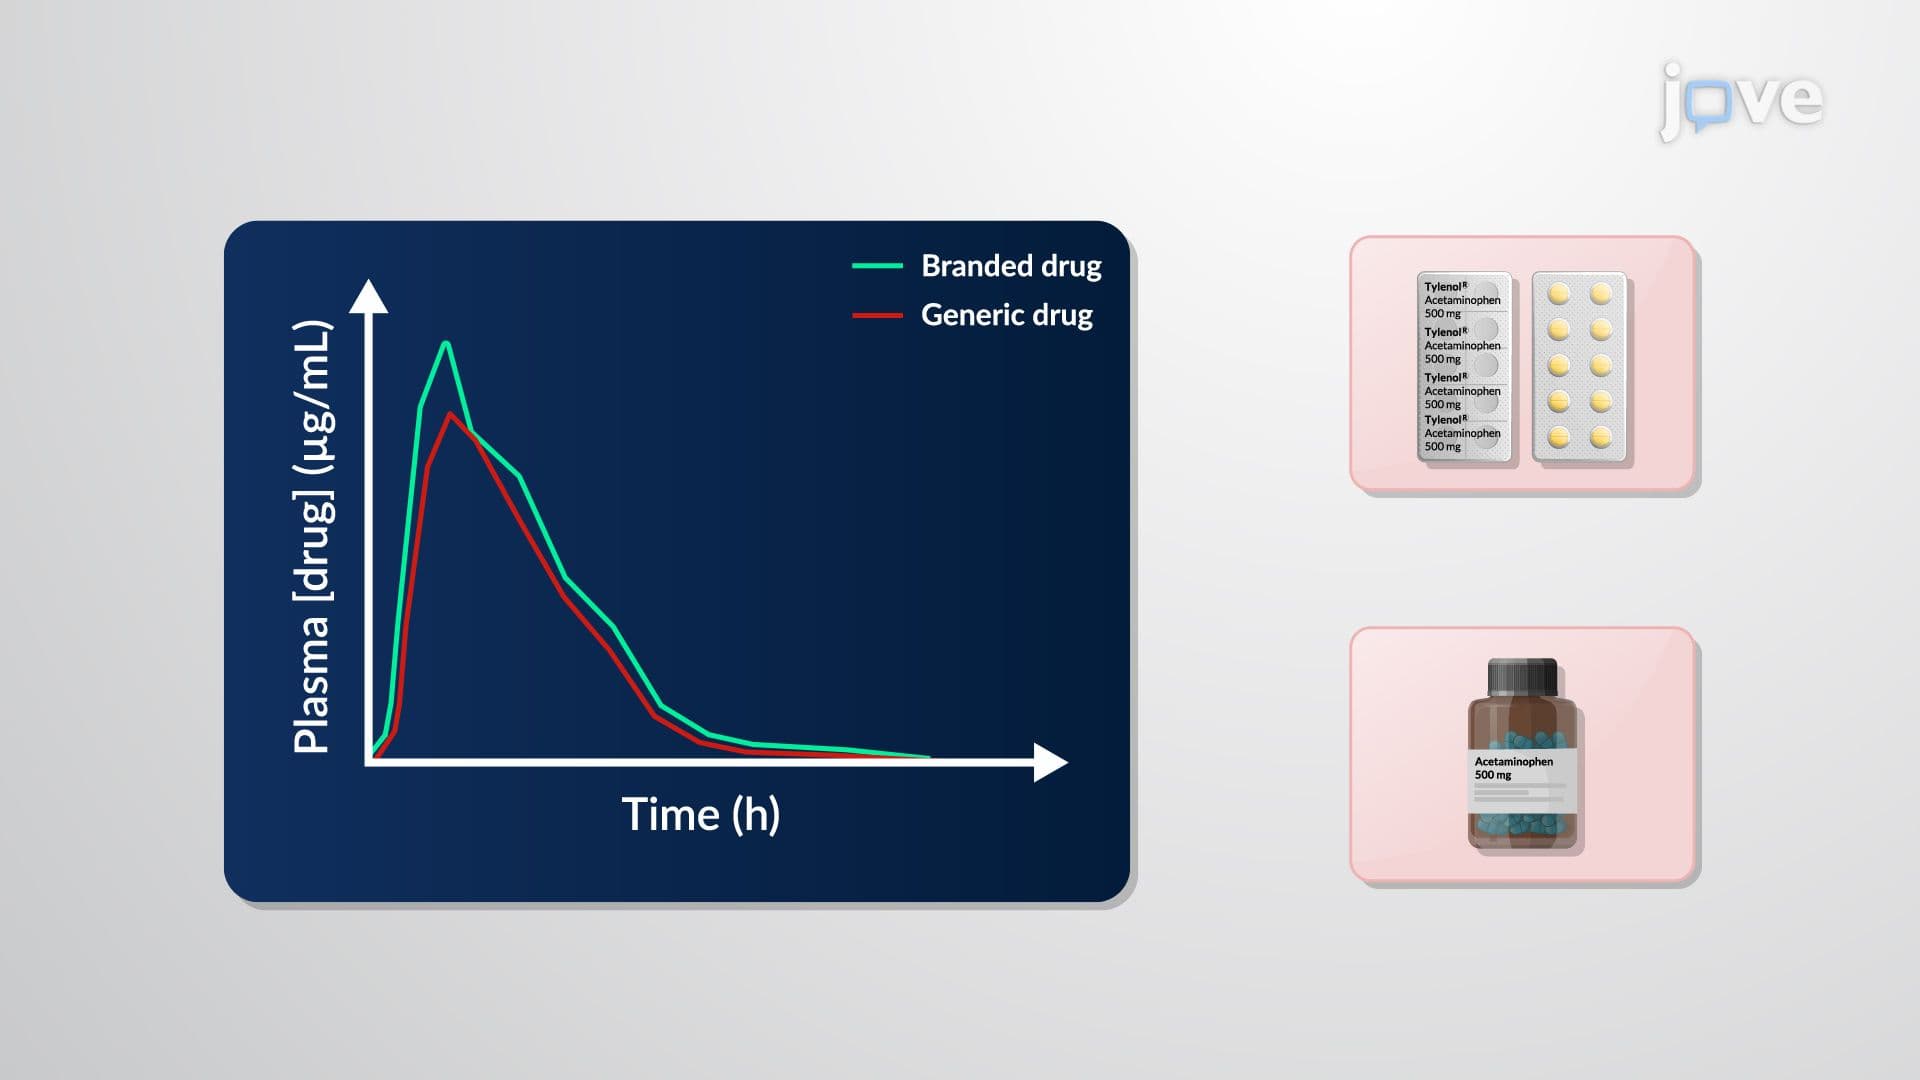
Bioequivalence Data: Statistical Interpretation
The statistical interpretation of bioequivalence data is a significant aspect of pharmaceutical research. Bioequivalence refers to the absence of any significant difference in the rate and extent to which the active ingredient in pharmaceutical products becomes available at the site of drug action when administered at the same molar dose under similar conditions. This helps determine if different drug products have similar absorption rates, ensuring their interchangeability.Statistical...
 01:14
Drug Dissolution: Requirements and Profile Comparison
The acceptance criteria for dissolution profile data are anchored in Q values, representing the percentage of drug dissolved within a specified period. This assessment unfolds in three stages:First Stage: The test passes if all six drug dosage units are equal to or greater than Q plus 5%; otherwise, the sample proceeds to the second stage.Second Stage: The average of twelve units must be equal to or greater than Q, with no unit falling below Q - 15% to pass; if not, it progresses to the final...
 01:26
Pharmaceutical Equivalents
As defined by regulatory standards, pharmaceutical equivalents require generic drug products to have identical dosage forms and chemically identical active pharmaceutical ingredients (APIs). They must adhere to compendial or applicable standards for potency, content uniformity, disintegration times, and dissolution rates. In the case of modified-release dosage forms, variations in drug content are permissible as long as the delivered amount remains consistent with the innovator drug product.
 01:27
Pharmaceutical Alternatives: Polymorphic Form-Related and Particle Size-Related Therapeutic Nonequivalence
Changes in polymorphic forms can significantly influence the bioavailability of poorly soluble drugs. Although the FDA defines pharmaceutical equivalence based on having the same active ingredient, dosage form, and route of administration, it does not automatically disqualify products with different polymorphic forms. This means two products with different polymorphs can still be deemed pharmaceutically equivalent. However, polymorphic differences can affect properties like wettability,...
 01:09
Bioequivalence of Drugs: Drugs with Multiple Indications
The concept of therapeutic equivalence (TE) in drugs with multiple indications is complex. A generic drug may be therapeutically equivalent to a brand-name product for one specific indication, but this doesn't necessarily mean it's equivalent for all other indications. Evidence of TE in one patient group and bioequivalence shown in healthy volunteers can support—but not confirm—TE for other indications. However, definitive proof requires individual clinical studies for each indication due to...