

打破功能性消化不良的障碍:一项系统性审查和对十二指肠紧结蛋白表达的元分析
Radu A Farcas1, Malaz Almasri2, Simona Grad1
12nd Department of Internal Medicine, "Iuliu Hatieganu" University of Medicine and Pharmacy, Cluj-Napoca, Romania.
Journal of neurogastroenterology and motility
|July 7, 2024

概括
这次元分析发现,功能性消化不良患者和对照人群之间紧结蛋白表达没有显著差异. 由于在FD中评估这些蛋白质的研究数量有限,需要进一步的研究.
科学领域:
- 胃肠病学 胃肠病学
- 分子生物学分子生物学
- 细胞生物学 细胞生物学
背景情况:
- 功能性消化不良 (FD) 与由于紧接 (TJ) 蛋白质中断而导致的十二指甲上皮屏障功能受损有关.
- 之前对FD患者TJ蛋白表达的研究已经产生了不一致的结果.
- 进行了系统性审查和元分析,以澄清TJ蛋白在FD病理生理学中的作用.
研究的目的:
- 系统地评估和定量合成与健康对照组相比,功能性消化不良患者中关键紧结蛋白的十二指肠粘膜表达水平.
- 解决先前研究中关于TJ蛋白质变化和FD之间的关联的不一致性.
主要方法:
- 在PubMed,EMBASE和Scopus数据库中进行了系统的电子文献搜索.
- 研究包括根据罗马III或罗马IV标准诊断出FD的患者.
- 定量合成 (元分析) 专注于FD患者和对照人群之间的特定TJ蛋白质 (克劳丁,ZO-1/2/3,β-catenin,E-cadherin,occludin) 表达的平均差异.
主要成果:
- 分析包括5项研究,共666名参与者 (420名FD患者).
- 在FD患者和对照组之间的claudin-1,claudin-2,claudin-3,claudin-4,ZO-1,ZO-2,ZO-3,β-catenin,E-cadherin或occludin的表达中没有观察到统计学上显著的差异.
- 报告了每个蛋白质的特定平均差异和95%置信区间,表明没有实质性的变化.
结论:
- 在功能性消化不良患者和健康对照人群之间,评估的紧结蛋白的十二指肠粘膜表达没有显著差异.
- 这些发现表明,这些特定的TJ蛋白质的改变可能不是FD病理生理学的主要因素.
- 由于在定量综合中包含的研究数量有限,应谨慎解释结果.

相关概念视频
 01:28
Peptic Ulcer Disease III: Clinical Manifestations and Diagnostic Studies
109
Peptic ulcer disease (PUD) presents with diverse symptoms depending on the location and severity of the ulcer. Clinical manifestations of peptic ulcer include dull pain and a burning sensation in the mid-epigastric region.
Few clinical manifestations differentiate gastric ulcers from duodenal ulcers. Distinctions in the location, timing, and pain relief are crucial for healthcare providers in differentiating between gastric and duodenal ulcers during clinical assessments.
Few clinical manifestations differentiate gastric ulcers from duodenal ulcers. Distinctions in the location, timing, and pain relief are crucial for healthcare providers in differentiating between gastric and duodenal ulcers during clinical assessments.
109
 01:22
Pathophysiology of Peptic Ulcer Disease: Injurious Factors
563
Peptic ulcers are sores on the stomach's inner lining and the upper small intestine, which are the result of disruptions in the mucosal layer that houses parietal cells which produce gastric acid, and chief cells which secrete pepsinogen.
In the antrum region, G cells secrete the gastrin hormone that binds to gastrin-cholecystokinin-B (CCK2) receptors on parietal and enterochromaffin-like (ECL) cells in the fundic glands. Simultaneously, the vagus nerve releases acetylcholine, which binds...
In the antrum region, G cells secrete the gastrin hormone that binds to gastrin-cholecystokinin-B (CCK2) receptors on parietal and enterochromaffin-like (ECL) cells in the fundic glands. Simultaneously, the vagus nerve releases acetylcholine, which binds...
563
 01:29
Tight Junctions
5.2K
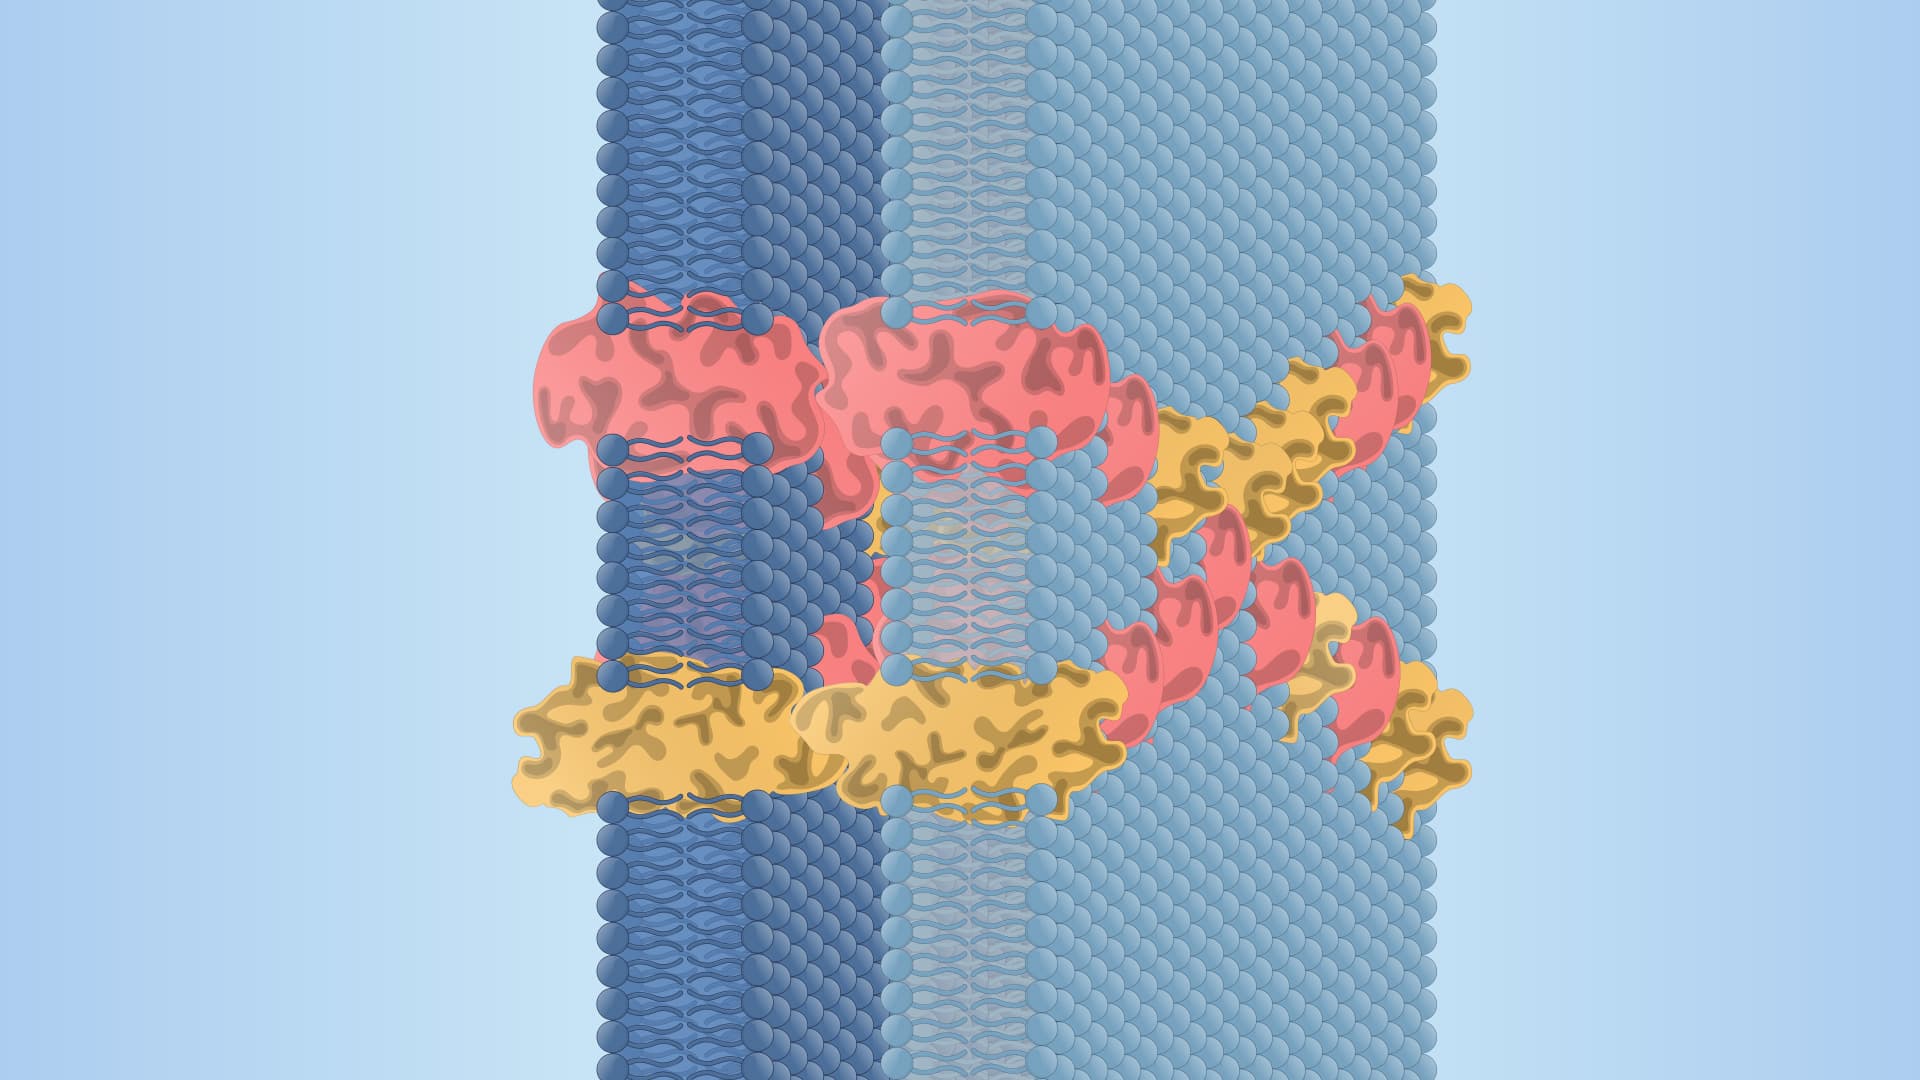
Tight junctions are molecular seals between cells that prevent the leaking of fluids, ions, and other small solutes across cavities and compartments in multicellular organisms. They are mainly composed of claudin and occludin transmembrane proteins, and other proteins such as tricellulin and JAM (junctional adhesion molecule). All these proteins are 4-pass transmembrane proteins, except JAM, which is a single-pass transmembrane protein belonging to the immunoglobulin superfamily. The...
5.2K
 01:28
Peptic Ulcer Disease II: Pathophysiology
365
Peptic Ulcer Disease (PUD) is characterized by the development of ulcers in the stomach or duodenal mucosa. Its pathophysiology is complex, involving a balance between damaging and protective elements.
Damaging agents such as Helicobacter pylori, gastric acid, pepsin, and nonsteroidal anti-inflammatory drugs (NSAIDs) can weaken the mucosal defense, allowing hydrogen ions to infiltrate back and harm epithelial cells.
Damaging agents such as Helicobacter pylori, gastric acid, pepsin, and nonsteroidal anti-inflammatory drugs (NSAIDs) can weaken the mucosal defense, allowing hydrogen ions to infiltrate back and harm epithelial cells.
365
 01:24
Pathophysiology of Peptic Ulcer Disease: Mucosal Defense Factors
365
Peptic ulcer disease, commonly called PUD, represents a multifaceted condition characterized by disruptions in the lining of the gastrointestinal (GI) tract. Central to the protection of the gastrointestinal lining is the mucosal-bicarbonate barrier. This physiological defense mechanism is a formidable shield against the corrosive effects of gastric acid and pepsin secretion in the stomach. Its role is pivotal in maintaining the structural integrity of the stomach's inner lining.
365
 01:17
Gastritis-II: Pathophysiology
312
Gastritis is marked by disruption of the mucosal barrier that usually protects the stomach tissue from digestive juices and manifests in acute and chronic forms.
In acute gastritis, the gastric mucosa becomes swollen and red and undergoes superficial erosion. Superficial ulceration may lead to bleeding.
In chronic gastritis, persistent or repeated insults lead to chronic inflammatory changes and, eventually, thinning or atrophy of the gastric tissue.
Gastritis can stem from various causes, each...
In acute gastritis, the gastric mucosa becomes swollen and red and undergoes superficial erosion. Superficial ulceration may lead to bleeding.
In chronic gastritis, persistent or repeated insults lead to chronic inflammatory changes and, eventually, thinning or atrophy of the gastric tissue.
Gastritis can stem from various causes, each...
312