GLP1-RA在优化减肥后巴里亚特手术中的作用:系统性审查和元分析
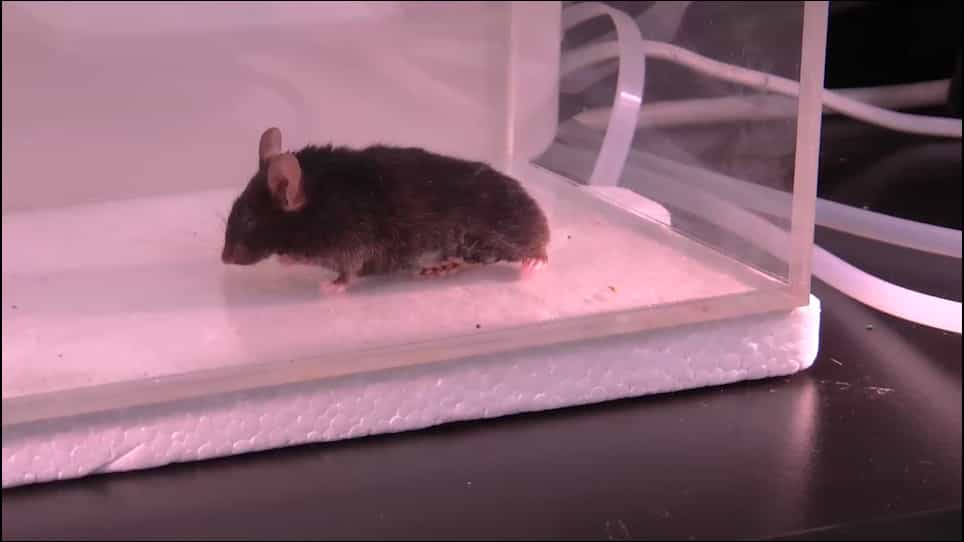
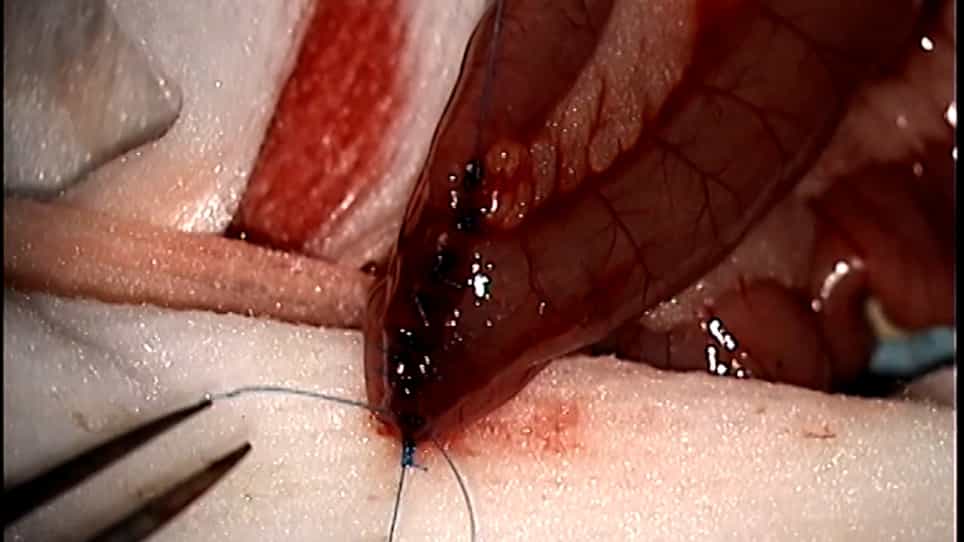
相关实验视频
Updated: Jun 14, 2025

07:37
Roux-en-Y Gastric Bypass Operation in Rats
Published on: June 11, 2012
23.5K
Mable Pereira1, Shenelle Menezes2, Ancy Jenil Franco3
1Lincoln American University School of Medicine, Kingston, Guyana. mablepereira27@gmail.com.
Obesity surgery
|August 31, 2024

概括
类似葡萄糖类-1受体激动剂 (GLP1-RAs) 在接受过腹部手术的患者中显著增强体重减轻. 这一元分析证实GLP1-RA疗法在六个月后改善了BMI和体重减轻.
科学领域:
- 代谢和腹部手术 代谢和腹部手术
- 药理学 药理学是指药理学的学科.
- 肥胖医学 肥胖医学
背景情况:
- 减肥手术在减肥方面是有效的,但有些患者经历了低于最佳的结果或体重恢复.
- 需要辅助疗法来改善长期的体重管理后腹部外科手术.
- 类似葡萄糖-1受体激动剂 (GLP1-RAs) 在增强减肥方面表现有前途.
研究的目的:
- 评估GLP1-RAs作为减肥减肥 bariatric 手术的辅助治疗的疗效.
- 为了比较减肥后接受GLP1-RAs与安慰剂的患者的减肥结果.
- 对此主题的随机对照试验 (RCT) 的数据进行系统分析.
主要方法:
- 三项随机对照试验 (RCT) 的元分析.
- 包括130名接受了减肥手术的患者.
- 分析体重减轻,BMI减轻,以及六个月后体重减轻的百分比.
主要成果:
- GLP1-RA治疗显著降低了6个月后的平均体重指数 (BMI).
- 与安慰剂相比,接受GLP1-RAs的患者体重减轻的百分比显著减少.
- 利拉格卢提德 (1.8-3毫克) 是一个显著的GLP1-RA在改善减肥结果.
结论:
- 在减肥手术后,GLP1-RAs有效改善减肥结果.
- 进一步的研究应该调查新的GLP1-RAs,每周给药.
- 需要更长的随访期来评估GLP1-RAs实现的减肥的持久性.
相关概念视频
 01:24
Glucagon-like Receptor Agonists
306
Incretins include glucagon-like peptide-1 (GLP-1) and glucose-dependent insulinotropic polypeptide (GIP), which stimulate insulin secretion post-meals. In type 2 diabetes, GIP's efficacy is reduced, making GLP-1 a viable drug target. GIP originates from preproGIP.
GLP-1, when administered in high doses intravenously, triggers insulin secretion, inhibits glucagon release, slows gastric emptying, reduces food intake, and restores normal insulin secretion. However, its rapid inactivation by...
GLP-1, when administered in high doses intravenously, triggers insulin secretion, inhibits glucagon release, slows gastric emptying, reduces food intake, and restores normal insulin secretion. However, its rapid inactivation by...
306
 01:23
Dipeptidyl Peptidase 4 Inhibitors
178
Dipeptidyl peptidase 4 (DPP-4) is a serine protease widely distributed in the body. It's involved in the inactivation of GLP-1 and GIP hormones, which are crucial for insulin regulation. DPP-4 inhibitors, such as sitagliptin (Januvia), saxagliptin (Onglyza), linagliptin (Tradjenta), alogliptin (Nesina), and vildagliptin (Galvus), help increase the proportion of active GLP-1, enhancing insulin secretion. These inhibitors work by competitively binding to DPP-4. This binding causes a...
178
 01:06
Oral Hypoglycemic Agents: Glinides
148
Repaglinide (Prandin) and Nateglinide (Starlix), known as glinides, are oral insulin secretagogues that stimulate insulin release from pancreatic β cells by closing the ATP-sensitive potassium channels (KATP channel). Repaglinide controls insulin release from pancreatic β cells by managing potassium efflux. It shares two binding sites with sulfonylureas and also has a unique site, indicating overlapping mechanisms of action. With a rapid onset and a 4-7 hour duration, it effectively...
148
 01:26
Oral Hypoglycemic Agents: Biguanides and Glitazones
183
Biguanides, particularly metformin (Glucophage), are insulin sensitizers that enhance glucose uptake, thereby reducing insulin resistance. Unlike sulfonylureas, metformin doesn't prompt insulin secretion, which helps to curb hypoglycemia risk. Metformin is beneficial in treating conditions like polycystic ovary syndrome due to its insulin-resistance reduction capability. The drug's primary action involves curtailing hepatic gluconeogenesis, a significant contributor to high blood...
183
 01:16
Hormones Regulating Blood Glucose
3.2K
Insulin is released by beta cells of the pancreas when blood glucose levels are high. It facilitates glucose absorption and utilization in insulin-dependent cells with insulin receptors on their plasma membranes. Insulin promotes glucose uptake by increasing the number of glucose transport proteins in the cell membrane, allowing glucose to enter the cell. As a result, glucose utilization and ATP production are enhanced.
In addition to accelerating glucose uptake and utilization, insulin has...
In addition to accelerating glucose uptake and utilization, insulin has...
3.2K
 01:16
Insulin: Dosing Regimen and Adverse Effects
160
Insulin-replacement therapy usually includes both long-acting insulin (basal) and short-acting insulin (to cater to postprandial needs). In a diverse group of type 1 diabetes patients, the average daily insulin dose is typically 0.5-0.7 units/kg body weight. However, obese patients and pubertal adolescents may need more due to insulin resistance.
The basal dose constitutes about 40%-50% of the total daily dose, with the rest as premeal insulin. The mealtime insulin dose should mirror...
The basal dose constitutes about 40%-50% of the total daily dose, with the rest as premeal insulin. The mealtime insulin dose should mirror...
160