
在患有乳头甲状腺癌的绝经后妇女中心周脂肪体积的变化,这些妇女正在接受甲状腺激素抑制疗法
Yunkyung Jeon1,2,3, Doohwa Kim1, Mijin Kim1,2,3
1Division of Endocrinology, Department of Internal Medicine, Pusan National University Hospital, Busan, Republic of Korea.
BMC endocrine disorders
|January 8, 2025

概括
对差异化甲状腺癌的TSH抑制疗法在绝经后妇女中增加了心表脂肪. 骨肌肉和腹部脂肪体积在两年内保持稳定.
科学领域:
- 内分泌学 在内分泌学.
- 在瘤学瘤学.
- 放射学 放射学是一门学科.
背景情况:
- 甲状腺刺激激素 (TSH) 抑制疗法对于差异化甲状腺癌 (DTC) 预后至关重要.
- 对长期的TSH抑制副作用存在担忧.
- 在TSH抑制下身体组成的变化需要调查.
研究的目的:
- 评估经历了TSH抑制的DTC的绝经后妇女的身体组成变化.
- 在2年的随访期内评估脂肪和肌肉体积的变化.
主要方法:
- 对心上,腹部内脏和皮下脂肪的体积测量评估.
- 使用计算机断层扫描 (CT) 测量psoas或大腿肌肉体积.
- 在2年内利用了基线和后续18F-FDG PET/CT扫描.
主要成果:
- 没有观察到体重或BMI的显著变化.
- 胸前脂肪体积显著增加,而其他脂肪储存和肌肉体积保持稳定.
- 心上脂肪增加与内脏脂肪和TSH抑制水平相关.
结论:
- 在经绝经后的女性中,TSH抑制疗法导致心表脂肪增加,DTC持续时间为<2年.
- 骨肌肉和腹部脂肪量没有受到影响.
- 需要进一步的研究来平衡TSH抑制在这个人群中的益处和风险.
相关概念视频
 01:17
Pericarditis III: Medical Management
586
The primary objectives of managing pericarditis are to determine the underlying cause, provide effective therapy for treatment and symptom relief, and promptly detect signs and symptoms of cardiac tamponade. The following outlines the essential aspects of medical management for pericarditis:ObjectivesDetermine the Cause: Identifying the underlying cause of pericarditis is crucial for targeted treatment. Causes include viral infections, autoimmune diseases, post-cardiac injury syndrome, and...
586
 01:25
Pericarditis IV: Nursing Management
640
Pericarditis, an inflammation of the pericardium, necessitates diligent nursing management to ensure effective patient care and recovery. The initial step in managing pericarditis is a comprehensive patient medical assessment.The patient reports chest pain aggravated by breathing, coughing, and swallowing, which worsens when lying supine. The pain often improves when sitting up and leaning forward. Additional symptoms may include fever, malaise, and, in severe cases, signs of heart failure.
640
 01:29
Cardiomyopathy III: Hypertrophic Cardiomyopathy
805
Hypertrophic cardiomyopathy, or HCM, is an autosomal dominant genetic disorder characterized by asymmetric left ventricular hypertrophy without ventricular dilation. It is more common in men and is typically diagnosed in young, athletic adults.EtiologyHCM is primarily genetic and is caused by mutations in genes encoding sarcomeric proteins. Researchers have identified over 1400 mutations across at least 11 different genes. Among these, the most frequently occurring mutations are found in the...
805
 01:25
Hyperthyroidism I: Introduction
30
Hyperthyroidism is a type of thyrotoxicosis characterized by the thyroid gland's overproduction of the thyroid hormones triiodothyronine (T3) and thyroxine (T4). This hormone excess increases the basal metabolic rate and enhances sensitivity to catecholamines.DiagnosisDiagnosis is based on clinical features and biochemical testing. It typically shows suppressed thyroid-stimulating hormone (TSH) levels below 0.4 mIU/L, with elevated free T3 and/or T4. Additional tests, including thyroid...
30
 01:27
Hyperthyroidism II: Pathophysiology
28
Hyperthyroidism is a hypermetabolic state caused by elevated levels of thyroid hormones, triiodothyronine (T3) and thyroxine (T4). It results from dysregulation at the thyroid, pituitary, or immune system level and affects multiple organ systems.PathophysiologyThe most common cause of hyperthyroidism is Graves’ disease, an autoimmune disorder in which antibodies, specifically thyroid-stimulating antibodies (TSAb), a subtype of TSH receptor antibodies (TRAb), bind to and activate TSH...
28
 01:23
Hypothyroidism II: Pathophysiology
26
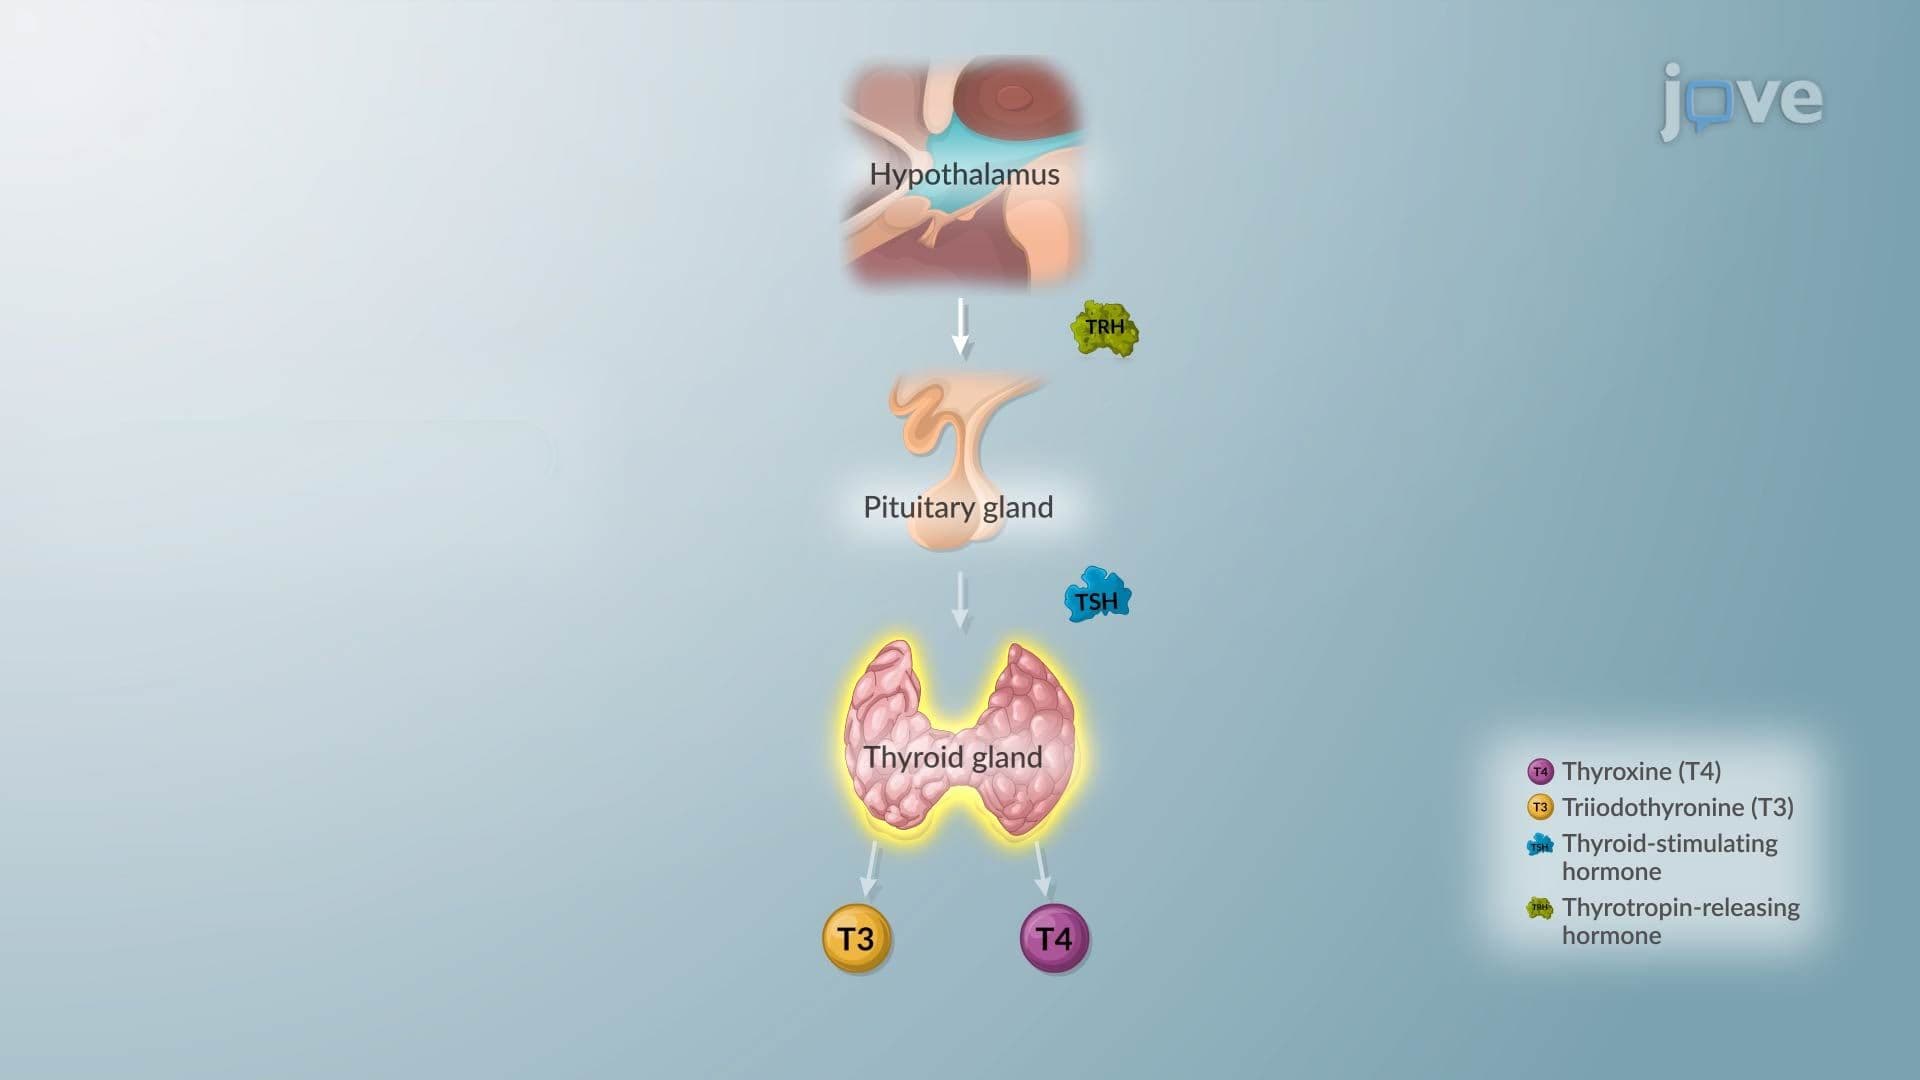
Hypothyroidism is a disorder characterized by insufficient production of thyroid hormones, which regulate metabolism, energy balance, and multiple organ systems.TypesHypothyroidism is classified based on the level of dysfunction. Primary hypothyroidism results from intrinsic thyroid gland dysfunction, causing reduced hormone production despite normal or increased stimulation. Secondary hypothyroidism arises from inadequate thyroid-stimulating hormone (TSH) secretion by the pituitary. Tertiary...
26