

呼吸不良和心力衰竭:隔膜的作用
Pablo Marino Corrêa Nascimento1,2, Mario Luiz Ribeiro1, Bernardo Nascimento Lourenço1
1Postgraduate Program in Cardiovascular Sciences, Fluminense Federal University, Niterói, Rio de Janeiro, Brazil.
Current cardiology reviews
|January 23, 2025

概括
隔膜功能障碍导致心力衰竭 (HF) 患者的呼吸障碍和运动不耐受. 对隔膜功能的超声波评估对于确定这种关联特别有用.
科学领域:
- 心脏病学 心脏病学
- 肺部病理学 肺部病理学
- 运动生理学 运动生理学
背景情况:
- 呼吸不全和运动耐受性降低是心力衰竭 (HF) 的标志性症状.
- 鼓舞性肌肉疲弱,特别是腹膜,是HF患者这些症状的潜在因素.
研究的目的:
- 审查有关膜功能在心力衰竭患者呼吸障碍和运动不耐受症发展中的作用的现有文献.
主要方法:
- 2003年1月至2023年3月期间发表的原始文章,临床试验和队列/病例控制研究的系统审查.
- 在PubMed/MEDLINE,Embase和BVS/LILACS数据库中搜索了评估HF患者,隔膜功能和呼吸障碍或运动耐受性的研究.
主要成果:
- 在最初识别的353篇文章中,有9篇研究被纳入了定性综合.
- 大多数包括的研究表明,腹膜功能障碍,呼吸障碍和HF患者的运动不耐受性之间存在显著的关联.
结论:
- 尽管方法异质,但大多数研究表明,膜功能受损有助于呼吸障碍和心力衰竭的运动不耐受.
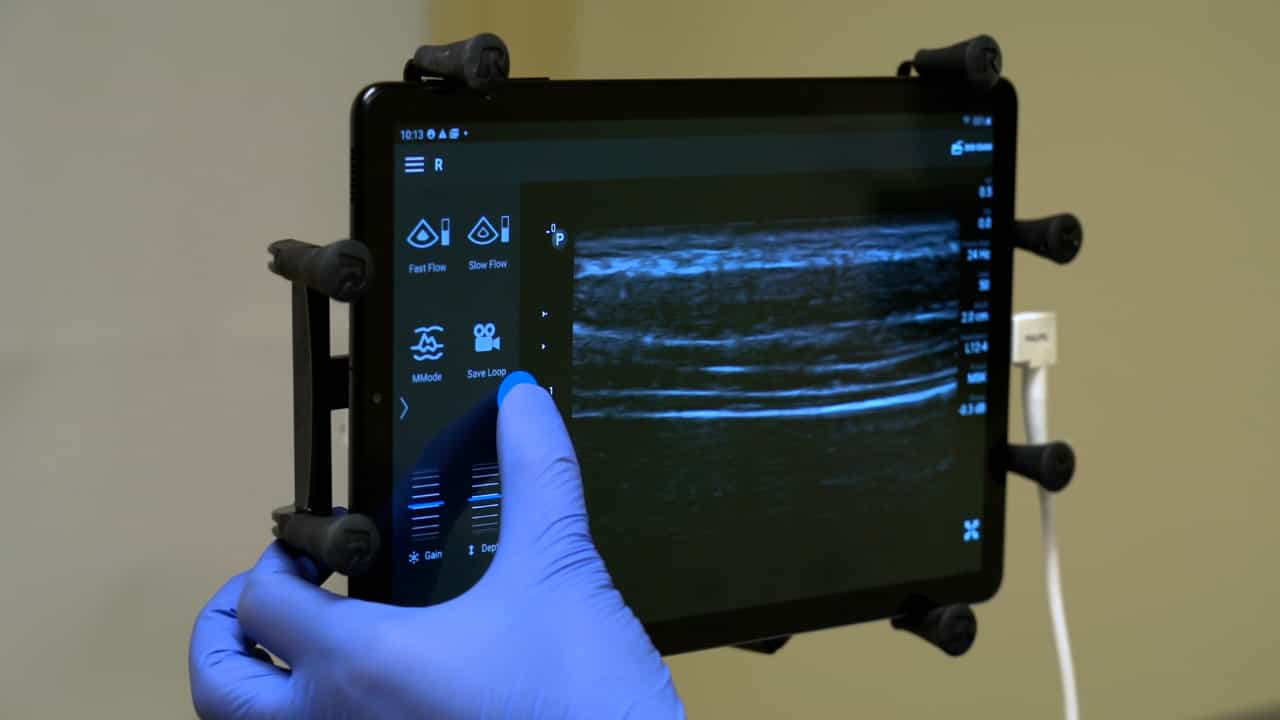
- 对隔膜功能的超声波评估在揭示这种关联方面似乎特别有效.

相关概念视频
 01:05
Breathing
The process of breathing, inhaling and exhaling, involves the coordinated movement of the chest wall, the lungs, and the muscles that move them. Two muscle groups with important roles in breathing are the diaphragm, located directly below the lungs, and the intercostal muscles, which lie between the ribs. When the diaphragm contracts, it moves downward, increasing the volume of the thoracic cavity and creating more room for the lungs to expand. When the intercostal muscles contract, the ribs...
 01:26
Imbalances in Cardiac Output
The heart's primary function is to pump blood throughout the body, maintaining a balance between blood sent out (cardiac output) and blood returning (venous return). If this balance is disrupted, it can result in congestive heart failure (CHF), a severe condition where the heart becomes an inefficient pump, leading to inadequate blood circulation.
CHF can occur due to the failure of either side of the heart. Left-side failure leads to pulmonary congestion—the right side continues to send blood...
CHF can occur due to the failure of either side of the heart. Left-side failure leads to pulmonary congestion—the right side continues to send blood...
 01:17
Pulmonary Cycle: Exhalation
In terms of human respiration, the act of expelling air, known as exhalation (or expiration), operates on the principle of pressure gradients. During expiration, the pressure within the lungs exceeds that of the surrounding atmosphere. Under normal conditions, quiet breathing involves passive exhalation and is free of muscular contractions. This is because the exhalation process is driven by the natural elastic recoil of the lungs and chest wall, both of which have an inherent tendency to...
 01:20
Chronic Obstructive Pulmonary Disease-II: Pathophysiology
Chronic Obstructive Pulmonary Disease (COPD) pathophysiology is intricate and multifaceted, involving a complex interplay of physiological processes. Understanding these mechanisms is crucial for effectively managing and treating COPD. Here is an in-depth look at the critical elements in the pathophysiology of COPD:
Chronic Inflammation
Chronic Inflammation
 01:10
Atelectasis II: Pathophysiology
Atelectasis develops when alveoli lose their air and collapse inward. Because lung tissue is naturally elastic, these air sacs shrink rather than remaining open. Collapsed alveoli are no longer ventilated, reducing their role in gas exchange. Blood flow may continue in these regions, creating a ventilation–perfusion mismatch. Clinical findings include decreased breath sounds, dullness to percussion, reduced chest expansion, and decreased tactile fremitus as sound transmission through collapsed...
 01:23
Chronic Obstructive Pulmonary Disease II: Emphysema
Emphysema, a major phenotype of chronic obstructive pulmonary disease (COPD), is characterized by irreversible destruction of alveolar walls and permanent enlargement of distal airspaces. Unlike chronic bronchitis, which primarily affects the airways, emphysema predominantly involves the lung parenchyma, where structural damage leads to airflow limitation.PathophysiologyIt most commonly results from prolonged exposure to cigarette smoke and other toxic gases, particularly cigarette smoke.