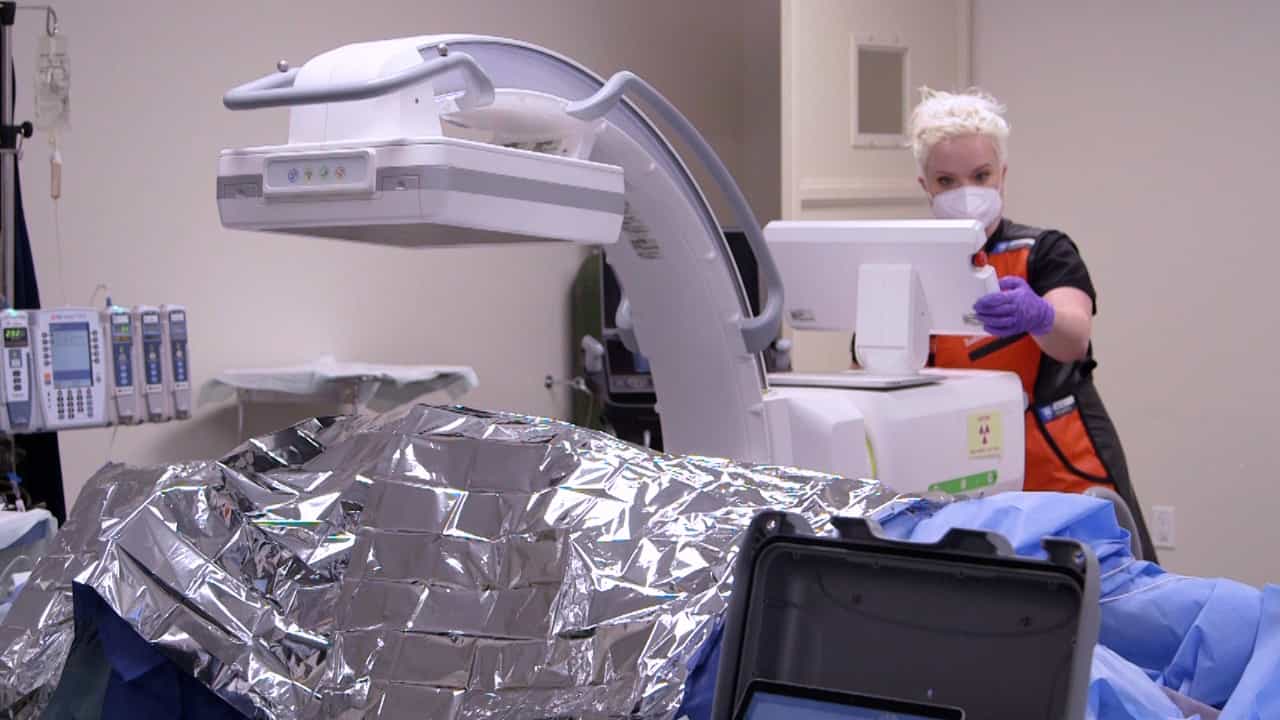
评估躺姿对急性损伤的影响
Eden Ezra1, Itai Hazan1,2, Dana Braiman1,3
1Joyce and Irving Goldman Medical School, The Faculty of Health Sciences, Ben-Gurion University of the Negev, Beer-Sheva 8410501, Israel.
Journal of clinical medicine
|January 25, 2025

概括
俯卧可能会增加急性损伤 (AKI) 的风险,在超重/肥胖的患者中,患有严重急性呼吸困扰综合征 (ARDS). 这一发现突显了特定患者群体的潜在风险,以及需要量身定制的管理策略.
科学领域:
- 关键护理医学 关键护理医学
- 腎臟病學 (nephrology) 是一種醫學專業.
- 肺部病理学 肺部病理学
背景情况:
- 倾斜的定位是管理严重急性呼吸困扰综合征 (ARDS) 的基石,主要是为了改善氧化.
- 倾斜定位对功能的影响,特别是在超重或肥胖患者中,仍然不太了解.
- 急性损伤 (AKI) 是重症患者常见的并发症,其与容易定位的关联值得调查.
研究的目的:
- 调查易受影响的定位和AKI在重症ARDS患者的发展之间的关联.
- 具体评估是否超重和肥胖的ARDS患者在躺卧姿势时会增加AKI的风险.
- 为了比较超重/肥胖患者的AKI发展与非肥胖的ARDS患者进行易感定位.
主要方法:
- 一个回顾性前后研究设计,涉及60名重症ARDS患者.
- 患者使用急性损伤网络 (AKIN) 标准对AKI进行了评估,评估了肌素水平 (AKIN_Cr) 和尿液输出 (AKIN_UO).
- 患者被分为超重/肥胖 (BMI ≥25) 和非肥胖 (BMI <25) 两组,在倾斜定位前后收集数据.
主要成果:
- 超重/肥胖患者 (n=39) 在躺卧后,AKIN_Cr (0至1,p < 0.01) 和AKIN_UO (0至2,p < 0.01) 中位数显著增加.
- 在非肥胖患者中,没有观察到AKIN得分的显著变化.
- 在任何一组中,将身体重新定位到仰卧位置并没有导致AKIN分数的显著差异.
结论:
- 倾斜的位置与超重和肥胖的ARDS患者中AKI的风险增加有关.
- 这种增加的风险可能与这些患者群体中脏对腹内高血压的敏感性有关.
- 建议进行进一步的研究,以开发超重和肥胖ARDS患者的最佳易感定位策略.


相关概念视频
 01:45
Kidney Structure
68.7K
The kidneys are two large bean-shaped organs located in the upper abdomen. They filter the blood several times a day to remove toxins and rebalance water and electrolytes of the circulatory system via the renal veins. The kidneys receive blood directly from the heart via the renal arteries. These arteries enter the kidney at the hilum, the concave surface of the bean, where they branch and divide into smaller vessels and capillaries.
68.7K
 01:10
Nephrons
2.1K
The kidneys are intricate organs with millions of working units known as nephrons. Each nephron features two major structures: the renal corpuscle, which facilitates blood plasma filtration, and the renal tubule, which handles the glomerular filtrate. Blood supply is directly linked to the nephrons. The renal corpuscle consists of the glomerulus, a capillary network, and the Bowman's capsule, a double-walled epithelial structure that encases the glomerulus. The filtering of blood plasma...
2.1K
 01:27
Dialysis
255
Renal failure occurs when the kidneys lose their ability to filter waste products from the blood effectively. It can be classified into two types: acute renal failure (ARF) and chronic renal failure (CRF).
Acute kidney injury develops suddenly and can be caused by pre-renal causes (e.g., hypovolemia, shock), intrinsic renal causes (e.g., acute tubular necrosis), or post-renal causes (e.g., urinary obstruction). In contrast, chronic renal failure progresses gradually over time and is often...
Acute kidney injury develops suddenly and can be caused by pre-renal causes (e.g., hypovolemia, shock), intrinsic renal causes (e.g., acute tubular necrosis), or post-renal causes (e.g., urinary obstruction). In contrast, chronic renal failure progresses gradually over time and is often...
255
 01:11
Renal Failure: Dose Adjustments
61
In patients with renal impairment, drugs undergo significant changes in their pharmacokinetics, which require dosage adjustments to ensure safe and effective therapy.
Reduced renal clearance and elimination rate are common outcomes of renal impairment. These alterations lead to a prolonged elimination half-life and an altered apparent volume of distribution for drugs. As a result, dosage adjustments are typically necessary to maintain optimal drug levels in the body.
However, dosage adjustments...
61
 01:25
Antihypertensive Drugs: Direct Renin Inhibitors
480
The renin-angiotensin-aldosterone system (RAAS) is an intricate physiological pathway involving numerous enzymes and hormones, including renin, angiotensin-converting enzyme (ACE), angiotensin I and II, and aldosterone. Imbalances within this system increase the production of angiotensin II and aldosterone. Increased angiotensin II levels promote vasoconstriction and blood pressure elevation. Concurrently, higher aldosterone levels stimulate sodium and water reabsorption in the kidneys,...
480
 01:22
Renal Drug Excretion: Effect of Urine pH, Flow Rate, and Drug pKa
132
The pH of urine, the drug's pKa, and the urine flow rate are vital parameters for drug reabsorption and excretion. Urinary pH varies between 4.6 and 8.0 and is influenced by diet, drug intake, and the patient's pathophysiology. It affects a drug's ionization state and reabsorption. For instance, carbohydrate-rich food produces alkaline urine promoting drug excretion, while proteins and certain medications like ascorbic acid lead to acidic urine enhancing reabsorption.
The pKa of a...
The pKa of a...
132