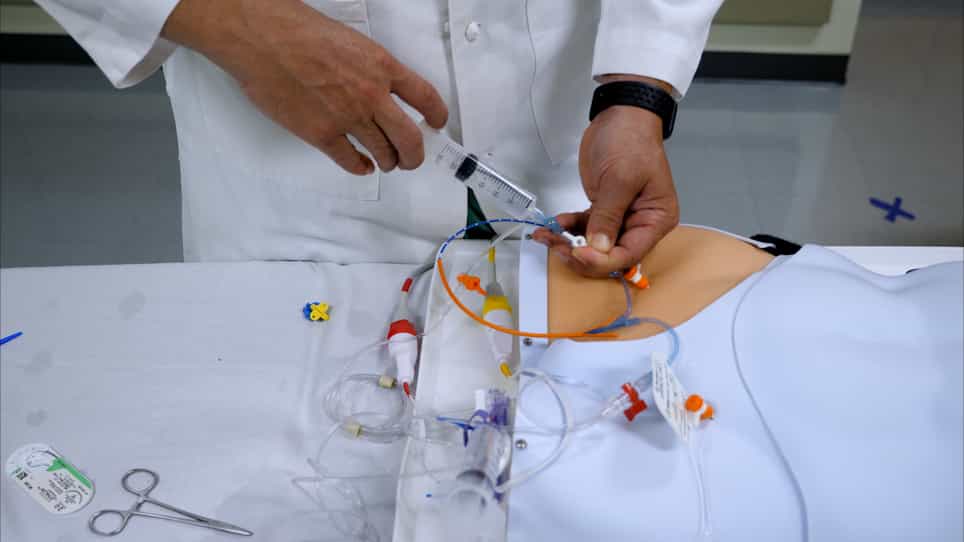
与完整的REBOA区域1和急诊室胸切除术相比,部分REBOA区域1与较低的死亡率有关:使用AORTA注册表的队列研究
Morgan G Dewey1, Ernest E Moore1,2, Lee Anne Ammons2
1School of Medicine, University of Colorado, Aurora, Colorado, USA.
Transfusion
|March 10, 2025

概括
大动脉的部分复苏内血管气球封闭 (P-REBOA) 显示出改善的结果. 这种大动脉封闭方法提供了更好的血液动力学稳定性和降低死亡率相比完整的REBOA (C-REBOA) 和急诊室胸切除术 (EDT) 在创伤患者没有穿透的胸部损伤.
科学领域:
- 创伤外科手术是什么
- 紧急医疗 紧急医疗
- 这是血管外科手术.
背景情况:
- 复苏性内血管气球阻塞大动脉 (REBOA) 和急诊室胸切除术 (EDT) 在危及生命的出血中对大动脉阻塞 (AO) 至关重要.
- 完全的AO可以导致内脏缺血,促使部分REBOA (P-REBOA) 的发展,以平衡出血控制和 perfusion.
- 在创伤中复苏的大动脉阻塞 (AORTA) 注册表提供了用于比较AO技术的数据.
研究的目的:
- 测试P-REBOA导致比EDT和C-REBOA更好的患者结果的假设.
- 在创伤患者中比较不同大动脉封闭方法的有效性.
- 评估AO技术对死亡率和患者康复的影响.
主要方法:
- 对2017-2023年AORTA注册表数据的分析.
- 在急诊室内包括接受EDT,C-REBOA或P-REBOA的成年患者,但不包括穿透胸部创伤的患者.
- 使用调整的生存率分析和通用线性模型,比较死亡率,无呼吸器日 (VFD) 和无ICU日 (ICUFD).
主要成果:
- 在921名患者中,66.6%接受EDT,24.3%C-REBOA和9.1%P-REBOA,整体死亡率为83.1%.
- 调整后的分析显示,C-REBOA和EDT与P-REBOA相比,与更低的血液动力学改善/稳定性和更高的死亡率有关.
- 与C-REBOA和P-REBOA患者相比,EDT患者的VFD和ICUFD较少;然而,EDT与幸存者的并发症有关.
结论:
- 与C-REBOA和EDT相比,P-REBOA显示出优越的血液动力稳定性和降低的死亡率.
- 对于没有穿透胸部损伤的创伤患者,P-REBOA可能是首选的大动脉封闭策略.
- 对优化P-REBOA应用的进一步研究是有必要的.
更多相关视频
 08:50
Technique and Patient Selection Criteria of Right Anterior Mini-Thoracotomy for Minimal Access Aortic Valve Replacement
Published on: March 26, 2018
11.6K
 05:39
Author Spotlight: A Non-Intubated Video-Assisted Thoracoscopic Surgery with Multimodal Analgesia and Sevoflurane Inhalation Anesthesia
Published on: May 26, 2023
1.4K
相关概念视频
 01:26
Flail Chest-II
151
Managing flail chest, a condition characterized by a segment of the chest wall moving independently from the rest of the thoracic cage, requires a comprehensive approach. It includes a thorough assessment of the patient's condition, a diagnostic evaluation to determine the extent of the injury, and the implementation of appropriate medical interventions tailored to the individual's needs.
Assessment:
1. Clinical Evaluation:
History:
Assessment:
1. Clinical Evaluation:
History:
151
 01:21
Acute Respiratory Failure-II
158
Type I Respiratory Failure, or hypoxemic respiratory failure, occurs when the partial pressure of oxygen (PaO2) in arterial blood falls below 60 mmHg while breathing room air without a corresponding increase in arterial carbon dioxide levels (PaCO2). This condition highlights a significant impairment in the lungs' capacity to oxygenate the blood.
The underlying physiological abnormalities that contribute to hypoxemic respiratory failure include:
The underlying physiological abnormalities that contribute to hypoxemic respiratory failure include:
158
 01:29
Acute Respiratory Failure-V
113
The treatment for acute respiratory failure varies based on factors like the underlying cause, overall health, and severity. A collaborative healthcare team is essential for early detection, often through arterial blood gas analysis. Identifying the cause is the primary goal, with treatment strategies adjusted for ventilation/perfusion (V/Q) mismatch, shunting, or diffusion impairment.
Ensure that patients are monitored continuously for their response to therapy, including changes in...
Ensure that patients are monitored continuously for their response to therapy, including changes in...
113
 01:30
Acute Respiratory Failure-III
150
Hypercapnic respiratory failure, also known as Type 2 or ventilatory respiratory failure, is a severe condition characterized by the body's inability to effectively remove carbon dioxide (CO2) from the bloodstream. It leads to an arterial CO2 pressure (PaCO2) exceeding 45 mmHg and a blood pH above 7.35. This situation indicates that the body's ventilatory demand, or the ventilation needed to maintain normal PaCO2 levels, surpasses its supply or the maximum gas flow achievable without...
150