在严重肝病的血吸附过程中,加工血量与总胆红素减少之间的关联
Yuanji Ma1, Yan Xu1, Lingyao Du2
1Center of Infectious Diseases, West China Hospital of Sichuan University, No.37 GuoXue Xiang, Wuhou District, Chengdu, 610041, China.
European journal of medical research
|March 16, 2025

概括
在双等离子分子吸附系统 (DPMAS) 治疗中,加工等离子体 (VPP) 的体积在严重的肝病中可以超过4500毫升. 对于身高增加或白蛋白水平较低的患者,可能需要更高的VPP,以确保有效减少胆红素.
科学领域:
- 肝病学 肝病学是一种肝病学.
- 生物医学工程 生物医学工程
- 临床化学 临床化学
背景情况:
- 双等离子体分子吸附系统 (DPMAS) 对于严重肝病管理至关重要.
- 在使用的加工血量 (VPP) 中存在显著的变化,缺乏标准化的协议.
- 这项研究调查了DPMAS治疗期间VPP和总胆红素减少之间的相关性.
研究的目的:
- 确定VPP与在接受DPMAS治疗的严重肝病患者中总胆红素水平的变化之间的关系.
- 为了确定更高的VPP是否与总 bilirubin 的更大降低有关.
- 确定可能从调整的VPP协议中受益的患者子组.
主要方法:
- 在重症肝病患者中进行重复测量前性观察性研究.
- 用于分析VPP和总胆红素变化之间的关联的概括估计方程.
- 在四个不同的VPP测量了总胆红素水平:0mL,3000mL,3750mL和4500mL.
主要成果:
- 在29名患者的75次DPMAS疗程中,总胆红素水平逐渐显著降低,随着VPP的增加,胆红素水平逐渐显著降低.
- 在基线水平<425μmol/L和≥425μmol/L的患者中,总 bilirubin 的降低比率是可比的.
- 总胆红素减少和VPP之间的正相关性在更高的患者或具有较低白蛋白水平的患者中不那么明显.
结论:
- 对于DPMAS治疗的有效VPP可能超过4500毫升.
- 身高较高或血清白蛋白较低的患者可能需要更高的VPP以获得最佳的治疗结果.
- 基于患者特征的个性化VPP调整可以提高DPMAS在肝病管理中的有效性.

相关概念视频
 01:29
Drug Distribution: Plasma Protein Binding
12.6K
Drugs predominantly attach to plasma proteins, with only a small percentage remaining unbound. The unbound portion can be calculated as one minus the bound fraction. Acidic drugs form large, inactive complexes by reversibly binding to plasma albumin, which prevents them from diffusing across biological barriers. These drug-protein complexes act as reservoirs for the drugs. As the concentration of unbound drugs decreases, these complexes quickly dissociate to release the free drug, maintaining...
12.6K
 01:09
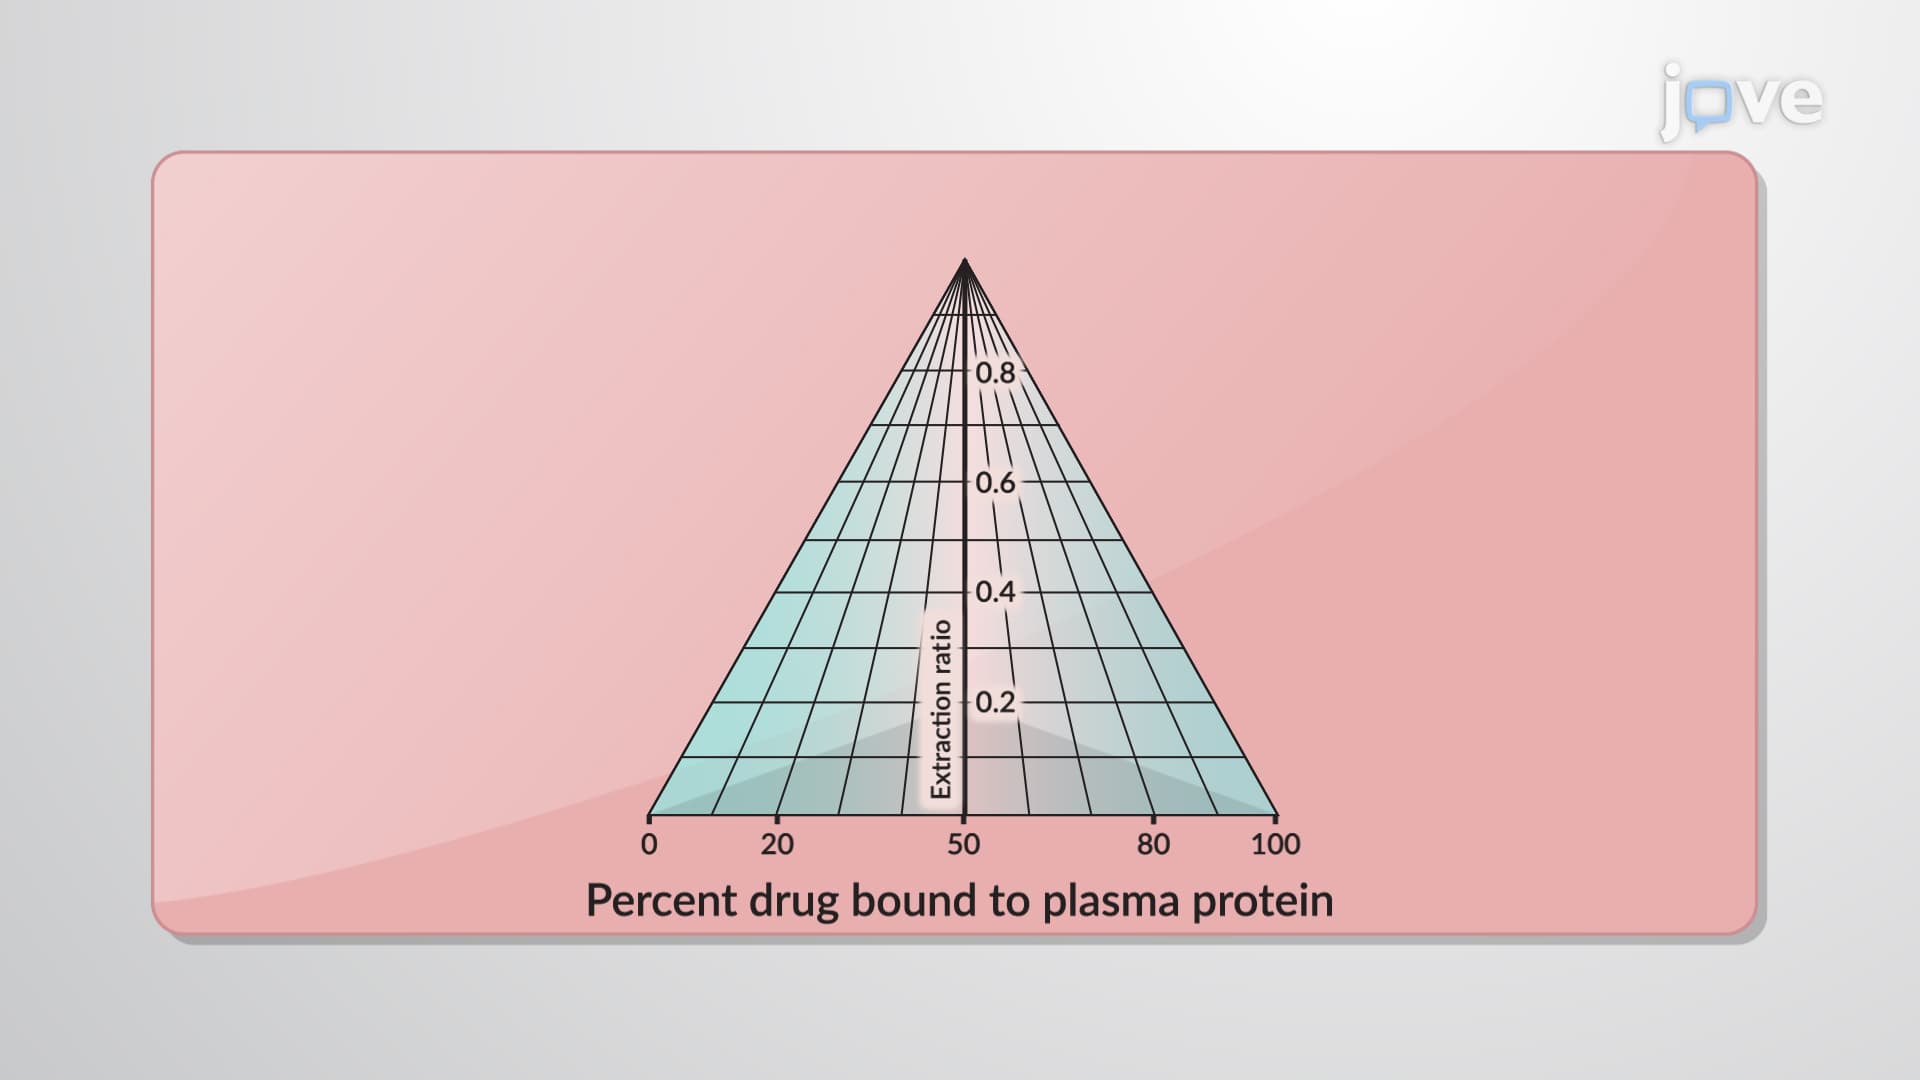
Hepatic Drug Clearance: Effect of Protein Binding
725
Hepatic clearance is influenced by protein binding based on the drug's extraction ratio. Drugs with high extraction ratios are considered flow-limited and remain unaffected by protein binding during hepatic clearance. On the other hand, drugs with low extraction ratios may be impacted by plasma protein binding, although the extent of this influence depends on the fraction of the drug bound.
For low-extraction-ratio drugs that are less than 80% protein-bound, minor changes in protein binding...
For low-extraction-ratio drugs that are less than 80% protein-bound, minor changes in protein binding...
725
 01:26
Effect of Hepatic Disease on Pharmacokinetics: Drug Dosing and Hepatic Blood Flow
382
Chronic liver disease significantly impacts drug metabolism due to alterations in hepatic blood flow and enzyme accessibility. This disruption affects the body's pharmacokinetics—the movement and processing of drugs within the system. Key enzymes crucial for metabolizing medications become less accessible, changing how drugs are processed and utilized. Furthermore, liver disease influences the synthesis of plasma proteins, such as albumin and globulins, which play critical roles in drug...
382
 01:14
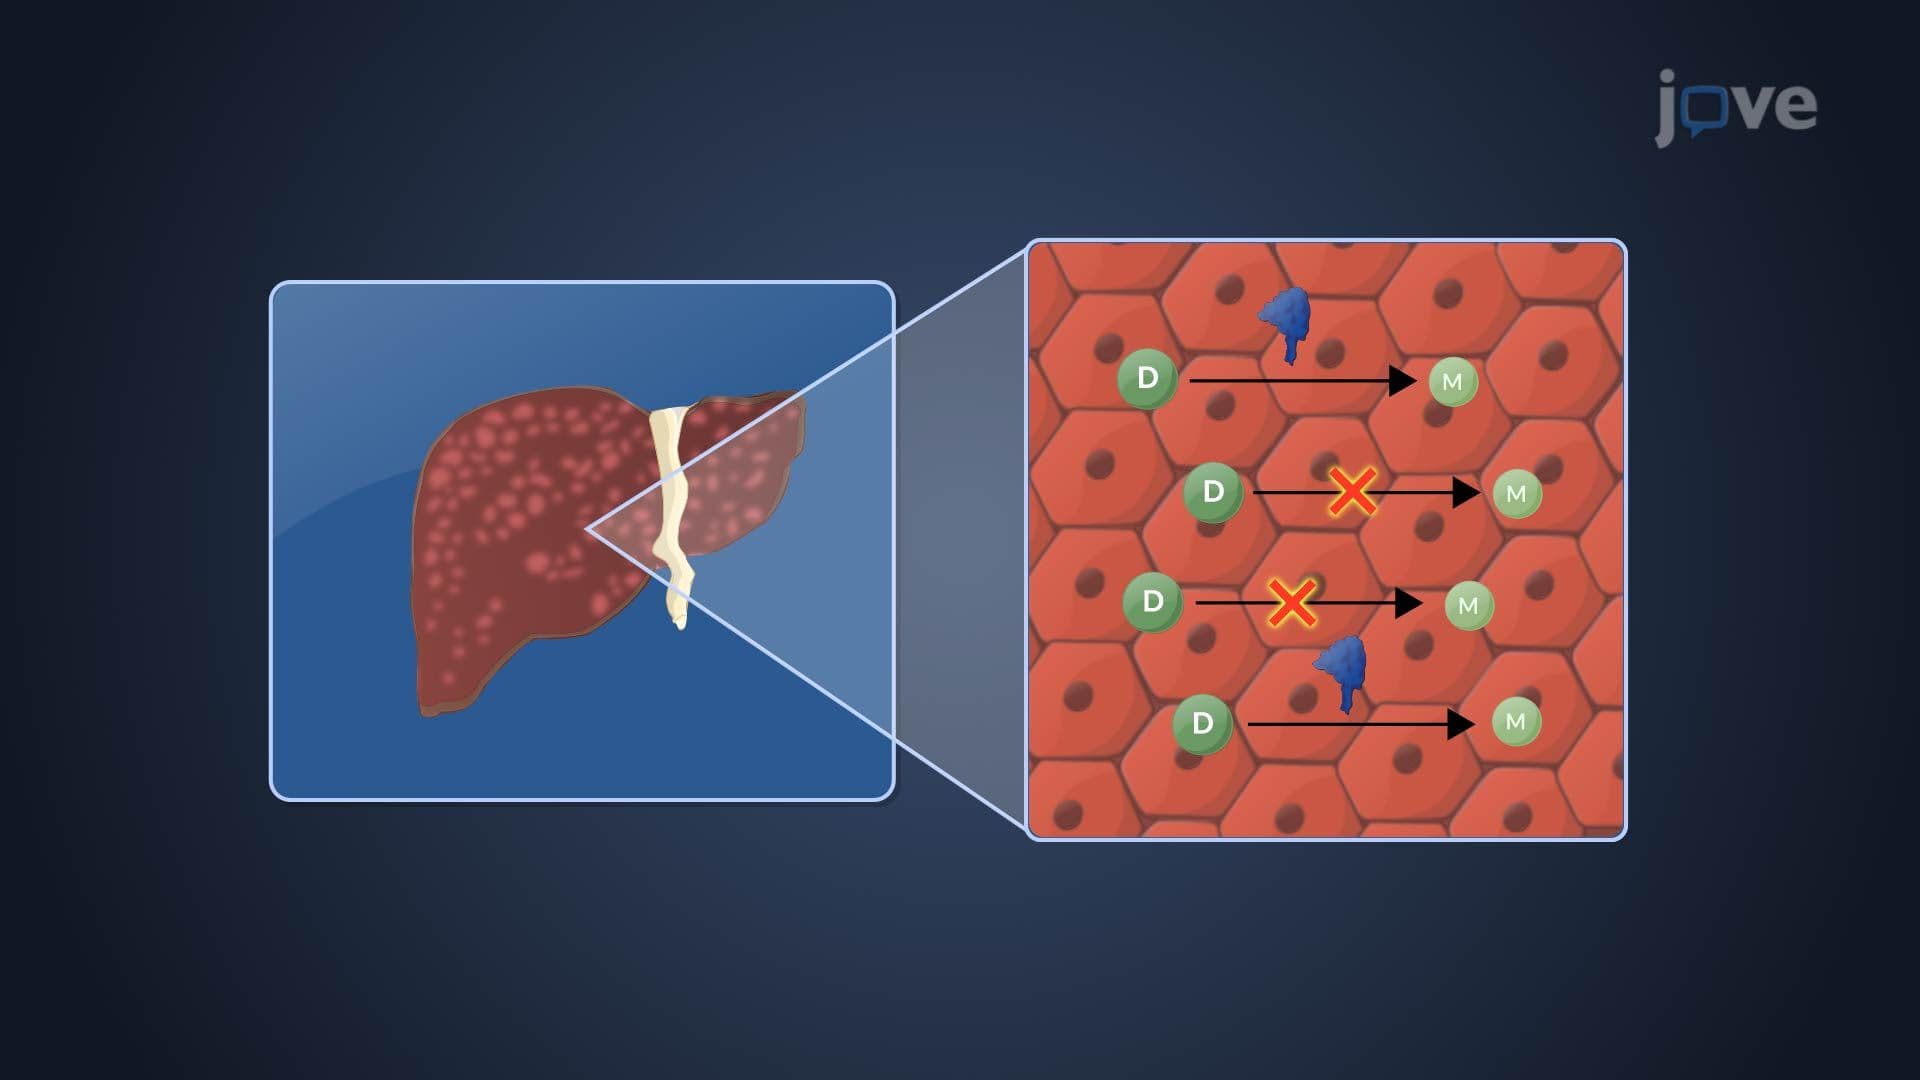
Effect of Hepatic Disease on Pharmacokinetics: Active Drug, Metabolite and Fraction of Metabolized Drug
358
In pharmacotherapy, monitoring drug concentrations is paramount, especially for drugs whose therapeutic effects hinge on both the active compound and its metabolite. Hepatic impairment profoundly influences drug potency by altering liver function. If the drug is more potent than its metabolite, impaired liver function amplifies drug activity due to elevated drug concentration levels. Conversely, if the metabolite holds greater potency, diminished liver function diminishes drug activity by...
358
 01:22
Effect of Hepatic Disease on Pharmacokinetics: Pathophysiologic Assessment and Liver Function Test
271
In clinical practice, the direct measurement of hepatic blood flow to evaluate liver function presents significant challenges due to the intricate and specialized nature of the necessary techniques. Consequently, healthcare professionals often rely on empirical estimates derived from thorough patient examinations and liver function tests to gauge liver health. Among the tools at their disposal, the Child–Pugh and MELD scoring systems stand out for their ability to categorize and assess...
271
 01:25
Jaundice
35
Jaundice, or icterus, is the yellow discoloration of the skin, sclerae, and mucous membranes. It happens when plasma bilirubin levels rise above 2.5-3 mg/dL, leading to bilirubin deposition in tissue.Bilirubin is a byproduct of hemoglobin degradation. In macrophages, hemoglobin breaks down into globin and heme. Globin is converted into amino acids, while heme is turned into biliverdin by heme oxygenase, which is then reduced to unconjugated bilirubin by biliverdin reductase.Unconjugated...
35