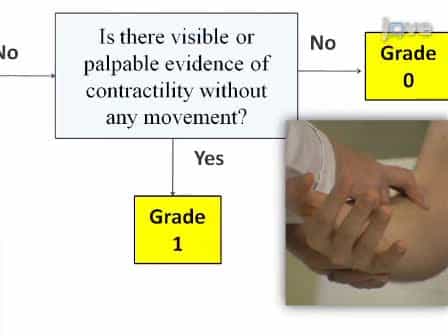

呼吸道和四肢肌肉在重症监护室获得的虚弱患者中反复产生最大同位体强度的能力:一项观察性研究
Margaux Machefert1,2, Guillaume Prieur3,4, Solène Aubry5
1Physiotherapy Department, Le Havre Hospital, Le Havre, F-76600, France. margaux.machefert@ch-havre.fr.

在重症监护室获得的软弱会对四肢和呼吸道肌肉产生不同的影响. 四肢力量在重复努力时下降,而灵感肌肉力量保持稳定,这表明ICU患者的明显恢复模式.
科学领域:
- 关键护理医学 关键护理医学
- 神经学 神经学
- 肺部病理学 肺部病理学
背景情况:
- 在重症监护室获得的虚弱 (ICU-AW) 是重症患者常见的并发症.
- ICU-AW影响四肢和呼吸道肌肉,影响患者的康复.
- 不同肌肉群参与ICU-AW的机制需要进一步研究.
研究的目的:
- 为了比较灵感肌和四头肌肌的力量演变的时间进程.
- 评估ICU-AW患者在重复的最大同位数收缩期间的力量变化.
- 评估不同肌肉群体的运动后恢复模式.
主要方法:
- 观察性,单中心研究,对被输出管的危急病患者进行观察,这些患者有肢体和灵感肌肉的软弱.
- 最大吸气压 (Pimax<30 cmH2O) 和MRC得分 (<48) 定义的弱点.
- 用电子压力计和动力计测量了10秒休息的重复最大自愿力度 (10次收缩).
主要成果:
- 在重复努力的过程中,四肢肌肉力量显著下降 (-15.45 N).
- 启发性肌肉强度保持稳定 (1.75 cmH2O的差异).
- 时间和肌肉群之间的显著相互作用 (p=0.0017) 表明了不同的强度演变;四头肌强度在恢复后得到改善 (p=0.009),而不是灵感肌肉 (p=0.16).
结论:
- 患有ICU获得的弱点的患者在四头肌和鼓动肌之间保持力量的能力有所不同.
- 四肢肌肉表现出疲劳和恢复,而呼吸肌肉表现出稳定性.
- 研究结果强调了在ICU-AW中针对不同肌肉群的有针对性的康复策略的潜力.
更多相关视频
 09:24
Repeated Measurement of Respiratory Muscle Activity and Ventilation in Mouse Models of Neuromuscular Disease
Published on: April 17, 2017
 09:37
Evaluation of Respiratory Muscle Activation Using Respiratory Motor Control Assessment RMCA in Individuals with Chronic Spinal Cord Injury
Published on: July 19, 2013
相关概念视频
 01:30
Assessment of Airway, Skin Color, and Use of Accessory Muscles
Introduction
The initial evaluation of a patient's respiratory system...
 01:27
Physical Assessment of the Respiratory Tract II: Inspection
Chest Configuration
The chest configuration...
 01:21
Mechanism of Breathing III: The Accessory Muscles
The respiratory system is a complex network that relies on primary respiratory muscles like the diaphragm, but also involves accessory muscles to enhance lung expansion and airflow during both inhalation and exhalation.
Enhancing Inhalation with Accessory Muscles:
Accessory muscles such as the sternocleidomastoid, scalene, intercostal, and abdominal muscles are crucial when additional respiratory effort is required, such as during deep...
 01:21
Acute Respiratory Failure-II
The underlying physiological abnormalities that contribute to hypoxemic respiratory failure include:
 01:23
Acute Respiratory Failure-IV
 01:30
Acute Respiratory Failure-III