相关实验视频
Updated: Jul 16, 2026
10:10

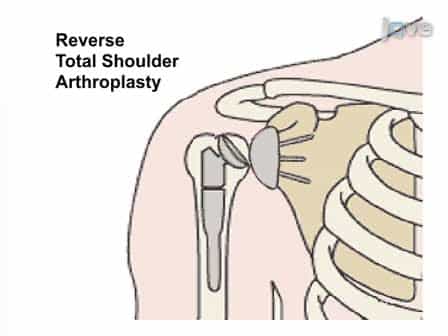
Reverse Total Shoulder Arthroplasty
Published on: July 5, 2011
43.0K
疼痛肩膀综合征作为临床问题 - - 对物理治疗的分析
Włodzisław Kuliński1, Krystian Szymczyk2
1DEPARTMENT OF REHABILITATION, MILITARY INSTITUTE OF MEDICINE, NATIONAL RESEARCH INSTITUTE, WARSAW, POLAND.

概括
物理治疗有效地减少疼痛和改善肩膀关节运动在轮手套受伤的患者. 这种治疗改善了疼痛肩膀综合征患者的整体生活质量和功能.
科学领域:
- 整形外科 整形外科 整形外科
- 物理医学和康复 康复
背景情况:
- 旋转手套损伤往往导致疼痛肩膀综合征,显著影响患者的功能.
- 有效的管理策略对于改善患者的治疗结果和生活质量至关重要.
研究的目的:
- 评估综合物理治疗方案对被诊断患有旋转手套损伤后的疼痛肩部综合征的患者的疗效.
主要方法:
- 一组25名患者 (15名女性,10名男性) 接受了为期3周的康复计划.
- 物理治疗方案包括二动力电流,超声波,冷疗法,冲击波疗法和运动疗法.
主要成果:
- 所有患者在治疗后经历了显著的疼痛减轻或完全消除.
- 观察到肩关节所有平面的运动范围显著增加.
结论:
- 实施的物理治疗方案成功地缓解了与旋转手腕损伤相关的疼痛.
- 改善了关节的移动性,功能能力和整体生活质量.
- 物理治疗是管理旋转手套损伤的疼痛肩部综合征的基石治疗.
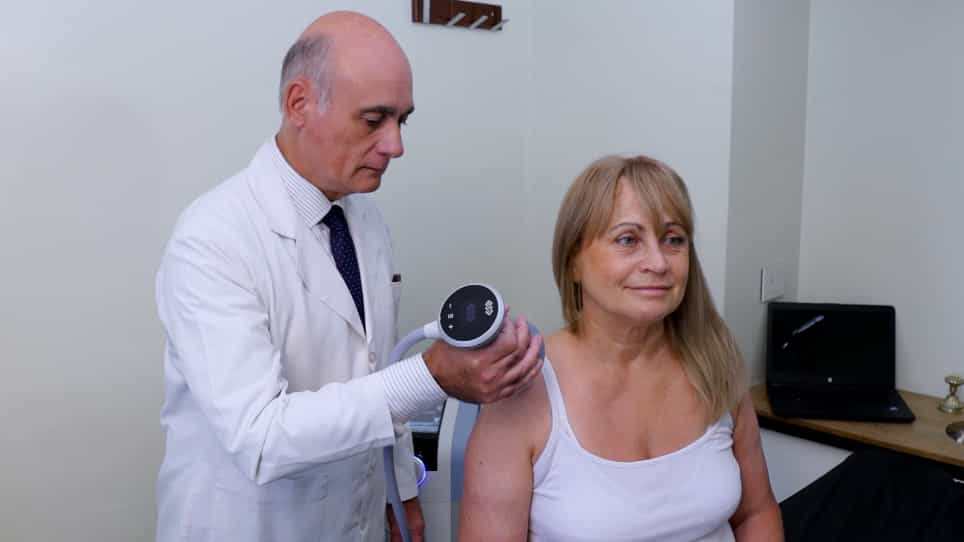
相关概念视频
 01:23
Muscles of the Shoulder
The muscles surrounding the shoulder girdle, including the clavicle and scapula, primarily stabilize the scapula. This stable base allows other muscles to move the humerus effectively. Scapular movements often mirror those of the humerus and extend its range of motion. For instance, raising the arm above the head would not be feasible without simultaneous upward rotation of the scapula.
Anterior Thoracic Muscles
The anterior thoracic muscles include the serratus anterior, subclavius, and...
Anterior Thoracic Muscles
The anterior thoracic muscles include the serratus anterior, subclavius, and...
 01:26
Flail Chest-II
Managing flail chest, a condition characterized by a segment of the chest wall moving independently from the rest of the thoracic cage, requires a comprehensive approach. It includes a thorough assessment of the patient's condition, a diagnostic evaluation to determine the extent of the injury, and the implementation of appropriate medical interventions tailored to the individual's needs.
Assessment:
1. Clinical Evaluation:
History:
Assessment:
1. Clinical Evaluation:
History:
 01:24
Chest Physiotherapy
Chest Physiotherapy (CPT) is a therapeutic technique used in respiratory care to improve ventilation, clear bronchial secretions, and enhance the efficiency of respiratory muscles. This therapy includes three primary procedures: postural drainage, percussion, and vibration. It can be performed on spontaneously breathing patients and those who are intubated and mechanically ventilated.
Purpose
CPT is primarily used for patients with excessive bronchial secretions who have difficulty clearing...
Purpose
CPT is primarily used for patients with excessive bronchial secretions who have difficulty clearing...
 01:25
Pericarditis IV: Nursing Management
Pericarditis, an inflammation of the pericardium, necessitates diligent nursing management to ensure effective patient care and recovery. The initial step in managing pericarditis is a comprehensive patient medical assessment.The patient reports chest pain aggravated by breathing, coughing, and swallowing, which worsens when lying supine. The pain often improves when sitting up and leaning forward. Additional symptoms may include fever, malaise, and, in severe cases, signs of heart failure.
 01:19
Acute Coronary Syndrome II: Pathophysiology and Clinical Manifestations
The pathophysiology of Acute Coronary Syndrome [ACD] involves several key processes:The main underlying cause of ACD is atherosclerosis, a chronic inflammatory disease characterized by the buildup of lipid-laden plaques within the coronary arteries.As the atherosclerotic plaque grows in the coronary artery, it may become unstable due to the formation of a lipid-rich core and a thin fibrous cap. Inflammatory cells within the plaque, such as macrophages, secrete enzymes that degrade the...
 01:21
Peripheral Arterial Disease II: Clinical Manifestations and Diagnostic Evaluation
Clinical manifestationsPeripheral Arterial Disease (PAD) manifests through a range of symptoms, from the characteristic intermittent claudication to atypical presentations and severe complications in advanced stages. Intermittent claudication, a hallmark symptom of PAD, presents as exercise-induced muscle pain that typically resolves within minutes of rest. This pain is reproducible and stems from inadequate blood flow, leading to the accumulation of lactic acid produced during anaerobic...