我们的轮子SPNing - 胰腺固体伪毛囊性瘤作为持续的十二指肠的外膜病因
Kanak V Kennedy1,2, Jibraan A Fawad1, Y Dana Neugut1
1Division of Gastroenterology, Hepatology, and Nutrition, Department of Pediatrics Children's Hospital of Philadelphia Philadelphia Pennsylvania USA.
JPGN reports
|May 19, 2025

概括
导致上部胃肠道出血的小儿十二指肠可能源于罕见的胰腺瘤. 这一案例突出显示了固体伪毛囊瘤 (SPNs) 是一个不寻常的外部原因,强调了需要怀疑复发性的必要性.
科学领域:
- 儿科胃肠病学 儿科胃肠病学
- 手术瘤学手术瘤学
- 胃肠道病理 胃肠道病理
背景情况:
- 由十二指肠引起的儿科上部胃肠道 (GI) 出血是一个危急的情况.
- 广泛的诊断可以导致这些.
- 胰腺瘤是十二指肠病理的一个不常见的原因.
研究的目的:
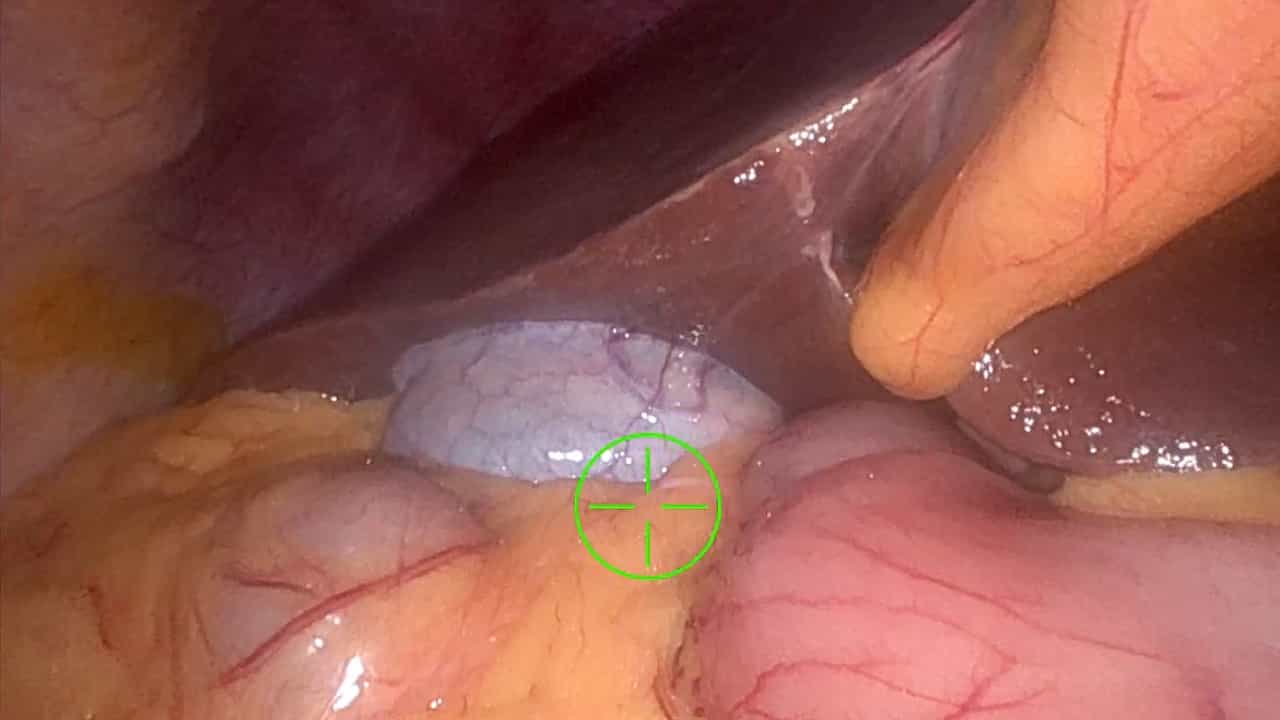
- 报告一例罕见的儿科十二指肠,由胰腺头部固体伪毛囊性瘤 (SPN) 引起.
- 强调SPNs是十二指肠的外部原因.
- 提高人们对复发十二指肠的外病因的认识.
主要方法:
- 案例报告的呈现方式.
- 对临床表现,诊断工作和管理的审查.
- 关于胰腺SPN和十二指肠病理学的文献综述.
主要成果:
- 一名儿科患者因十二指肠而出现反复的上部肠道出血.
- 发现是由胰腺头部的固体伪毛囊性瘤 (SPN) 引起的.
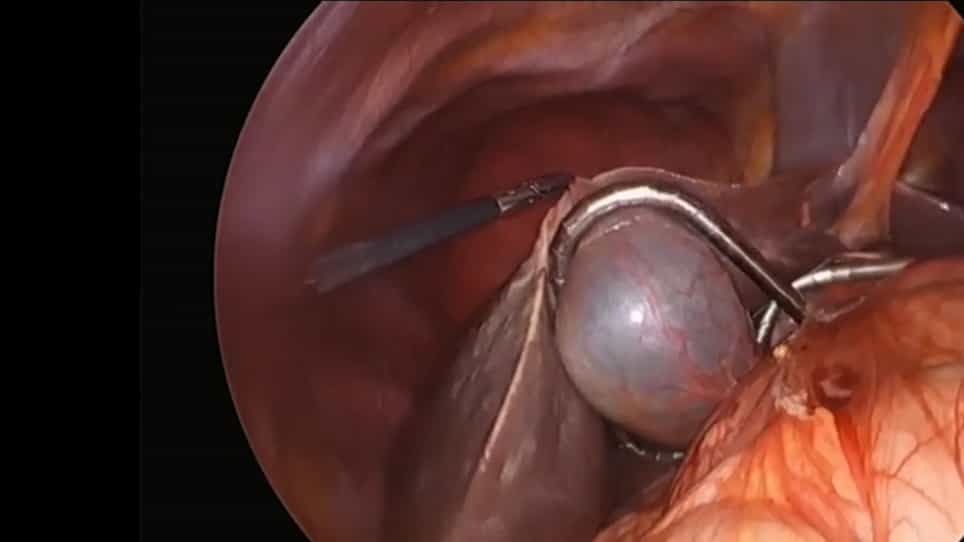
- 该SPN被确定为压缩十二指肠的外部质量.
结论:
- 胰腺SPNs是儿童十二指肠的罕见但重要的外部原因.
- 没有明显的内部原因的反复或渐进的十二指肠需要对外质量进行调查.
- 早期识别和诊断胰腺SPN对于儿童患者的有效治疗至关重要.
相关概念视频
 01:30
Peptic Ulcer Disease I: Introduction
111
Peptic Ulcer Disease (PUD) is characterized by mucosal excavation in the esophagus, stomach, pylorus, or duodenum. It can manifest as acute or chronic based on the extent and duration of mucosal involvement.
An acute ulcer, marked by superficial erosion and minimal inflammation, swiftly resolves upon identifying and addressing the underlying cause. In contrast, a chronic ulcer persists, potentially eroding through the muscular wall and forming fibrous tissue.
Peptic ulcers can also be...
An acute ulcer, marked by superficial erosion and minimal inflammation, swiftly resolves upon identifying and addressing the underlying cause. In contrast, a chronic ulcer persists, potentially eroding through the muscular wall and forming fibrous tissue.
Peptic ulcers can also be...
111
 01:24
Chronic Pancreatitis I: Introduction
56
The pancreas, an elongated and flat gland situated behind the stomach, serves a vital function in digesting food and managing blood sugar levels.
Pancreatitis is the inflammation of the pancreas, which occurs when the immune system becomes active and causes swelling, pain, and disruptions in organ function. Pancreatitis can manifest as either an acute or chronic condition.
Acute pancreatitis arises suddenly and lasts for a brief duration, while chronic pancreatitis is a long-term affliction...
56
 01:28
Peptic Ulcer Disease III: Clinical Manifestations and Diagnostic Studies
72
Peptic ulcer disease (PUD) presents with diverse symptoms depending on the location and severity of the ulcer. Clinical manifestations of peptic ulcer include dull pain and a burning sensation in the mid-epigastric region.
Few clinical manifestations differentiate gastric ulcers from duodenal ulcers. Distinctions in the location, timing, and pain relief are crucial for healthcare providers in differentiating between gastric and duodenal ulcers during clinical assessments.
Few clinical manifestations differentiate gastric ulcers from duodenal ulcers. Distinctions in the location, timing, and pain relief are crucial for healthcare providers in differentiating between gastric and duodenal ulcers during clinical assessments.
72
 01:28
Peptic Ulcer Disease II: Pathophysiology
183
Peptic Ulcer Disease (PUD) is characterized by the development of ulcers in the stomach or duodenal mucosa. Its pathophysiology is complex, involving a balance between damaging and protective elements.
Damaging agents such as Helicobacter pylori, gastric acid, pepsin, and nonsteroidal anti-inflammatory drugs (NSAIDs) can weaken the mucosal defense, allowing hydrogen ions to infiltrate back and harm epithelial cells.
Damaging agents such as Helicobacter pylori, gastric acid, pepsin, and nonsteroidal anti-inflammatory drugs (NSAIDs) can weaken the mucosal defense, allowing hydrogen ions to infiltrate back and harm epithelial cells.
183
 01:24
Pathophysiology of Peptic Ulcer Disease: Mucosal Defense Factors
327
Peptic ulcer disease, commonly called PUD, represents a multifaceted condition characterized by disruptions in the lining of the gastrointestinal (GI) tract. Central to the protection of the gastrointestinal lining is the mucosal-bicarbonate barrier. This physiological defense mechanism is a formidable shield against the corrosive effects of gastric acid and pepsin secretion in the stomach. Its role is pivotal in maintaining the structural integrity of the stomach's inner lining.
327
 01:26
Peptic Ulcer Disease IV: Management
55
Medical treatment strategies for peptic ulcers encompass various methods. The primary goal of treatment is to diminish gastric acidity and strengthen mucosal defense mechanisms.
The therapeutic approach involves ensuring adequate rest, implementing drug therapy, promoting smoking cessation, making dietary modifications, and emphasizing long-term follow-up care.
Pharmacological management
The prevailing therapy for peptic ulcers involves a combination of managing the patient's current...
55