相关实验视频
Updated: Jul 21, 2026
12:23
Granulocyte-dependent Autoantibody-induced Skin Blistering
Published on: October 12, 2012
10.6K
HLA-B*58:01 是阿洛普林醇诱导的严重皮肤不良反应的不完整预测剂
medRxiv : the preprint server for health sciences
|June 6, 2025

概括
这种HLA-B*58:01基因变异与阿洛普林醇诱导的严重皮肤不良反应 (SCAR) 密切相关. 第二个基因HLA-A*34:02也被确定为美国患者的独立风险因素.
科学领域:
- 药物基因组学 药物基因组学
- 免疫遗传学 免疫遗传学
背景情况:
- 在全球范围内,人类白细胞抗原 (HLA) -B*58:01等位基因是已知的史蒂文斯 - 约翰逊综合征/有毒表皮解 (SJS/TEN) 和带有异黄素和系统性症状 (DRESS) 的药物反应的已知危险因素.
- 然而,这种关联对包括美国在内的不同人群的概括性需要进行调查.
研究的目的:
- 在美国队列中研究HLA类I和II与氨醇诱导的SJS/TEN和DRESS (氨醇-SCAR) 的关联.
- 为了比较HLA携带在阿洛普林醇-SCAR患者与阿洛普林醇耐受性和一般人群对照.
主要方法:
- 使用范德比尔特大学医学中心 (VUMC) BioVU生物库进行了一项病例控制研究.
- 16名阿洛普林醇-SCAR患者与160名阿洛普林醇耐受性对照组和人口对照组进行了比较,年龄,性别和自我认同的种族相匹配.
- 进行了HLA类别I和II的类型化,并使用条件逻辑回归分析来确定显著的关联.
主要成果:
- 该研究确定了两个独立相关的HLAI类等位基因与增加的Allopurinol-SCAR风险.
- HLA-B*58:01显示出强烈的关联 (OR 28),证实了之前的发现.
- HLA-A*34:02被确定为一种新的,独立的风险因素 (OR 20.6). 没有发现有意义的HLAII类关联.
结论:
- HLA-B*58:01和氨醇-SCAR之间的关联可以对研究的美国人口进行概括.
- 在这个队列中,HLA-A*34:02代表了一种额外的独立基因风险因子,用于allopurinol-SCAR.
- 这些发现凸显了需要进行特定人群的遗传研究,以改善查,风险分层和诊断在基因多样化的群体中Allopurinol诱导的SCAR.

相关概念视频
 01:11
Pharmacogenetics of Drug Targets: β₂-Adrenergic Receptors, Apo E, Thymidylate Synthase
Genetic polymorphisms in drug targets have emerged as critical determinants of interindividual variability in drug response and toxicity. Pharmacogenomic investigations increasingly focus on identifying these variations to personalize and optimize therapeutic interventions. A drug target may be a receptor, enzyme, or signaling protein involved in pharmacologic responses or disease-related pathways. While early pharmacogenetic studies focused primarily on drug metabolism, current research...
 01:30
Drug Toxicity: Allergic Reactions
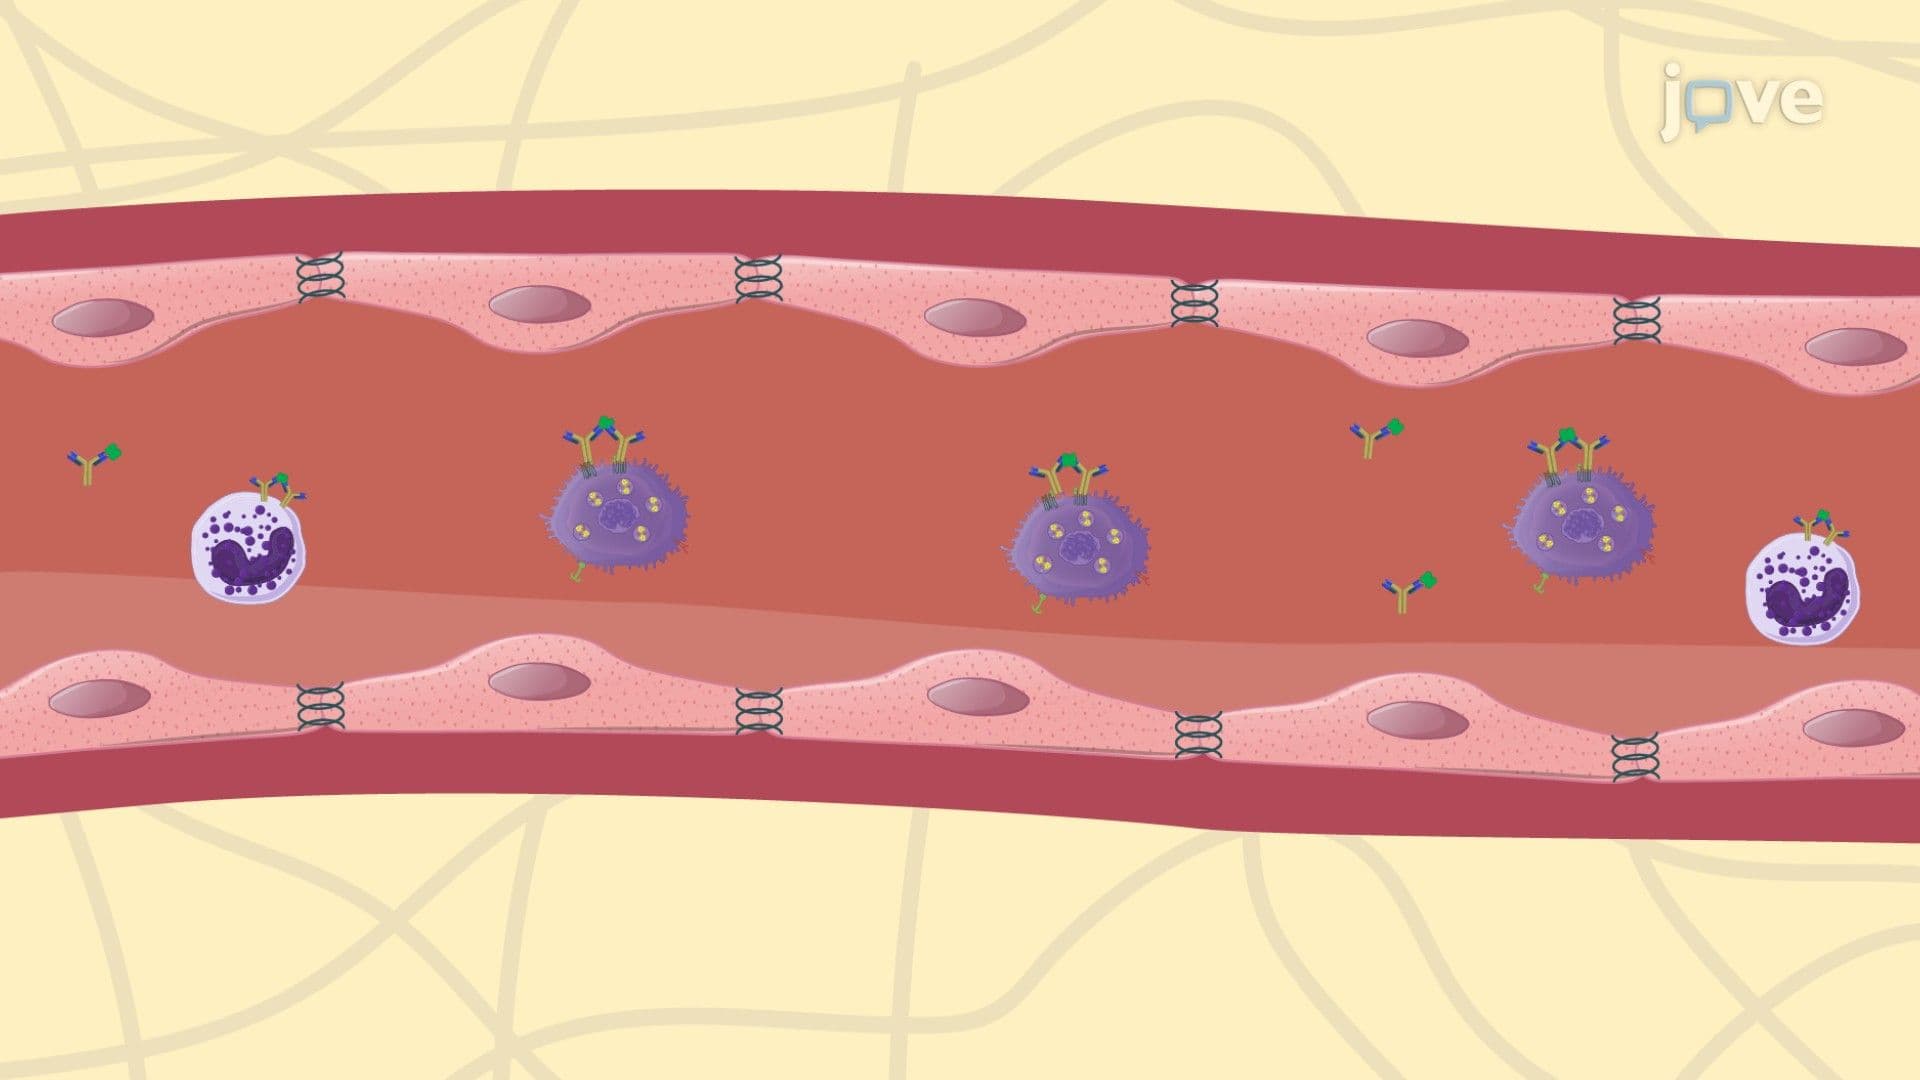
Drug-related allergies are immune-mediated responses triggered by the administration of pharmacological agents. These hypersensitivity reactions are classified based on the immune mechanisms involved. The four primary types—Type I, II, III, and IV—are mediated by different immunological pathways and exhibit distinct clinical manifestations.Type I Hypersensitivity/ IgE-Mediated Reactions: Immunoglobulin E (IgE) immediately mediates Type I hypersensitivity reactions. Upon initial exposure to a...
 01:01
Hypersensitivity Reactions: Cytolytic Reactions
Type II hypersensitivity involves IgG and IgM antibodies targeting cell surface antigens, leading to cell destruction. This can occur through complement activation, antibody-dependent cell-mediated cytotoxicity (ADCC), or acting as opsonins for phagocytosis. When excessive, these reactions cause significant tissue damage.Drug-induced hemolytic anemia is a common example, where drugs like penicillin or cephalosporins bind to red blood cells, forming drug-protein complexes. These complexes...
 01:29
Hypersensitivity Reactions: Delayed Hypersensitivity Reactions
Delayed-Type Hypersensitivity (DTH), or Type IV hypersensitivity, is a cell-mediated immune response. It occurs when T cells, rather than antibodies, mediate a reaction to specific antigens. It is characterized by a delayed onset (1-2 days) and involves the recruitment of macrophages to the inflammation site.The initiation of a DTH response begins with the sensitization of T cells. During this phase, which lasts at least 1-2 weeks, antigen-specific T cells are activated, clonally expanded, and...
 01:16
Drug toxicity: Idiosyncratic Reactions
Idiosyncratic drug reactions represent abnormal chemical responses that vary significantly among individuals, ranging from extreme sensitivity to low doses to insensitivity to high doses. These reactions often occur due to the drug's covalent binding with serum proteins, forming a foreign hapten that triggers an immunotoxicological response. The variability in drug reactions has a strong pharmacogenetic foundation, with genetic differences crucial in how individuals metabolize drugs. For...
 01:19
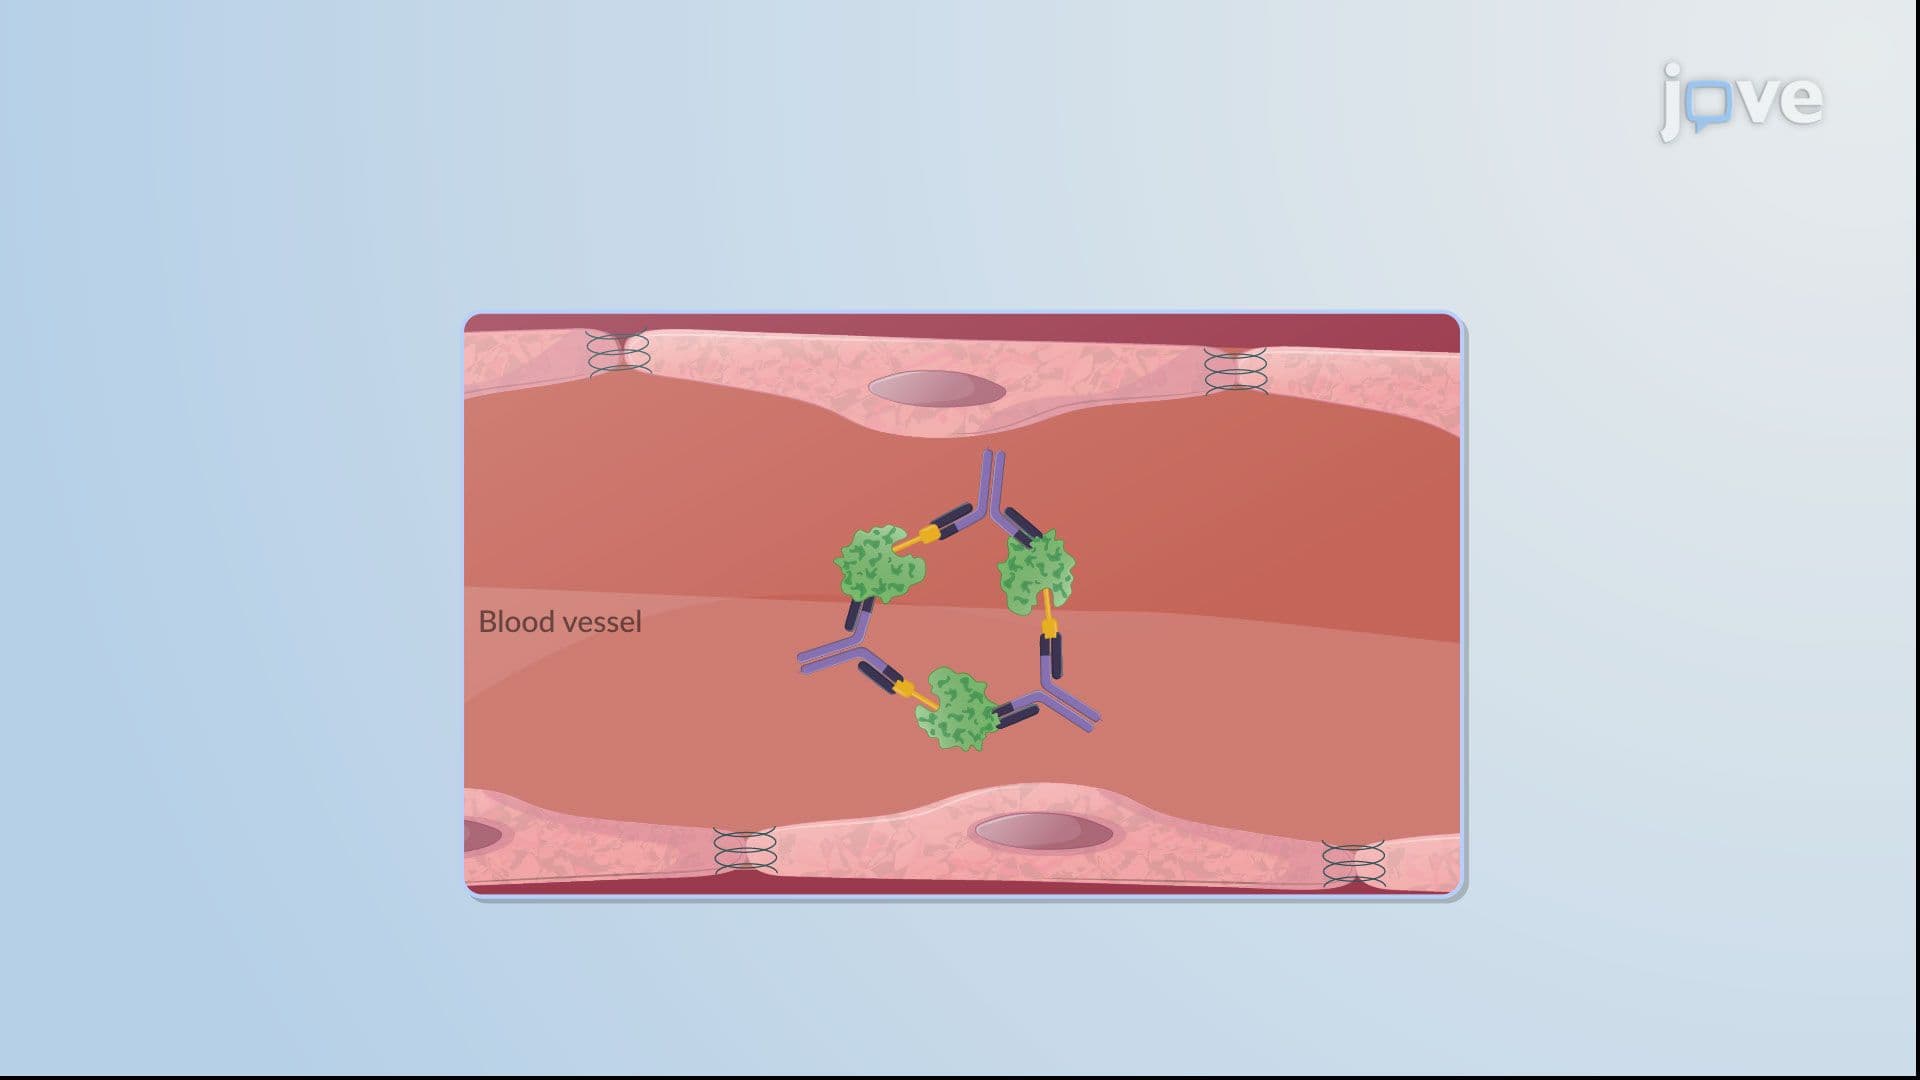
Hypersensitivity Reactions: Immune-Complex Reactions
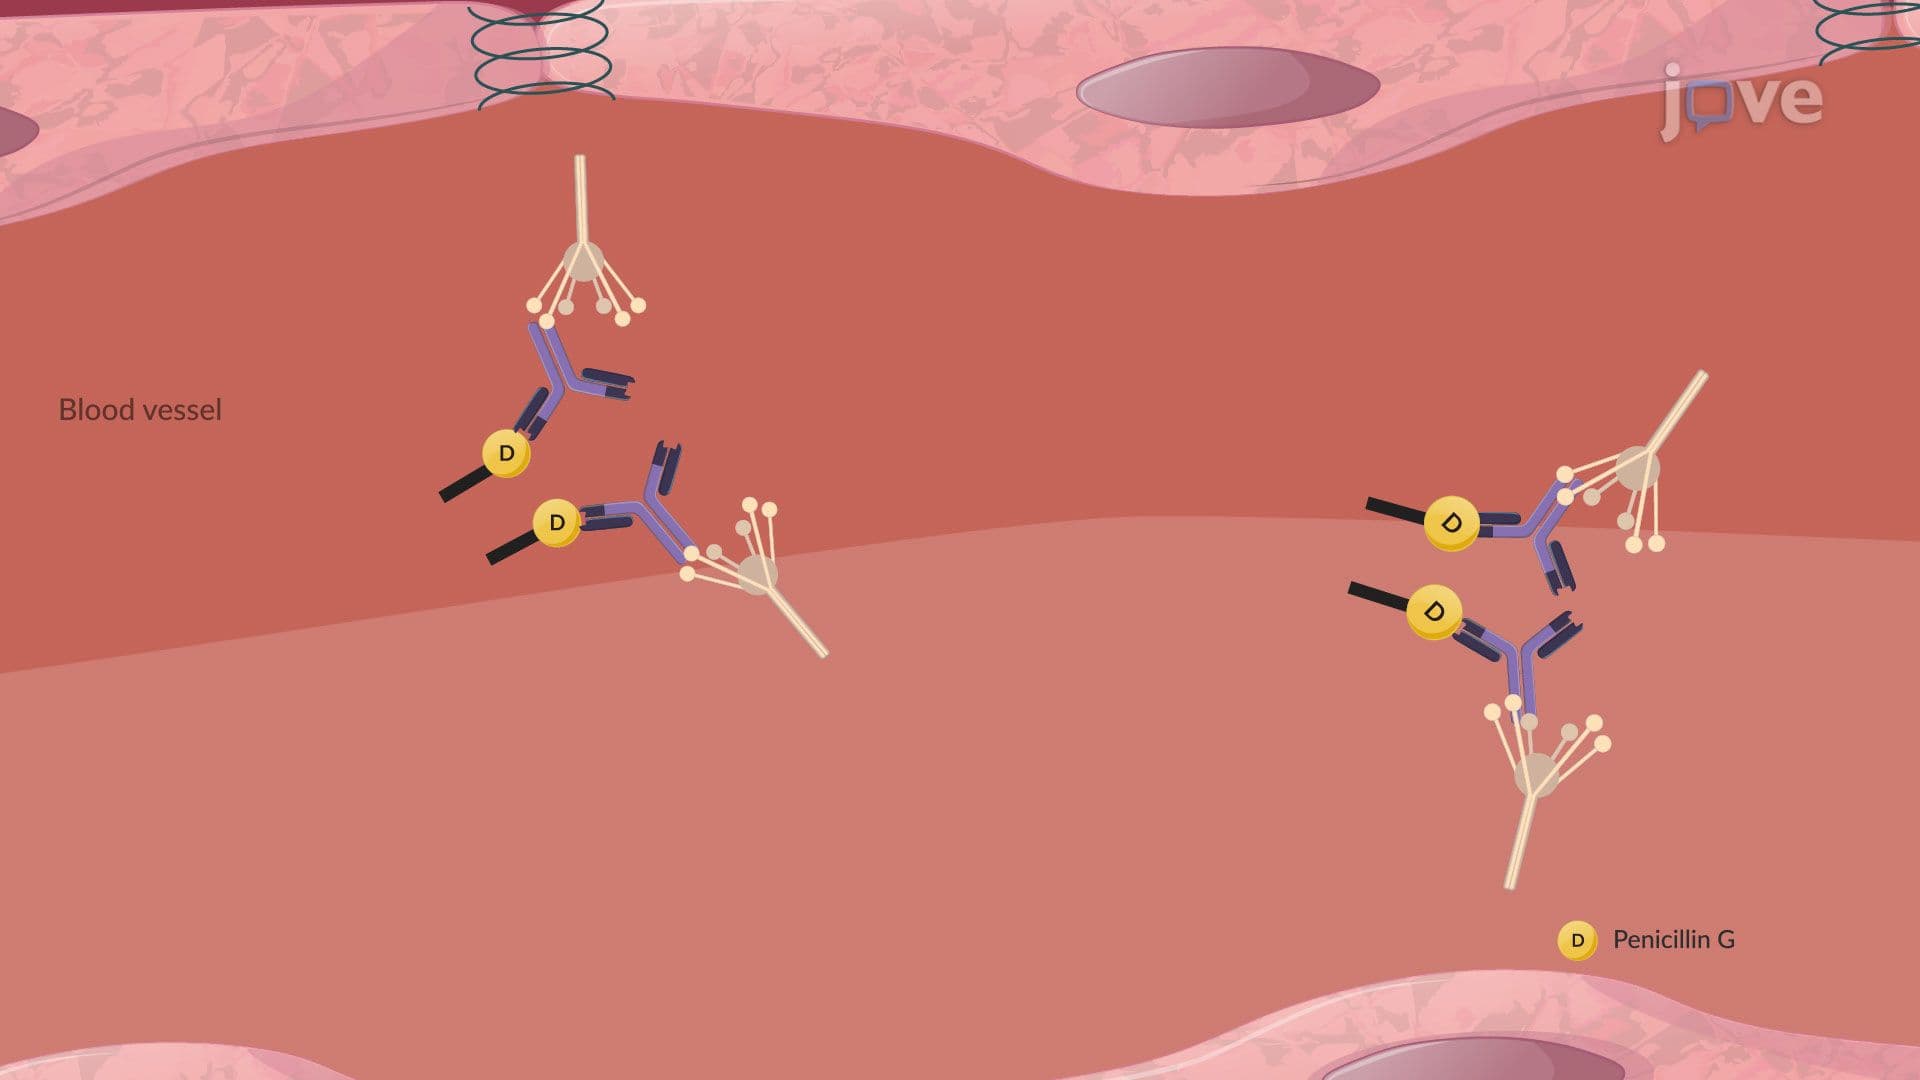
Type III hypersensitivity reactions occur when antigen–antibody complexes form and activate the complement system. Normally, these complexes help the clearance of antigens by phagocytes and red blood cells. However, when large numbers of immune complexes are present, they can deposit in tissues—particularly in the walls of blood vessels—leading to inflammation and tissue injury. These deposits trigger complement activation and neutrophil recruitment, resulting in serum sickness, a systemic...