相关实验视频
Updated: May 2, 2026
09:23
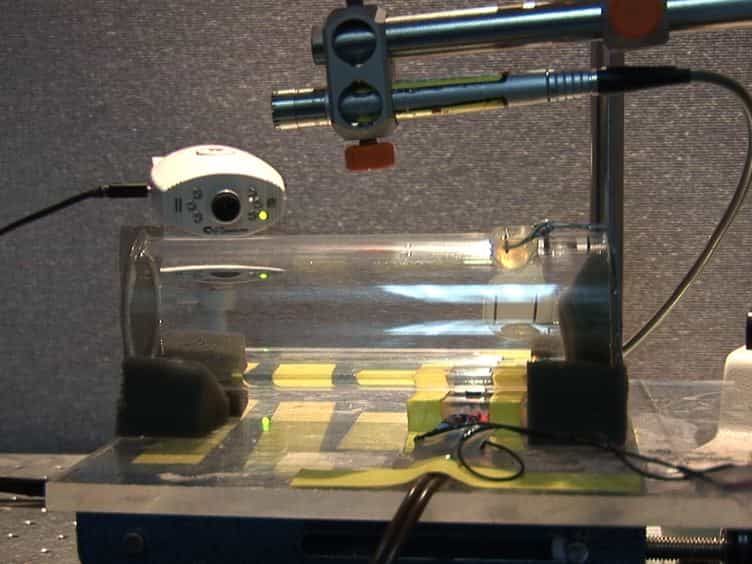
A Low Cost Setup for Behavioral Audiometry in Rodents
Published on: October 16, 2012
12.8K
高压氧气治疗启动延迟对急性声学创伤后的听觉结果的影响
Maayan Manheim1, Liel Mogilevsky1, Amit Geva1
1Israel Naval Medical Institute, Israel Defence Force Medical Corps, Haifa, Israel.
Diving and hyperbaric medicine
|June 21, 2025

概括
早期的高压氧 (HBO) 治疗可以改善声学创伤后的听力恢复. 在七天内治疗显著增加了积极的结果,响应率在三周后下降.
科学领域:
- 耳鼻喉科 耳鼻喉科 耳鼻喉科
- 紧急医疗 紧急医疗
- 航空航天医学 航空航天医学
背景情况:
- 由于暴露于强烈噪音的急性声学创伤可能导致严重的听力损失.
- 高压氧气 (HBO) 治疗正在作为一种辅助治疗来改善听力结果.
- 在声学创伤后启动HBO治疗的最佳时间尚不清楚.
研究的目的:
- 确定早期高压氧疗法 (HBO) 在急性声学创伤后改善听力方面的疗效.
- 建立HBO治疗启动的最佳时间框架,以最大限度地恢复听力.
主要方法:
- 患有急性声学创伤的患者接受了联合HBO和皮质类固醇治疗.
- 治疗包括80分钟253kPa的HBO,治疗数量根据反应进行调整.
- 主要结果:在高纯音频 (3-8 kHz) 中至少有10dB的改善. 二次结果包括高纯色总和 (HPTS) 变化和恢复战斗准备.
主要成果:
- 在七天内接受治疗的患者中,88%的患者实现了主要结局,而21+天后接受治疗的患者中,这一比例为56% (P = 0.002).
- 早期治疗 (7天内) 显示HPTS显著改善 (55dB对-5dB),HPTS相对改善 (55%对3%),并恢复战备状态 (57%对15%).
- 这些发现在调整年龄,初始听力损失和损伤机制后仍然存在.
结论:
- 早期启动高压氧 (HBO) 治疗对于改善急性声学创伤的治疗反应至关重要.
- 对于HBO来说,最佳的治疗延迟时间似乎是在受伤后的七天内.
- 延迟超过三周的HBO治疗与有效性显著降低有关.


相关概念视频
 01:16
Treatment for Pulmonary Arterial Hypertension: Oxygen Therapy for Respiratory Failure
817
Oxygen therapy has emerged as a significant tool in enhancing the quality of life for patients suffering from pulmonary arterial hypertension (PAH). While this therapy has principally been studied on patients with significant hypoxemia, this therapeutic approach helps prevent potential organ damage and can be administered in the comfort of one's home.
Oxygen therapy is vital in increasing and maintaining blood oxygen levels in PAH patients. As a result, it aids in reducing fatigue,...
Oxygen therapy is vital in increasing and maintaining blood oxygen levels in PAH patients. As a result, it aids in reducing fatigue,...
817
 01:29
Acute Respiratory Failure-V
768
The treatment for acute respiratory failure varies based on factors like the underlying cause, overall health, and severity. A collaborative healthcare team is essential for early detection, often through arterial blood gas analysis. Identifying the cause is the primary goal, with treatment strategies adjusted for ventilation/perfusion (V/Q) mismatch, shunting, or diffusion impairment.
Ensure that patients are monitored continuously for their response to therapy, including changes in...
Ensure that patients are monitored continuously for their response to therapy, including changes in...
768
 01:26
Pneumothorax-I
2.2K
A pneumothorax is a condition where air builds up in the space between the lung and the chest wall, causing the lung to collapse. This condition arises when air enters the space between the parietal and visceral pleura, disrupting the negative pressure essential for lung inflation. This can lead to a partial or complete collapse of the lung.
Pneumothorax can be even further classified as spontaneous, traumatic, and tension pneumothorax.
Pneumothorax can be even further classified as spontaneous, traumatic, and tension pneumothorax.
2.2K
 01:27
Pneumothorax-II
1.7K
Pneumothorax is a medical condition defined by the buildup of air in the pleural space between the lungs and the chest wall. This accumulation of air can lead to partial or complete lung collapse, resulting in a range of clinical manifestations. Understanding the clinical presentation and effective management strategies is crucial for healthcare professionals in providing timely and appropriate care to individuals with pneumothorax.
Clinical Manifestations:
Clinical Manifestations:
1.7K
 01:22
Cardiopulmonary Resuscitation II: ACLS Airway Management
1.2K
Airway management is a key skill in emergency and critical care settings, as maintaining a clear airway is essential for adequate oxygenation and ventilation.Head Tilt-Chin Lift TechniqueThe head tilt-chin lift maneuver is an essential technique primarily used in patients without suspected cervical spine injuries. To perform this maneuver, one hand is placed on the patient’s forehead, and gentle pressure is applied backward to tilt the head. The fingertips of the other hand are positioned...
1.2K
 01:10
Atelectasis II: Pathophysiology
40
Atelectasis develops when alveoli lose their air and collapse inward. Because lung tissue is naturally elastic, these air sacs shrink rather than remaining open. Collapsed alveoli are no longer ventilated, reducing their role in gas exchange. Blood flow may continue in these regions, creating a ventilation–perfusion mismatch. Clinical findings include decreased breath sounds, dullness to percussion, reduced chest expansion, and decreased tactile fremitus as sound transmission through...
40