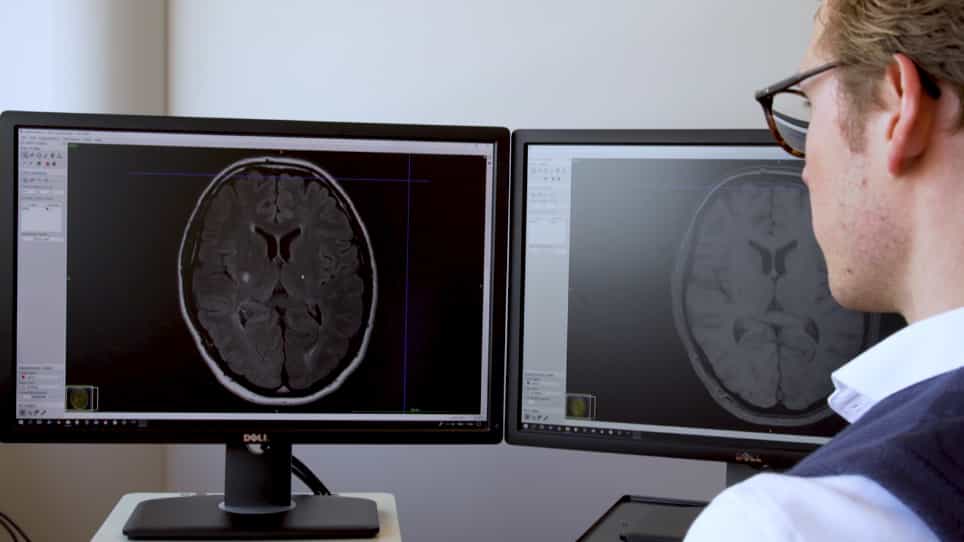

前部循环再通道化后CT超密度大血管封闭:缺血性中风后恶性脑的预测因素?
Alberto Ramponi1,2, Andrea Di Cristofori3, Francesca Graziano4,5
1Neurosurgery, Fondazione IRCCS San Gerardo dei Tintori, Via G.B. Pergolesi 33, Monza, 20900, Italy.

概括
针对急性缺血性中风 (AIS) 的机械血栓切除术 (MT) 可能仍然需要去压缩性脑膜切除术 (DC),这表明恶性病变的进展更快. 早期的指标,如体内高密度和中线转移,可以预测在MT后需要DC.
科学领域:
- 神经学 神经学
- 神经外科 神经外科
- 脑卒中医学 脑卒中医学
背景情况:
- 机械血栓切除术 (MT) 是急性缺血性中风 (AIS) 中大血管封闭 (LVO) 的关键治疗方法.
- 一些接受MT治疗的患者会发展出恶性脑和内高血压,可能需要进行解压性脑切除术 (DC).
- 当在中风发作后48小时内进行时,DC有效控制内高血压并降低死亡率.
研究的目的:
- 调查先前的MT是否影响DC的程序方面.
- 确定放射性指标,预测AIS患者在MT后需要DC的需要.
主要方法:
- 针对恶性前循环AIS进行DC的患者的回顾性研究 (2008年1月至2023年12月).
- 纳入标准:前部循环大血管AIS的血栓或栓塞起源.
- 在DC之前接受MT的患者 (MT组) 和没有接受MT的患者 (非MT组) 的比较.
主要成果:
- 与非MT患者 (49.77小时) 相比,在MT患者 (29.28小时) 中DC的执行时间更早.
- 在12小时内,在MT组 (66.7%) 和非MT组 (11.5%) 中,膜内超密度显著更高.
- 36小时的中线转移在MT组 (18名患者) 比非MT组 (12名患者) 观察到的频率更高.
结论:
- 对于前部循环LVO进行MT的患者,尽管再输血成功,但仍可能需要DC.
- 在需要DC的MT患者中观察到更快的恶性中风进展.
- 放射学指标可能有助于预测MT后DC的需要.
相关概念视频
 01:15
Ischemic Stroke ll: Pathophysiology
74
An ischemic stroke occurs when a cerebral blood vessel becomes obstructed, most often by a thrombus or embolus, interrupting the delivery of oxygen and glucose to brain tissue. Because neurons rely on continuous aerobic metabolism, energy failure begins within minutes of reduced perfusion. The region receiving the least blood flow becomes the infarct core, an area of irreversible cellular death. Surrounding this core lies the penumbra, a zone of hypoperfused but still viable tissue that is...
74
 01:29
Hemorrhagic Stroke ll: Pathophysiology
57
A hemorrhagic stroke develops when a cerebral blood vessel ruptures, allowing blood to escape into the surrounding brain tissue, as in intracerebral hemorrhage (ICH), or into the subarachnoid space, as in subarachnoid hemorrhage (SAH). Because the skull is a rigid compartment, the sudden presence of extravascular blood rapidly increases intracranial pressure and compresses adjacent neural structures, leading to immediate tissue injury and impaired cerebral perfusion.Mass Effect and Primary...
57
 01:19
Cerebral Edema l: Introduction
35
Cerebral edema is a pathological increase in brain water content that disrupts intracranial pressure regulation and impairs neurological function. Because the cranial vault is rigid, even modest increases in tissue volume can compromise cerebral perfusion, distort neural structures, and initiate secondary injury. Cerebral edema develops through four principal mechanisms: vasogenic, cytotoxic, interstitial, and ionic.Vasogenic EdemaVasogenic edema arises from disruption of the blood–brain...
35
 01:22
Cerebral Edema ll: Pathophysiology
31
Vasogenic edema is a major form of cerebral edema characterized by abnormal accumulation of fluid in the brain’s extracellular space due to disruption of the blood–brain barrier (BBB). The BBB is a specialized structure composed of endothelial cells connected by tight junctions, supported by astrocytic endfeet and a basement membrane. Under normal conditions, it tightly regulates the movement of ions, proteins, and solutes between the bloodstream and brain parenchyma. When this...
31
 01:21
Cytotoxic Edema: Pathophysiology
31
Cytotoxic edema is a form of cerebral edema characterized by intracellular swelling of neurons, astrocytes, and other glial cells. It develops when the mechanisms responsible for maintaining ionic gradients across the cell membrane become impaired. Under normal physiological conditions, the sodium–potassium ATPase actively transports sodium ions out of the cell and potassium ions into the cell, preserving osmotic balance and enabling electrical signaling. This pump requires a continuous...
31