
在ADPKD的托尔瓦普坦治疗患者中使用达帕格利弗洛辛:在回顾性研究中探索结局
Ryunosuke Nakajima1, Shun Minatoguchi1, Ryosuke Umeda1
1Department of Nephrology, Fujita Health University School of Medicine, Toyoake, Japan.
Clinical kidney journal
|September 29, 2025

概括
-葡萄糖共运输体2抑制剂 (SGLT2i) 显示,在接受托尔瓦普坦治疗的患者中,自身主导性多囊性病 (ADPKD) 患者的eGFR下降数量较慢. 没有观察到任何严重的不良事件,这表明ADPKD管理的潜在好处.
科学领域:
- 腎臟病學 (nephrology) 是一種醫學專業.
- 药理学 药理学是指药理学的学科.
- 遗传学 是一个遗传学.
背景情况:
- 自体主导多囊性病 (ADPKD) 是一种常见的遗传性病.
- -葡萄糖共传输体2抑制剂 (SGLT2i) 广泛用于慢性病 (CKD),但它们在ADPKD中的作用尚不清楚.
研究的目的:
- 为了评估达帕格利弗洛辛,SGLT2抑制剂,在已经接受托尔瓦普坦治疗的ADPKD患者的疗效.
- 评估达帕格利弗洛辛对ADPKD患者估计膜过率 (eGFR) 降低的速度的影响.
主要方法:
- 一项观察性研究涉及48名接受托尔瓦普坦治疗的ADPKD患者,分为对照组和达帕格利弗洛辛组.
- 主要结局:使用多变量线性混合效应模型分析慢性eGFR斜率.
- 二次分析:在达帕格利弗洛辛启动后,使用中断时间序列方法进行组内eGFR斜率变化.
主要成果:
- 平均随访时间约为649天.
- 在达帕格利弗洛辛和对照组之间没有观察到慢性eGFR斜率的统计学上显著差异 (-1.72 vs -2.30 mL/min/1.73 m2/year).
- 集团内部分析显示,在开始服用达帕格利弗洛辛后,eGFR下降速度较慢的趋势是不显著的 (P=.191). 没有报告任何严重的不良事件.
结论:
- 达帕格利弗洛辛在接受托尔瓦普坦治疗的ADPKD患者中显示出数字上较慢的eGFR下降,尽管在统计学上不显著.
- 该研究没有发现该患者群体中与达帕格利弗洛辛相关的危害证据.
- 这些发现有助于关于SGLT2抑制剂在管理ADPKD中的潜在治疗作用的持续讨论.


相关概念视频
 01:30
Acute Kidney Injury IV: Diagnostic Studies and Prevention
260
Accurate diagnosis and effective prevention are critical in managing Acute Kidney Injury (AKI), which is linked to high mortality rates ranging from 10% to 80%. Timely recognition of at-risk patients and careful monitoring can significantly reduce the likelihood of kidney damage.Diagnostic Assessments:The diagnostic process starts with a comprehensive medical history to identify prerenal, intrarenal, and postrenal causes.Prerenal causes, such as dehydration, hypotension, or blood loss, should...
260
 01:28
Drug Dosing in Renal Diseases: Estimation of Glomerular Filtration Rate Based on Serum Creatinine Concentration
190
Glomerular filtration rate (GFR) can be estimated from serum creatinine using the modification of diet in renal disease (MDRD) formula or the chronic kidney disease–epidemiology collaboration (CKD–EPI) equation. Both methods are widely used in clinical practice to assess kidney function and guide treatment decisions.The MDRD equation does not require weight or height measurements and is normalized to the body surface area of 1.73 m², considered the average adult surface area.
190
 01:25
Drug Dosing in Renal Diseases: Dose Adjustments Based on Drug Clearance and Elimination Rate Constant
209
In patients with renal disease, dosage adjustments are necessary to maintain therapeutic plasma drug concentrations and prevent toxicity or subtherapeutic exposure. Renal impairment alters drug pharmacokinetics, especially in conditions like uremia, where changes such as prolonged elimination half-life and altered apparent volume of distribution can significantly affect drug disposition. These changes require careful modification of the dosing regimen to achieve the desired clinical...
209
 01:06
Renal Drug Clearance: Overview
665
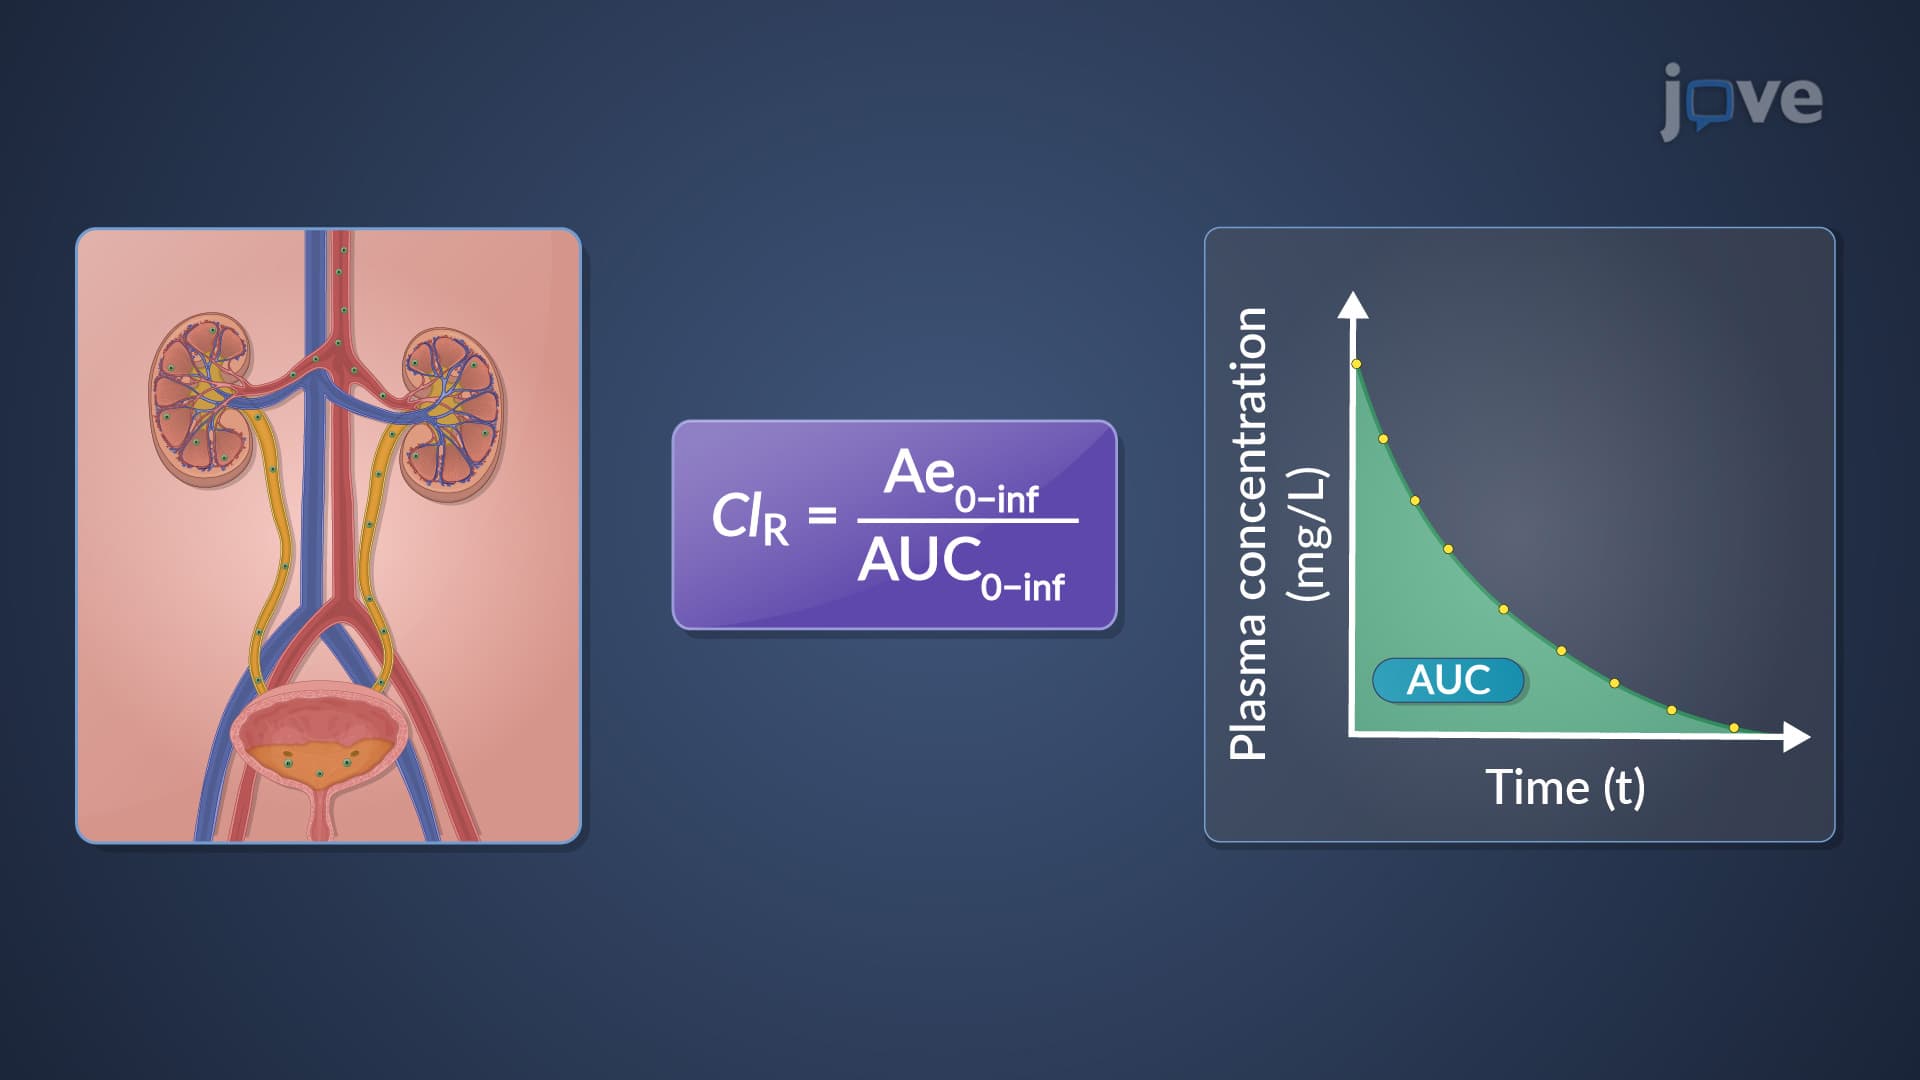
Renal clearance is a crucial parameter in pharmacokinetics that quantifies the rate at which the kidneys excrete a drug. It represents a constant fraction of the central volume of distribution containing the drug that the kidney eliminates per unit of time.
Renal clearance can be calculated using different methods. One approach is to divide the urinary drug excretion rate by the plasma drug concentration. This method directly measures renal clearance, indicating the kidneys' efficiency in...
Renal clearance can be calculated using different methods. One approach is to divide the urinary drug excretion rate by the plasma drug concentration. This method directly measures renal clearance, indicating the kidneys' efficiency in...
665
 01:25
Renal Drug Excretion: Tubular Reabsorption
745
Tubular reabsorption, a process occurring post-glomerular filtration of drugs in the renal tubule, is a critical determinant of drug half-life. During the process of renal excretion, as the glomerular filtrate progresses to the distal convoluted tubule (DCT), drugs that are highly permeable, lipophilic, and nonionized undergo passive reabsorption from the tubular fluid into the surrounding peritubular capillaries. This reabsorption process restricts their elimination through the kidneys. This...
745
 01:23
Dipeptidyl Peptidase 4 Inhibitors
594
Dipeptidyl peptidase 4 (DPP-4) is a serine protease widely distributed in the body. It's involved in the inactivation of GLP-1 and GIP hormones, which are crucial for insulin regulation. DPP-4 inhibitors, such as sitagliptin (Januvia), saxagliptin (Onglyza), linagliptin (Tradjenta), alogliptin (Nesina), and vildagliptin (Galvus), help increase the proportion of active GLP-1, enhancing insulin secretion. These inhibitors work by competitively binding to DPP-4. This binding causes a...
594