相关实验视频
Updated: Jun 25, 2026

13:01
Anti-Nuclear Antibody Screening Using HEp-2 Cells
Published on: June 23, 2014
137.1K
案例报告:非典型的抗GBM炎与亨诺赫-申莱因紫色炎共存:探索致病性结系
Yongxiu Huang1, Caihong Liu1, Wei Wei1
1Department of Nephrology, Kidney Research Institute, West China Hospital of Sichuan University, Chengdu, China.
Frontiers in immunology
|October 3, 2025

概括
这一案例突出显示了抗质底膜 (GBM) 炎和亨诺克-施恩莱因紫色炎 (HSPN) 的罕见重叠. 通过活检及及时免疫抑制疗法的早期诊断改善了患者的治疗结果.
科学领域:
- 腎臟病學 (nephrology) 是一種醫學.
- 免疫学 免疫学 免疫学
- 病理学 病理学 病理学
背景情况:
- 抗质底膜 (GBM) 炎通常涉及循环的抗GBM抗体.
- 血清阴性变体和以IgA沉积为特征的Henoch-Schönlein紫性炎 (HSPN) 可以同时出现.
- 由于报告的病例有限,这种重叠带来了诊断和治疗方面的挑战.
研究的目的:
- 描述一种独特的,同时存在的血清阴性抗GBM炎和HSPN的病例.
- 为了强调活检在复杂的淋巴结膜炎病例中的诊断效用.
- 为了突出联合免疫抑制疗法的有效性.
主要方法:
- 评估了一名16岁的女性,患有快速进展的淋巴细胞炎和紫外线.
- 对抗GBM抗体的血清测试呈阴性.
- 用免疫光进行脏活检以确定沉积模式.
主要成果:
- 光显微镜显示了细分型淋巴结核硬化.
- 免疫光检测显示了双重沉积:介质性IgA (HSPN) 和沿着GBM (抗GBM炎) 的线性IgG.
- 患者对包括葡萄糖皮质类药物,免疫抑制剂和等离子体酶在内的联合治疗反应良好,功能得到改善.
结论:
- 组织病理学检查对于诊断与HSPN重叠的血清阴性抗GBM炎至关重要.
- 早期和积极的免疫抑制治疗对于这种复杂的病例是有效的.
- 对共享的致病机制进行进一步的研究是有必要的.


相关概念视频
 01:20
Renal Corpuscle
The glomerulus and Bowman's capsule are two essential components of the nephron, which is the functional unit of the kidney. These microscopic structures play a critical role in the process of blood filtration to produce urine.
Glomerulus: Structure and Function
The glomerulus is a tiny, intricate network of capillaries located at the beginning of the nephron. It's enveloped by the Bowman's capsule and receives its blood supply from an afferent arteriole, which divides into numerous capillaries...
Glomerulus: Structure and Function
The glomerulus is a tiny, intricate network of capillaries located at the beginning of the nephron. It's enveloped by the Bowman's capsule and receives its blood supply from an afferent arteriole, which divides into numerous capillaries...
 01:27
Acute Pyelonephritis I: Introduction
Pyelonephritis is a bacterial infection that primarily affects the renal parenchyma and collecting system, including the renal pelvis, tubules, and interstitial tissue of one or both kidneys. It can be classified as either acute—a sudden, severe infection—or chronic, which refers to long-term or recurrent kidney infections.The primary cause of acute pyelonephritis (APN) is bacterial infection, with Escherichia coli accounting for approximately 70-80% of cases. Other bacteria, such as Proteus,...
 01:28
Acute Pyelonephritis II: Diagnostic Studies and Management
Introduction:For diagnosing acute pyelonephritis, a comprehensive patient history is collected to identify symptoms such as dysuria, frequent or urgent urination, flank pain, or costovertebral angle (CVA) tenderness that may suggest a kidney infection.Physical ExaminationDuring the physical examination, CVA tenderness is assessed. This involves gentle percussion over the costovertebral angle, where tenderness often indicates a kidney infection.Diagnostic TestsUrinalysis: Used to identify white...
 01:24
Nephrotic Syndrome I : Introduction
Nephrotic Syndrome is a chronic kidney disorder defined by clinical findings such as severe proteinuria, hypoalbuminemia, hyperlipidemia, and edema. These symptoms result from damage to the glomeruli, the kidney’s filtering units, increasing their permeability to proteins.Definition and Meaning:Proteinuria, defined as the loss of more than 3.5 grams of protein per day in adults, is a crucial feature of nephrotic syndrome. This condition is often accompanied by edema, the accumulation of fluid...
 01:26
Nephrotic Syndrome II : Assessment and Medical Management
IntroductionNephrotic syndrome is a kidney disorder marked by excessive protein loss in the urine, leading to various systemic complications. This condition often results from damage to the glomeruli—the kidney's filtering units—causing proteinuria, low blood protein levels, and fluid retention. Understanding the assessment, diagnosis, and management of nephrotic syndrome is essential for effective treatment and prevention of further kidney damage.AssessmentPatient History: Document any history...
 01:19
Hypersensitivity Reactions: Immune-Complex Reactions
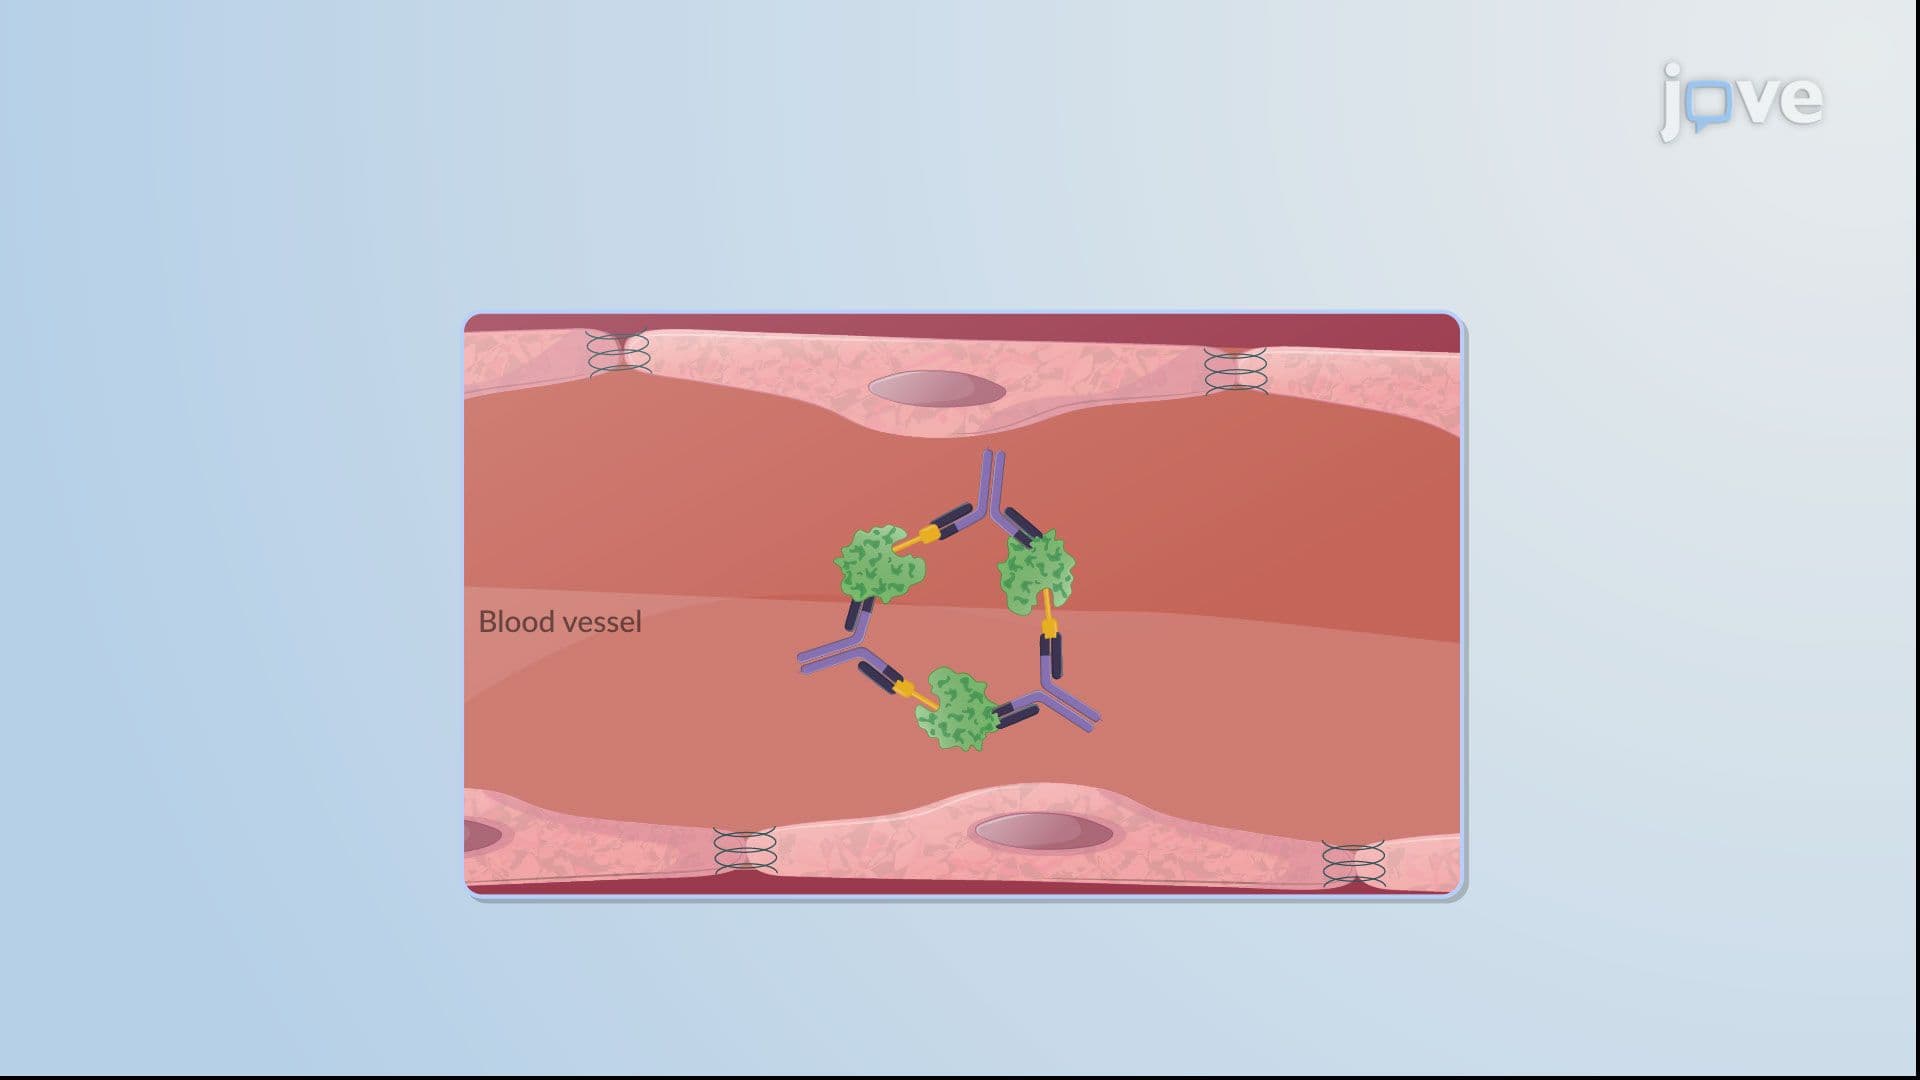
Type III hypersensitivity reactions occur when antigen–antibody complexes form and activate the complement system. Normally, these complexes help the clearance of antigens by phagocytes and red blood cells. However, when large numbers of immune complexes are present, they can deposit in tissues—particularly in the walls of blood vessels—leading to inflammation and tissue injury. These deposits trigger complement activation and neutrophil recruitment, resulting in serum sickness, a systemic...