相关实验视频
Updated: Jan 15, 2026

08:43

A Unified Methodological Framework for Vestibular Schwannoma Research
Published on: June 20, 2017
7.7K
在老年人中管理前体 schwannoma 的管理
Ahmed Helal1, Mathew L Carlson2, Michael J Link1
1Department of Neurologic Surgery, Mayo Clinic, Rochester, MN, United States.
Handbook of clinical neurology
|October 6, 2025

概括
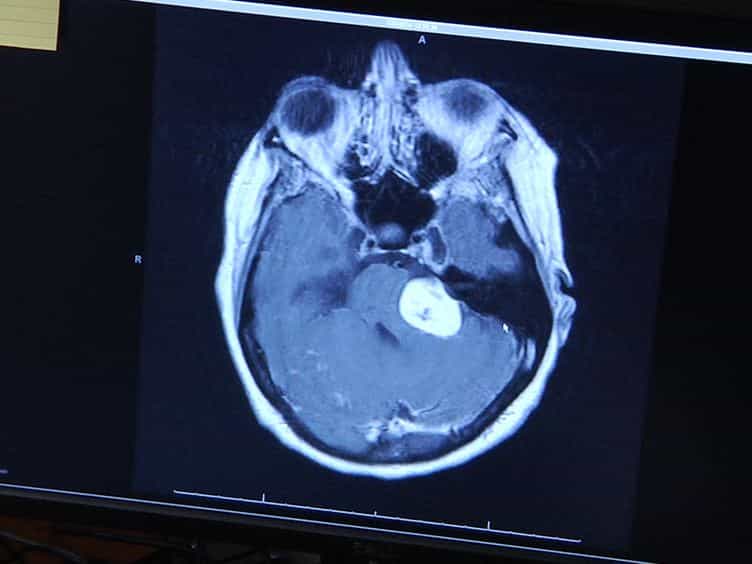
警等待和放射性外科手术在日益增长的老年人群中为前庭神经瘤 (VS) 提供了有效的管理. 这些方法优先考虑听力和面部神经的保护,这对生活质量至关重要.
科学领域:
- 神经外科 神经外科
- 耳鼻喉科 耳鼻喉科 耳鼻喉科
- 老年医学 老年医学
背景情况:
- 全球老年人口正在扩大,这导致老年人前置神经瘤 (VS) 诊断的发病率增加.
- 诊断工作的进步导致了早期检测VS,通常与较小的瘤大小和年龄较大.
- 垂体瘤表现出可变的生长模式,大约三分之一以每年2毫米的平均增长率生长,特别是较大的瘤.
研究的目的:
- 审查 vestibular schwannoma 的当前治疗策略,特别关注老年人群的挑战和考虑.
- 评估老年患者对VS进行保守管理 (警等待),放射性手术和微手术的疗效和结果.
- 根据瘤特征,患者年龄和风险因素,为选择最合适的治疗方式提供指导.
主要方法:
- 对专注于老年患者前庭神经瘤管理的研究进行文献综述.
- 对治疗结果的分析,包括瘤控制率,听力保护和面部神经功能.
- 不同的治疗方式的比较:警等待,放射性外科手术和微手术.
主要成果:
- 警的等待对于较小的瘤来说是一个可行的选择,提供高听力率和面部神经的保存.
- 放射性外科手术在长期随访中显示出>94%的瘤控制率和~57%的听力保存率,这对于高风险的老年患者来说是有利的.
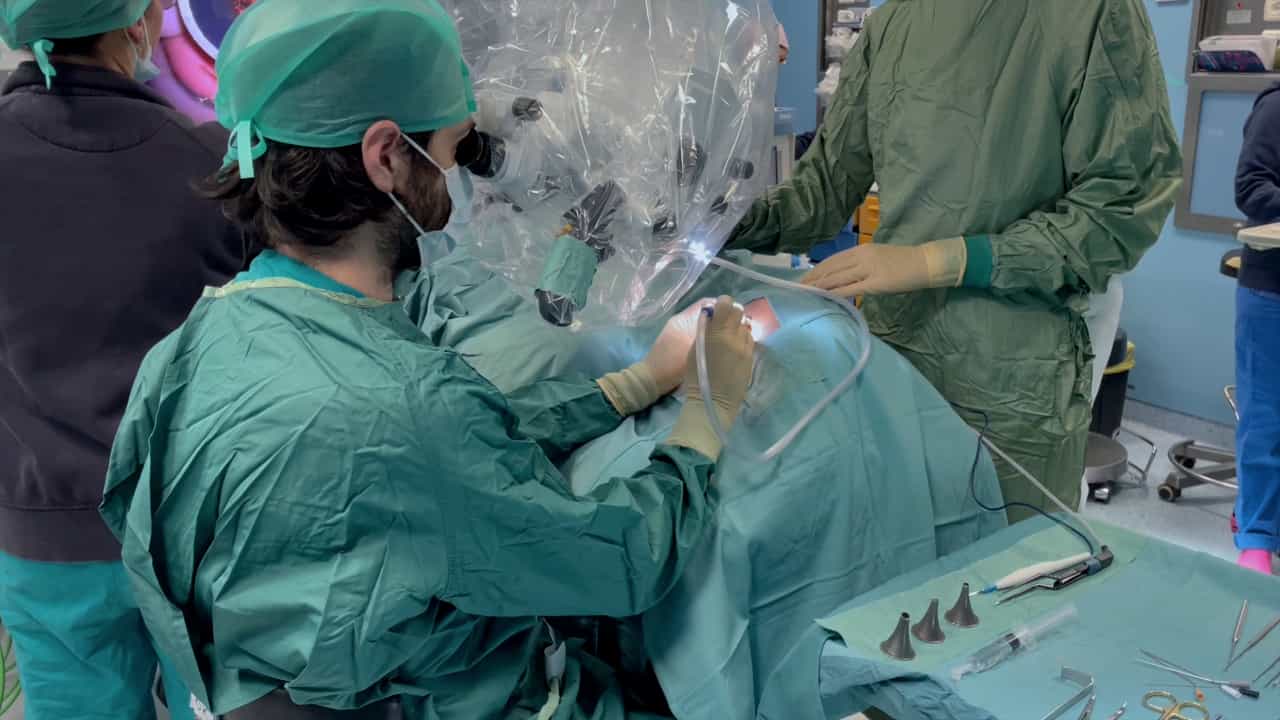
- 微手术仍然是一个可行的选择,选择的老年患者可接受的手术风险和Koo大4级瘤不适合放射性手术.
结论:
- 由于个体差异,老年人VS的标准化治疗缺乏,需要个性化方法.
- 警等待和放射性外科手术是有效的,器官保存的选择,用于管理老年人VS,特别是在较小或高风险的病例.
- 微手术仅适用于适合手术的老年患者或有瘤不能接受其他治疗的老年患者的特定症状.
相关概念视频
 01:15
Equilibrium and Balance
6.3K
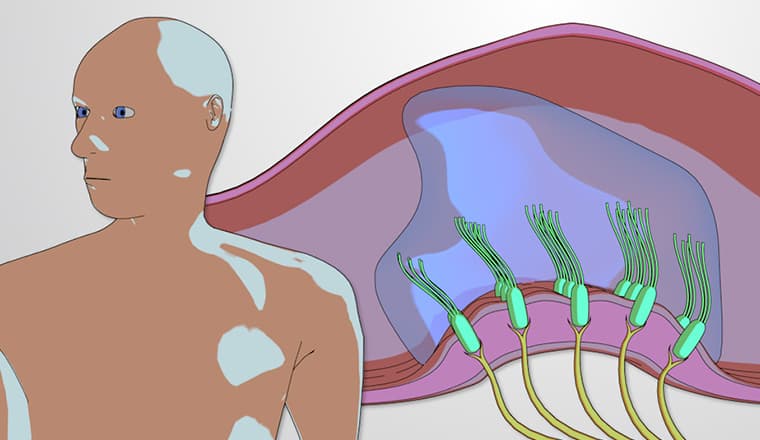
The inner ear assumes dual functionalities of auditory perception and equilibrium maintenance. The vestibule is the organ responsible for balance. This organ contains mechanoreceptors, specifically hair cells, endowed with stereocilia, which aid in deciphering information regarding the position and motion of our heads. Two intrinsic components, the utricle and saccule, help perceive head position, while the semicircular canals track head movement. Neurological messages initiated in the...
6.3K
 01:29
The Vestibular System
43.4K
The vestibular system is a set of inner ear structures that provide a sense of balance and spatial orientation. This system is comprised of structures within the labyrinth of the inner ear, including the cochlea and two otolith organs—the utricle and saccule. The labyrinth also contains three semicircular canals—superior, posterior, and horizontal—that are oriented on different planes.
43.4K
 01:26
Mitral Stenosis III: Medical Management
246
Mitral stenosis, a condition marked by the narrowing of the mitral valve, necessitates an integrated approach for effective management. This approach includes preventative measures, medical therapy, and surgical interventions to reduce symptoms and prevent complications.PreventionPrevention of mitral stenosis primarily focuses on reducing the incidence of bacterial infections, particularly streptococcal infections, which can lead to rheumatic fever and subsequent valvular damage. Timely...
246
 01:19
Mitral Valve Prolapse III: Nursing Management
289
The nursing management of Mitral Valve Prolapse, or MVP, centers around patient education, symptom monitoring, and lifestyle modifications.Patient Education on MVP Diagnosis and Heredity: Nurses should provide comprehensive education about MVP, a condition where the mitral valve does not close appropriately during heartbeats. This education often includes the condition's pathophysiology, symptoms, and potential complications, like arrhythmias or mitral regurgitation. Though not fully...
289
 01:22
Mitral Valve Prolapse II: Assessment and Management
418
IntroductionA range of clinical features characterizes Mitral Valve Prolapse (MVP), but it is important to note that many individuals with MVP are asymptomatic and may remain so throughout their lives. For those who do exhibit symptoms, the following are the key clinical features:Palpitations: This is a common symptom where individuals feel an irregular or rapid heartbeat. Palpitations in MVP are often due to arrhythmias such as premature ventricular contractions or supraventricular...
418
 01:25
Mitral Regurgitation III: Medical Management
279
Mitral regurgitation (MR) is characterized by retrograde blood circulation from the left ventricle into the left atrium due to inadequate mitral valve closure. The severity of the condition, symptoms, and underlying cause determine treatment strategies.Monitoring and Pharmacological TreatmentPatients with mild to moderate MR typically do not need immediate intervention but regular monitoring to assess progression and guide treatment. Patients with mild MR should have an echocardiogram every 3-5...
279