
儿科患者的塔克罗利斯Henoch-Schönlein紫色炎:目标度范围
Fashuang Li1, Huiying Li1, Linbo Li1
1Department of Pharmacy, Kunming Children's Hospital, Yunnan, China.

概括
确定塔克罗利斯在儿科亨诺克-申莱因紫性炎 (HSPN) 中的最佳治疗范围至关重要. 达克罗利斯的最低度为3-5 ng·mL-1在中国儿科患者中显示出最佳的疗效和安全性.
科学领域:
- 儿科脏病学 儿科脏病学
- 临床药理学 临床药理学
- 免疫抑制疗法是一种免疫抑制疗法.
背景情况:
- 亨诺克-施恩莱因紫色炎 (HSPN) 是儿童常见的血管炎.
- 塔克罗利斯是一种用于管理HSPN的免疫抑制剂.
- 优化tacrolimus的剂量对于儿科HSPN的疗效和安全至关重要.
研究的目的:
- 为了确定治疗参考范围的血中度塔克罗利斯在儿童患者的HSPN.
- 评估影响该群体中塔克罗利斯药理动学的因素.
- 为了确定最大限度地提高治疗疗效和最大限度地减少不良事件的最佳塔克罗利斯低度.
主要方法:
- 接收器操作特征 (ROC) 曲线分析以确定最佳的塔克罗利斯值.
- 在不同的塔克罗利斯度组中对临床疗效和不良事件的比较分析.
- 对缓解率和持续时间进行卡普兰-梅尔生存分析.
- 多变量线性回归以确定影响塔克罗利斯度的因素.
主要成果:
- 对于临床疗效,ROC分析确定了3.02 ng·mL-1的最佳塔克罗利斯最低度切线 (AUC=0.816,P<0.01).
- 较低的塔克罗利斯度 (<3 ng·mL-1) 显示有效性显著降低.
- 整体不良事件没有显著差异,但最高度组 (≥10 ng·mL−1) 的毒性较高.
- 血清肌素水平是塔克罗利斯度的重要决定因素.
结论:
- 对于中国儿科HSPN患者的最佳疗效,建议塔克罗利斯的最低度为3-5 ng·mL-1的治疗范围.
- 监测塔克罗利斯水平对于实现预期的治疗结果至关重要.
- 进一步的研究可能会探索基于患者因素的个性化剂量策略,如血清肌素.
相关概念视频
 01:26
Pharmacokinetics in Pediatric Patients: Drug Excretion
197
In pediatric medicine, understanding the renal function and drug elimination nuances is crucial for administering safe and effective treatments. Newborns, in particular, display markedly slower renal functions than adults, profoundly affecting how drugs are cleared from their bodies. This slower drug clearance requires clinicians to extend the dosing intervals for many medications to prevent drug accumulation and toxicity while ensuring therapeutic efficacy.One key area where these adjustments...
197
 01:11
Renal Failure: Dose Adjustments
416
In patients with renal impairment, drugs undergo significant changes in their pharmacokinetics, which require dosage adjustments to ensure safe and effective therapy.
Reduced renal clearance and elimination rate are common outcomes of renal impairment. These alterations lead to a prolonged elimination half-life and an altered apparent volume of distribution for drugs. As a result, dosage adjustments are typically necessary to maintain optimal drug levels in the body.
However, dosage adjustments...
416
 01:25
Drug Dosing in Renal Diseases: Measurement of Serum Creatinine Concentration and Clearance
173
In healthy individuals, serum creatinine levels remain stable due to a balance between its constant production—primarily from muscle metabolism—and renal excretion. Creatinine is freely filtered by the glomeruli, making it a valuable marker for estimating renal function. When the glomerular filtration rate (GFR) decreases, the kidneys can only eliminate less creatinine, causing serum levels to rise.Serum creatinine concentration is widely used to estimate creatinine clearance...
173
 01:15
Determination of Multiple Dosing Parameters: Steady-State, Minimum and Maximum Concentrations
226
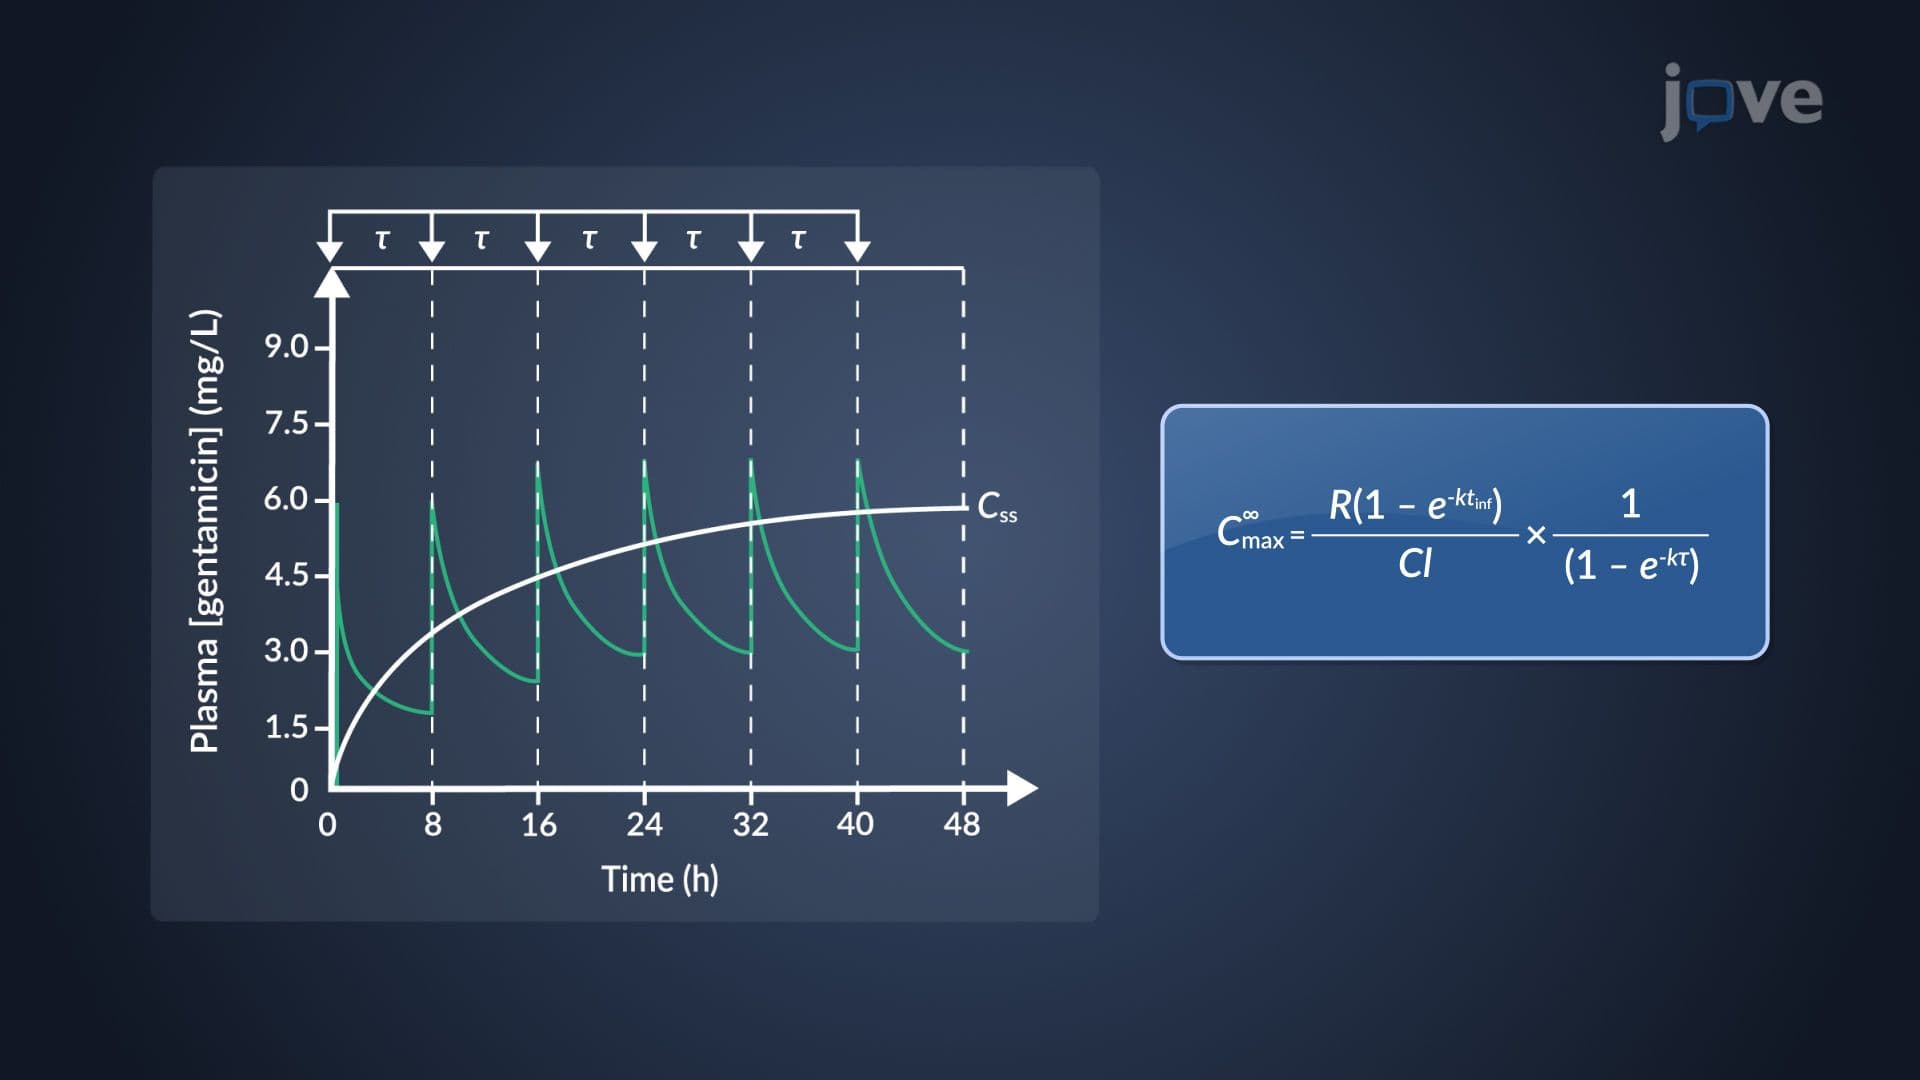
Gentamicin, an aminoglycoside antibiotic, is commonly administered via intermittent intravenous infusion to treat severe infections. An intermittent one-hour infusion of gentamicin, administered at eight-hour intervals, allows for precise control of plasma drug concentrations, minimizing toxicity while ensuring therapeutic efficacy. Pharmacokinetic principles govern the dynamics of plasma concentrations and can be mathematically described using specific equations.The plasma drug concentration...
226
 01:24
Pharmacokinetics in Pediatric Patients: Drug Metabolism
182
In pediatric care, understanding the nuances of hepatic drug metabolism is crucial, as it significantly differs from that of adults. This divergence is primarily due to the developmental stage of drug-metabolizing enzymes, which affects how medications are processed in the body. In neonates, for instance, the activity of Phase I enzymes—critical for the initial breakdown of drugs—is markedly reduced, functioning at just 20–40% of the levels seen in adults. This reduction poses...
182
 01:25
Drug Dosing in Renal Diseases: Dose Adjustments Based on Drug Clearance and Elimination Rate Constant
200
In patients with renal disease, dosage adjustments are necessary to maintain therapeutic plasma drug concentrations and prevent toxicity or subtherapeutic exposure. Renal impairment alters drug pharmacokinetics, especially in conditions like uremia, where changes such as prolonged elimination half-life and altered apparent volume of distribution can significantly affect drug disposition. These changes require careful modification of the dosing regimen to achieve the desired clinical...
200