
分析初始循环利尿剂剂量策略及其与时间与脱的关联
Gregory Taylor1,2, Jessica Starr1,3, Nathan Pinner1,3
1Department of Pharmacy Services, Baptist Health Princeton Hospital, Birmingham, AL, USA.

概括
较高的初始循环利尿剂剂量没有加快急性不补偿性心力衰竭 (ADHF) 患者的脱血速度. 虽然高剂量患者需要更少的利尿强化,但这并没有缩短住院时间.
科学领域:
- 心脏病学 心脏病学
- 药理学 药理学是指药理学的学科.
背景情况:
- 对于急性不补偿性心力衰竭 (ADHF) 的最佳循环利尿剂剂量缺乏可靠的证据.
- 目前的指导方针建议初始剂量至少是患者家庭治疗方案的两倍.
研究的目的:
- 评估较高的初始静脉循环利尿剂量是否能加速住院ADHF患者的脱血.
主要方法:
- 114名ADHF患者 (≥19岁) 接受IV循环利尿剂的回顾性单中心队列研究.
- 患者分为高剂量 (≥2.5倍家庭剂量) 和低剂量 (<2.5倍家庭剂量) 组.
- 主要结局:临床脱血时间.
主要成果:
- 在高剂量和低剂量组之间,时间到脱血没有显著差异 (P=0.44).
- 高剂量组显示,在24小时以后,尿液强化需要显著减少 (P=0.0001).
- 在较高的初始剂量和较短的住院时间 (LOS) 之间没有发现相关性.
结论:
- 较高的初始循环利尿剂量不会加速ADHF的脱.
- 在高剂量组中,降低了随后的利尿强化需求,但并没有转化为改善的LOS.

相关概念视频
 01:22
Heart Failure Drugs: Diuretics
763
Heart failure and kidney perfusion are interconnected in a complex way. Reduced renal perfusion and venous congestion are two significant factors that contribute to renal dysfunction in heart failure. The kidneys, primarily responsible for fluid balance in the body, are adversely affected due to compromised cardiac output and increased venous pressure. In response to reduced renal perfusion, the kidneys activate neurohumoral mechanisms to restore balance. However, these mechanisms can be...
763
 01:25
Drug Dosing in Renal Diseases: Dose Adjustments Based on Drug Clearance and Elimination Rate Constant
181
In patients with renal disease, dosage adjustments are necessary to maintain therapeutic plasma drug concentrations and prevent toxicity or subtherapeutic exposure. Renal impairment alters drug pharmacokinetics, especially in conditions like uremia, where changes such as prolonged elimination half-life and altered apparent volume of distribution can significantly affect drug disposition. These changes require careful modification of the dosing regimen to achieve the desired clinical...
181
 01:25
Determination of Multiple Dosing Parameters: Loading and Maintenance Doses
185
A loading dose is an essential pharmacological strategy to rapidly achieve the target plasma drug concentration necessary for an immediate therapeutic effect. This approach is especially critical for drugs characterized by slow absorption or extended half-lives, where delaying therapeutic plasma levels could compromise treatment outcomes. By administering a loading dose, clinicians ensure a prompt onset of drug action, even for agents with complex pharmacokinetic profiles.Achieving steady-state...
185
 01:24
Drug Accumulation During Multiple Dosing: Intermittent IV Infusions
209
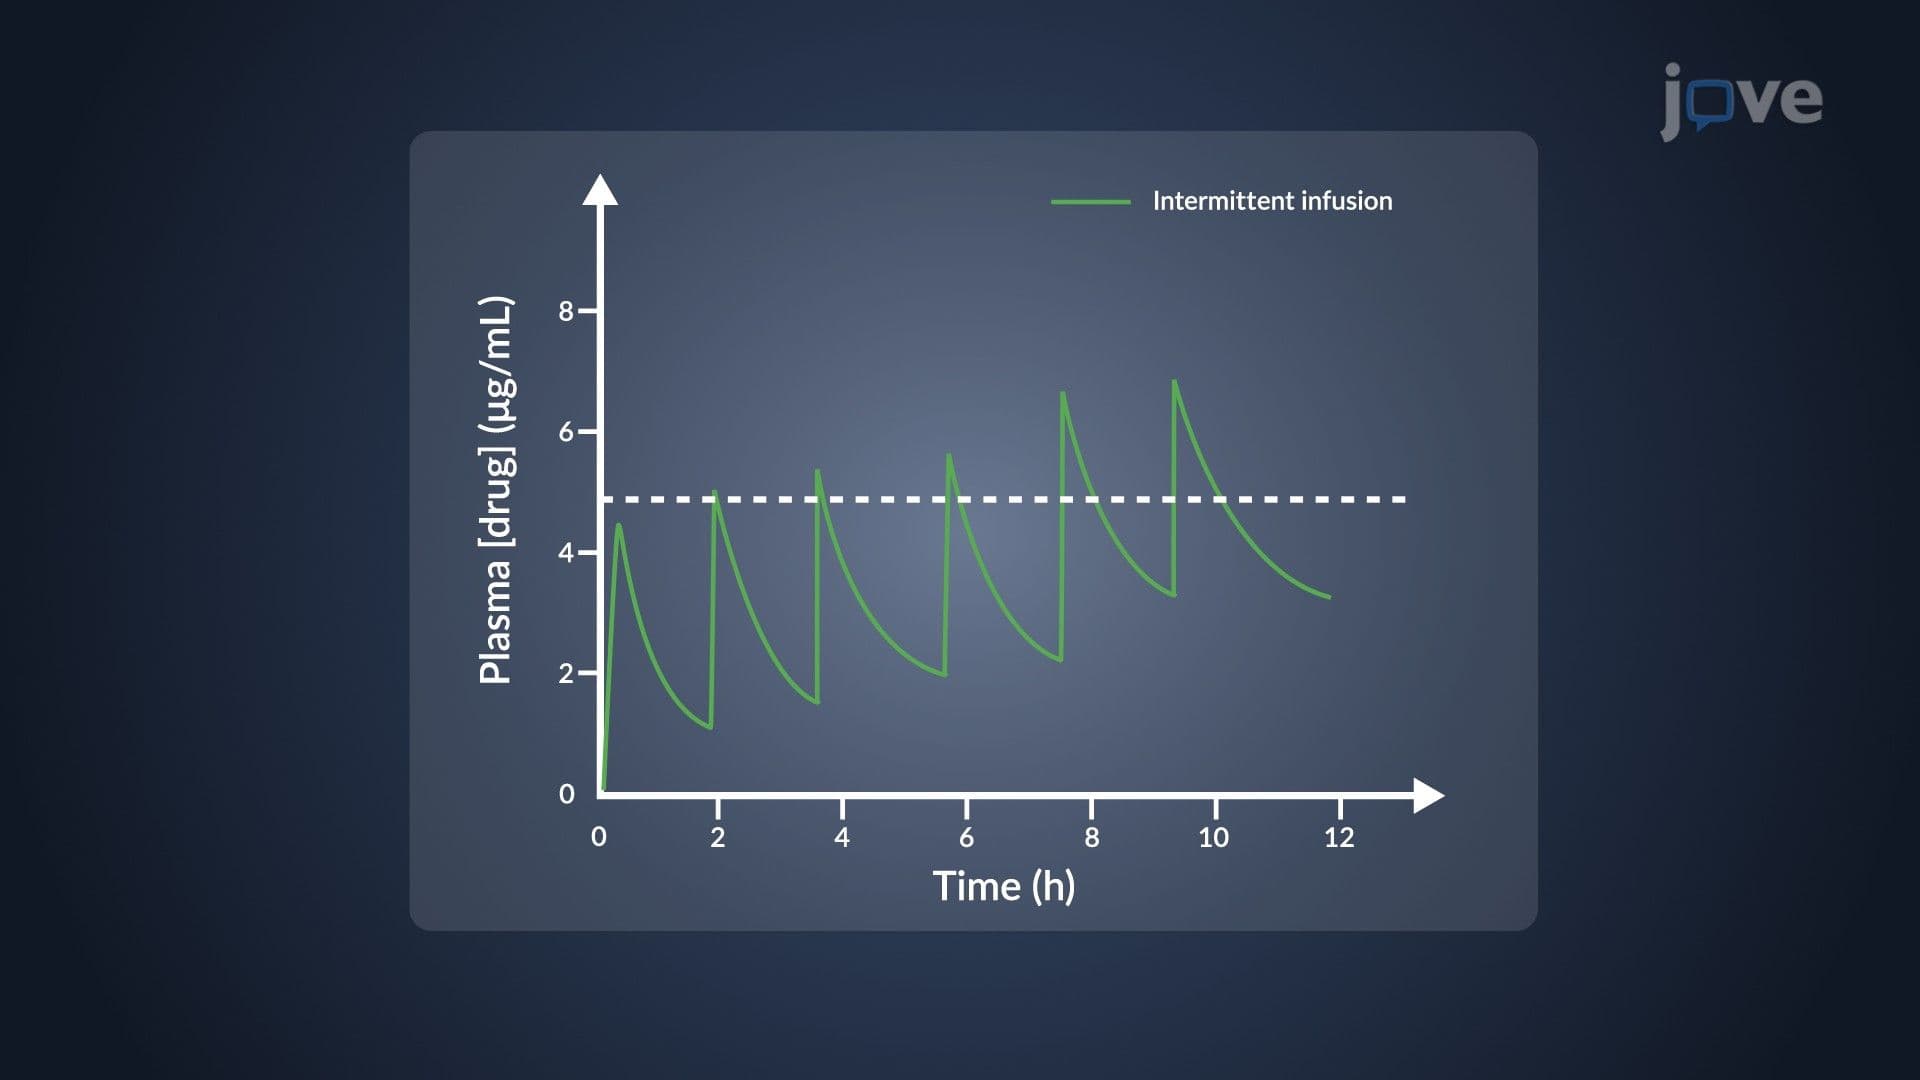
Intermittent intravenous (IV) infusion is a method of drug administration where medications are delivered over short infusion periods followed by intervals of no drug delivery. This approach helps to prevent sustained high drug concentrations in the bloodstream, reducing the risk of adverse effects associated with prolonged exposure. Unlike continuous infusion, steady-state concentrations may not be achieved during a single dosing cycle but can be reached through repeated...
209
 01:21
Drug Accumulation During Multiple Dosing: Repetitive IV Injections
221
Calculating drug dosage and accumulation in multiple-dose regimens is crucial for achieving therapeutic efficacy while avoiding toxicity. This involves determining the plasma drug concentrations over time to optimize dosing schedules. The principle of superposition is fundamental in this process, allowing for the prediction of drug concentration in plasma following multiple doses based on single-dose data.The principle of superposition asserts that the plasma concentration-time curves from...
221
 01:28
Dosage Regimens: Designs and Approaches
227
Designing a dosage regimen, which refers to the manner of drug administration, is a complex process involving the selection of drug dose, route, and frequency. This process is underpinned by pharmacokinetic parameters derived from tests and population averages. These parameters are then tailored to patient-specific variables such as diagnosis, demographics, and allergy status. Once therapy commences, therapeutic response monitoring is critical and achieved through clinical and physical...
227