

重构自发性肺胸部:PLEX变种分类的实用指南
Mohan Venkatesh Pulle1, Harsh Vardhan Puri1, Arvind Kumar1
1Department of Thoracic Surgery, Institute of Chest Surgery, Medanta, Gurugram, India.
Asian cardiovascular & thoracic annals
|January 7, 2026

概括
新的PLEX分类通过根据肺模式,泄漏位置,疾病程度和手术复杂性对病例进行分类来改善自发性肺胸病的管理,提高手术规划和预测结果.
科学领域:
- 胸部外科手术 胸部外科手术
- 肺部医学 肺部医学
- 诊断成像 诊断成像 诊断成像
背景情况:
- 目前的初级-二级自发性肺胸的分类缺乏外科相关性.
- 电脑图像扫描通常会忽略微妙的肺部异常,这对于手术规划至关重要.
- 需要一个与肺胸部相关的临床框架.
研究的目的:
- 引入自发性肺胸的PLEX分类系统.
- 为分类肺胸部提供一个更具运作相关性的框架.
- 改善手术规划,沟通和预测肺胸病例的结果.
主要方法:
- 普莱克斯分类的发展:肺部异常的模式,泄漏和肺部储备的位置,疾病的程度,预期的手术复杂性和手术结果.
- 将其分为四种变体:I型 (尖端脆弱性),II型 (多球性),III型 (肺性) 和IV型 (纤维性肺).
- 在710个胸腔镜手术中应用和验证PLEX分类.
主要成果:
- 该PLEX分类表明,从I型到IV型的手术难度和并发症增加的明显梯度.
- PLEX有效地根据特定的肺异常和预测的手术结果对肺胸变异进行了分类.
- 该系统在大型队列中被证明是务实和手术可行的.
结论:
- 与传统方法相比,PLEX分类为自发性肺胸部提供了一个优越的框架.
- PLEX 增强了手术规划,手术期间的沟通和术后的结果预测.
- 这种分类系统对于优化自发性肺胸外科手术管理至关重要.


相关概念视频
 01:27
Pneumothorax-II
884
Pneumothorax is a medical condition defined by the buildup of air in the pleural space between the lungs and the chest wall. This accumulation of air can lead to partial or complete lung collapse, resulting in a range of clinical manifestations. Understanding the clinical presentation and effective management strategies is crucial for healthcare professionals in providing timely and appropriate care to individuals with pneumothorax.
Clinical Manifestations:
Clinical Manifestations:
884
 01:26
Pneumothorax-I
1.1K
A pneumothorax is a condition where air builds up in the space between the lung and the chest wall, causing the lung to collapse. This condition arises when air enters the space between the parietal and visceral pleura, disrupting the negative pressure essential for lung inflation. This can lead to a partial or complete collapse of the lung.
Pneumothorax can be even further classified as spontaneous, traumatic, and tension pneumothorax.
Pneumothorax can be even further classified as spontaneous, traumatic, and tension pneumothorax.
1.1K
 01:22
Cardiopulmonary Resuscitation II: ACLS Airway Management
512
Airway management is a key skill in emergency and critical care settings, as maintaining a clear airway is essential for adequate oxygenation and ventilation.Head Tilt-Chin Lift TechniqueThe head tilt-chin lift maneuver is an essential technique primarily used in patients without suspected cervical spine injuries. To perform this maneuver, one hand is placed on the patient’s forehead, and gentle pressure is applied backward to tilt the head. The fingertips of the other hand are positioned...
512
 01:25
Pleural Effusion I: Introduction
3.9K
Pleural effusion is an abnormal fluid accumulation in the pleural cavity, a narrow space between the lungs and the chest wall. It is not a disease per se but rather a symptom or indication of an underlying disease. In normal circumstances, this space contains a small amount of fluid (5 to 15 mL), a lubricant facilitating the non-frictional movement of the pleural surfaces.
There are two main types of pleural effusion: transudative and exudative. They are differentiated using Light's...
There are two main types of pleural effusion: transudative and exudative. They are differentiated using Light's...
3.9K
 01:13
Pleura of the Lungs
6.3K
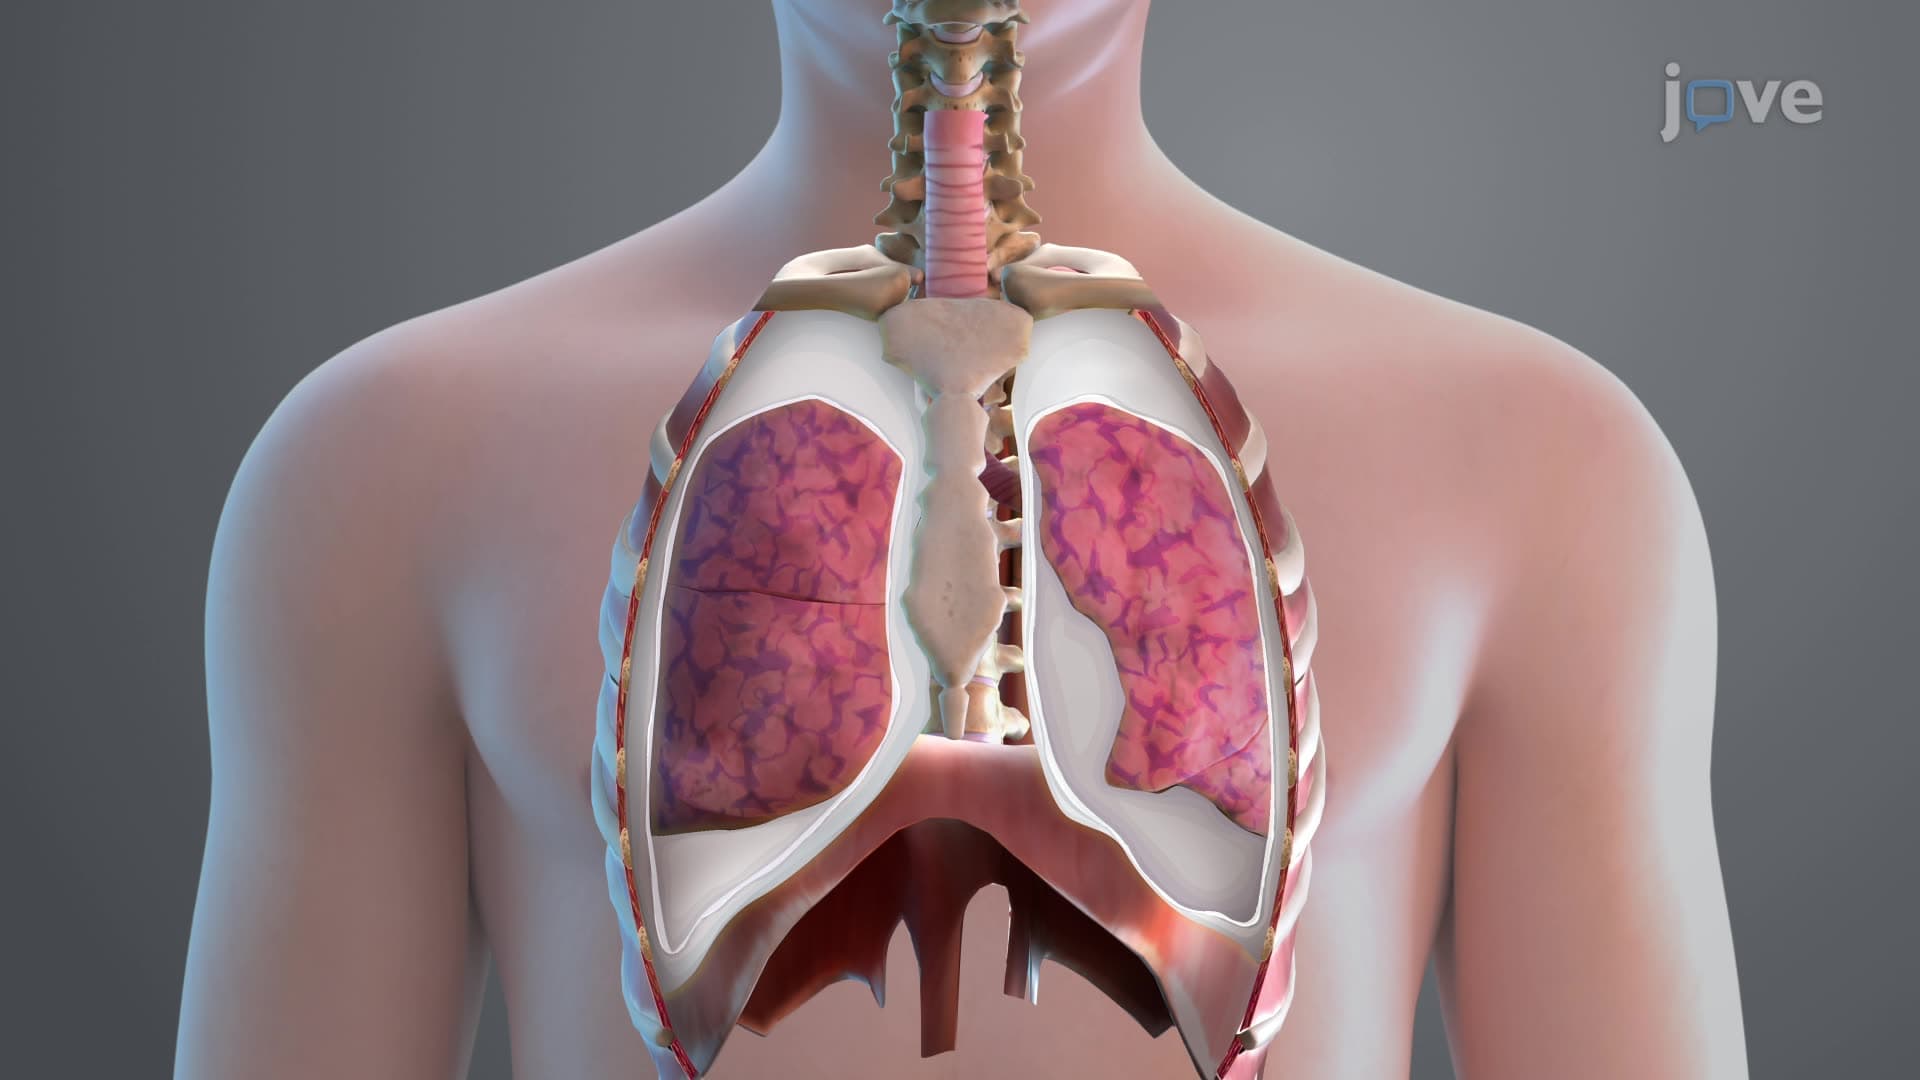
The lungs are nestled in a cavity, shielded by the pleura. The pleura, a form of serous membrane, wraps around each lung. This membrane arrangement consists of two layers: the visceral and parietal pleurae. The visceral pleura lines the surface of the lungIn contrast, the parietal pleura is the outer layer and contacts to the thoracic wall, the mediastinum, and the diaphragm. The hilum is the point of connection between the visceral and parietal layers. The space between the parietal and...
6.3K
 01:26
Flail Chest-II
516
Managing flail chest, a condition characterized by a segment of the chest wall moving independently from the rest of the thoracic cage, requires a comprehensive approach. It includes a thorough assessment of the patient's condition, a diagnostic evaluation to determine the extent of the injury, and the implementation of appropriate medical interventions tailored to the individual's needs.
Assessment:
1. Clinical Evaluation:
History:
Assessment:
1. Clinical Evaluation:
History:
516