
为什么在心脏骤停时优先使用上腺素? 答案可能在于β-上腺素受体激活
Anastasios Lymperopoulos1, Alexis J M'Sadoques1, Renee A Stoicovy1
1Laboratory for the Study of Neurohormonal Control of the Circulation, Department of Pharmaceutical Sciences (Pharmacology), Barry and Judy Silverman College of Pharmacy, Nova Southeastern University, Davie/Ft. Lauderdale, FL 33328-2018, USA.
Frontiers in bioscience (Landmark edition)
|January 8, 2026

概括
上腺素 (Epi) 是一种重要的心脏骤停治疗. 它对β-2上腺素受体 (β2AR) 的独特激活增强了心脏功能和心肺复苏期间的血液流动,使其与其他血管压缩剂区别开来.
科学领域:
- 心脏病学 心脏病学
- 药理学 药理学是指药理学的学科.
- 紧急医疗 紧急医疗
背景情况:
- 上腺素 (Epi) 是根据高级生命支持 (ALS) 准则在心肺复苏 (CPR) 期间的心脏骤停的主要治疗方法.
- 在CPR中,Epi与其他血管压缩剂的特定药理优势尚未完全理解.
研究的目的:
- 探索上腺素 (Epi) 独特的药理特性,这些特性可能会在心肺复苏 (CPR) 期间提高其有效性.
- 要突出Epi对β-2上腺素受体 (β2AR) 激活在改善心脏功能和心脏骤停期间患者的结果中的关键作用.
主要方法:
- 这是一篇意见文章,提出基于现有药理知识的理论论证.
- 这篇文章的重点是将Epi的作用机制与其他血管压缩剂,特别是上腺素 (NE) 的作用机制进行比较.
主要成果:
- 上腺素独特地激活β-2上腺体受体 (β2AR),这种特性与其他血管压缩剂 (如诺亚上腺素 (NE)) 没有共同之处.
- 通过Epi的β2AR激活增强了心脏起器细胞脉冲生成,并通过/的激活恢复缺血性心肌细胞的收缩功能.
- 与其他血管压缩剂相比,这些β2AR介导的作用为Epi提供了提高心脏输出和组织 perfusion 的卓越能力.
结论:
- 上腺素的β2AR激活是区分其在心肺复苏中的有效性与其他血管抑制剂的关键因素.
- 上腺素独特的药理特征使其在简单的血压升高不足的情况下特别有价值,例如在心脏骤停期间.

相关概念视频
 01:26
Adrenergic Receptors: β Subtype
3.4K
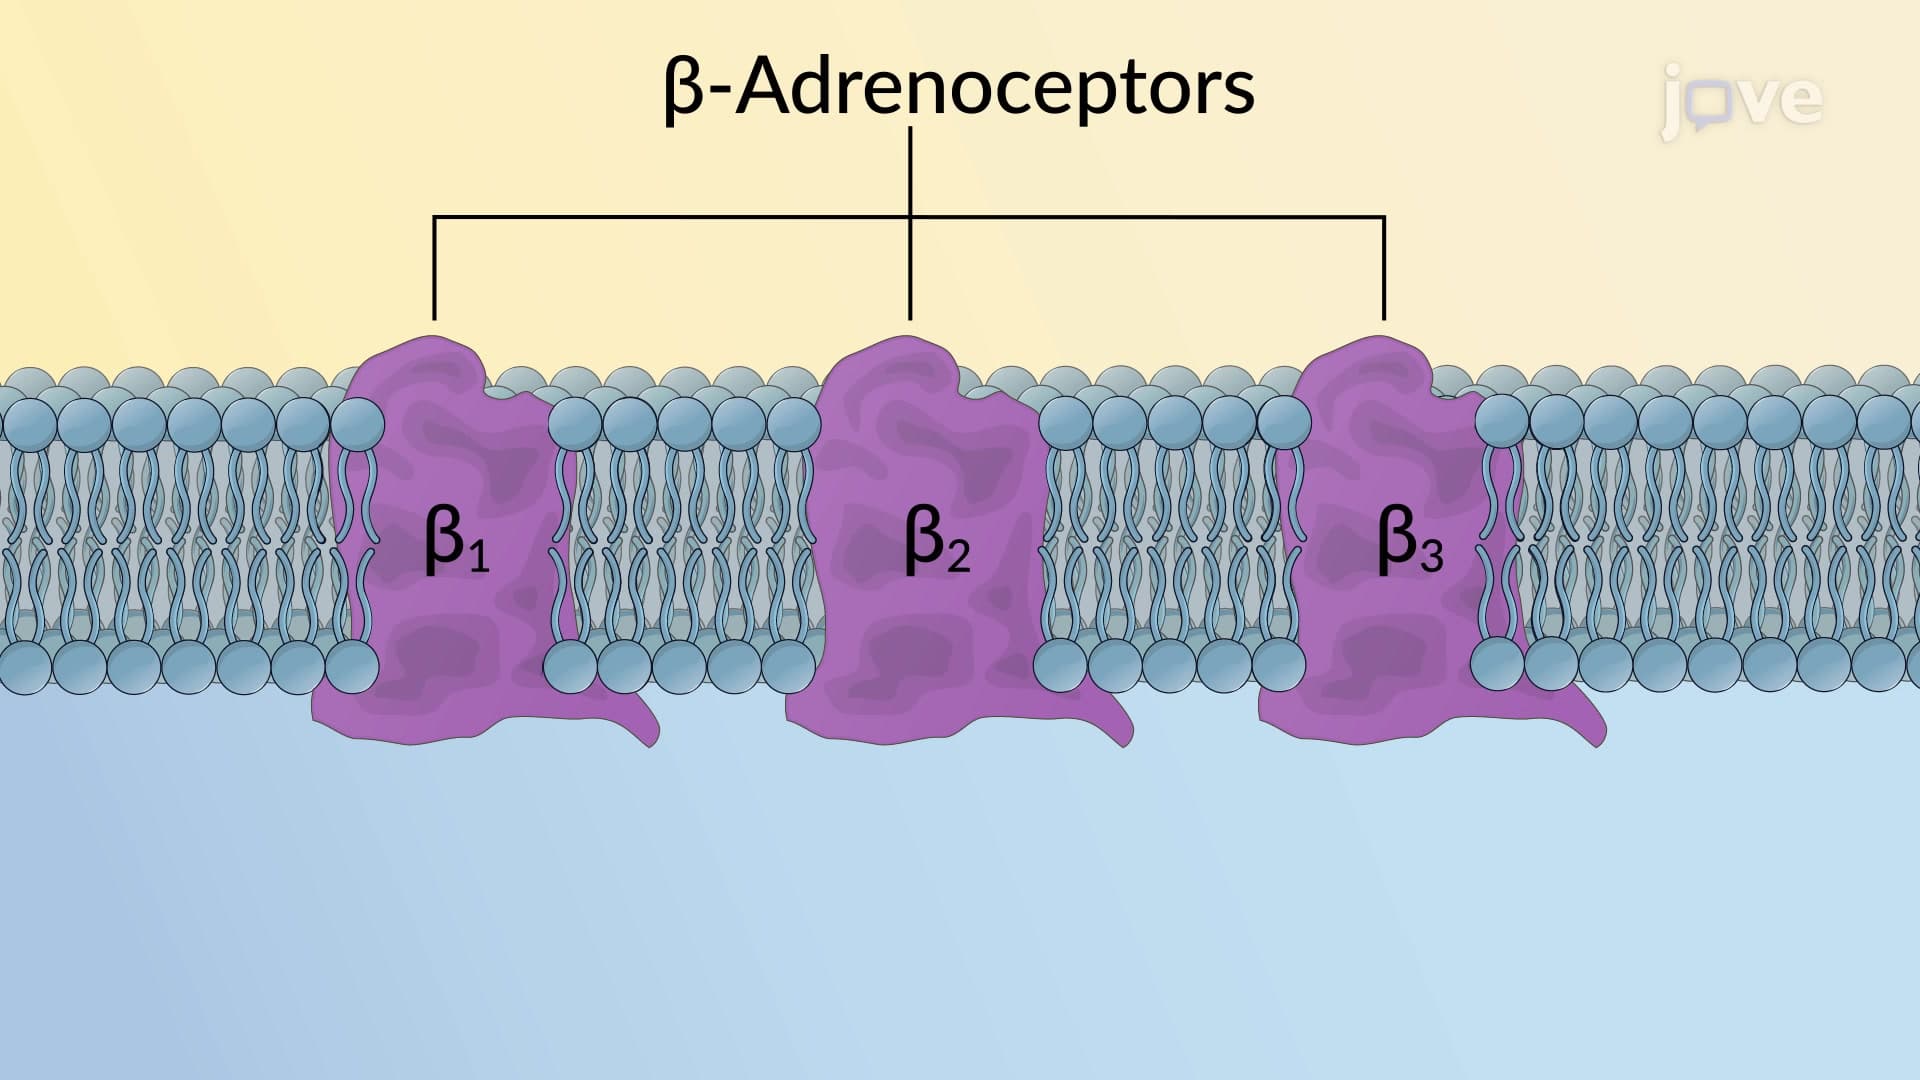
β-adrenoceptors have varied sensitivities towards adrenaline, noradrenaline, and isoprenaline. The order of agonist potency is as follows:
Isoprenaline > Adrenaline > Noradrenaline
Neurotransmitter binding to these receptors causes activation of adenylyl cyclase resulting in increased concentrations of cAMP and modulation of calcium ion channels within the cell. They are further classified into β1, β2, and β3 subtypes.
β1-adrenoceptors: β1-adrenoceptors...
3.4K
 01:25
Cardiopulmonary Resuscitation IV: Pharmacological Management
639
Pharmacologic intervention is crucial in treating cardiac arrest patients during ACLS or Advanced Cardiovascular Life Support. The ACLS algorithms guide the administration of specific drugs based on the patient's cardiac arrest rhythm, which includes pulseless ventricular tachycardia (VT), ventricular fibrillation (VF), asystole, and pulseless electrical activity (PEA).EpinephrineIndication: Epinephrine is the first-line drug for all cardiac arrest rhythms.Mechanism of Action: Epinephrine...
639
 01:30
Adrenergic Agonists: Therapeutic Uses
1.6K
Adrenergic agonists have diverse therapeutic uses across various medical conditions and emergencies.
Emergency and Intensive Care Unit (ICU) applications: Pressor agents increase blood pressure, heart rate, and contractility in shock and organ failure situations. Dopamine can induce vasodilation and stimulate adrenoceptors. Endogenous catecholamines are effective in treating cardiogenic shock. α2-agonists like clonidine can reverse anesthesia-induced hypertension.
Allergies and...
1.6K
 01:30
Adrenergic Agonists: Direct-Acting Agents
2.6K
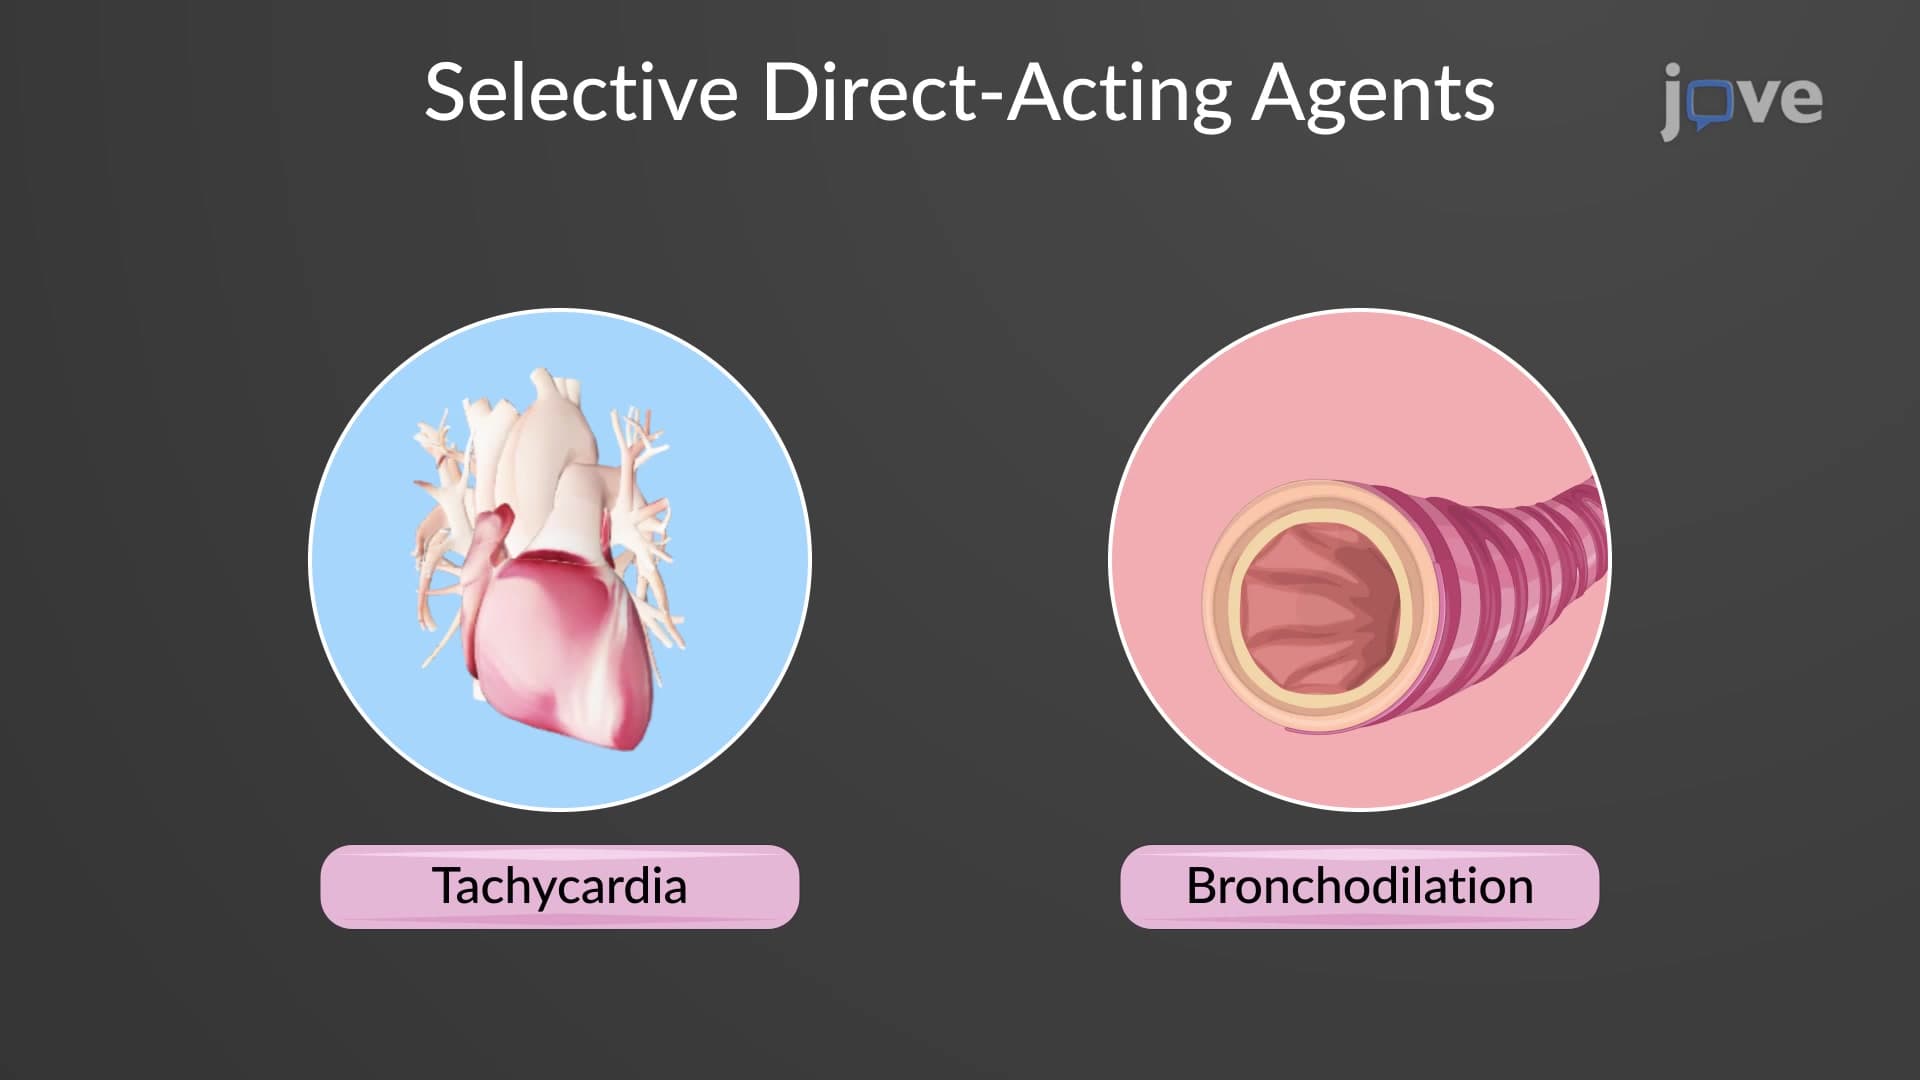
Drugs that mimic the action of endogenous catecholamines like noradrenaline and adrenaline are called adrenergic agonists or sympathomimetics. Based on their mechanism of action, sympathomimetics can be classified as direct-, indirect-, or mixed-acting sympathomimetics. Direct-acting adrenergic agonists activate adrenoceptors without affecting presynaptic neurons, making them independent of neuronal catecholamine-depleting agents like reserpine and guanethidine.
These agents can be classified...
These agents can be classified...
2.6K
 01:31
Adrenergic Receptors: ɑ Subtype
2.7K
Adrenoceptors are classified into α and ꞵ classes based on their potencies to catecholamine agonists. α-adrenoceptors show the following order of catecholamine potency:
Adrenaline ≥ Noradrenaline >> Isoprenaline
α-adrenoceptors are further divided into α1 and α2-adrenoceptors.
α1-Adrenoceptors: These receptors are located postsynaptically on the effector organs and cause constriction of smooth muscle mediated by activation of phospholipase...
Adrenaline ≥ Noradrenaline >> Isoprenaline
α-adrenoceptors are further divided into α1 and α2-adrenoceptors.
α1-Adrenoceptors: These receptors are located postsynaptically on the effector organs and cause constriction of smooth muscle mediated by activation of phospholipase...
2.7K
 01:28
Adrenergic Agonists: Mixed-Action Agents
1.4K
Mixed-action adrenergic agonists, like ephedrine and pseudoephedrine, directly and indirectly affect adrenergic receptors. These agents stimulate adrenoceptors and indirectly release stored neurotransmitters, amplifying the adrenergic response.
Ephedrine and pseudoephedrine lack a catecholamine group, making them less susceptible to degradation by metabolic enzymes. They have increased oral bioavailability and lipophilicity, resulting in a longer duration of action. Their response is reduced by...
Ephedrine and pseudoephedrine lack a catecholamine group, making them less susceptible to degradation by metabolic enzymes. They have increased oral bioavailability and lipophilicity, resulting in a longer duration of action. Their response is reduced by...
1.4K