
由于宫动脉解剖导致的急性缺血性中风的内血管支架:全国性关于中风复发的研究
Huanwen Chen1, Mihir Khunte2,3, Marco Colasurdo4
1Division of Neurointerventional Surgery, Department of Neurosurgery University of Maryland Medical Center Baltimore MD.
Stroke (Hoboken, N.J.)
|January 23, 2026

概括
由于宫动脉剖析 (CAD) 导致的急性缺血性中风 (AIS) 的内血管支架显著减少了180天内中风的复发. 虽然支架增加了内出血风险,但它没有影响短期死亡率或出院结果.
科学领域:
- 神经学 神经学
- 血管外科 血管外科
- 干预心脏病学 干预心脏病学
背景情况:
- 宫动脉解剖 (CAD) 可以导致急性缺血性中风 (AIS).
- 内血管支架用于AIS-CAD中严重的狭窄或闭塞.
- 之前的研究表明,在AIS-CAD中,支架与不支架的结果各不相同,没有关于中风复发的数据.
研究的目的:
- 研究AIS-CAD患者内血管内支架和中风复发之间的关联.
- 评估支架在AIS-CAD的指数住院期间对短期结果的影响.
主要方法:
- 使用2016-2021年全国再录取数据库进行的回顾性队列研究.
- 包括因AIS-CAD住院的成年患者.
- 倾向性得分匹配被用来比较那些接受了支架与那些没有接受支架的患者,控制人口统计,中风严重程度和并发症.
主要成果:
- 支架组 (2244名患者) 与没有支架组 (2215名患者) 相比,在180天内复发性缺血性中风的风险显著降低 (HR 0.50;P=0.034).
- 180天的复发性中风率为1.2%与支架相比3.5%没有 (P=0.017).
- 支架与较高的内出血率 (21.9% vs 19.0%;P=0.027) 有关,但与常规排泄或死亡率的差异无关.
结论:
- 内血管支架与AIS-CAD患者中风复发风险降低有关.
- 尽管增加了内出血的风险,但支架并没有导致更糟糕的短期发病率或死亡率.
- 对于某些患有AIS-CAD的患者来说,支架可能是一个有益的治疗选择,以预防复发性中风.
相关概念视频
 01:27
Regulation of Stroke Volume
4.8K
The regulation of stroke volume, which is the amount of blood the heart pumps out during each heartbeat, is critical for maintaining a healthy circulatory system. Stroke volume is influenced by three main factors: preload, contractility, and afterload.
Preload refers to the degree of stretch on the heart before it contracts. It's analogous to the stretching of a rubber band; the more it's stretched, the more forcefully it snaps back. This concept is encapsulated in the Frank-Starling law of the...
Preload refers to the degree of stretch on the heart before it contracts. It's analogous to the stretching of a rubber band; the more it's stretched, the more forcefully it snaps back. This concept is encapsulated in the Frank-Starling law of the...
4.8K
 01:11
Cardiac Output and Stroke Volume
4.5K
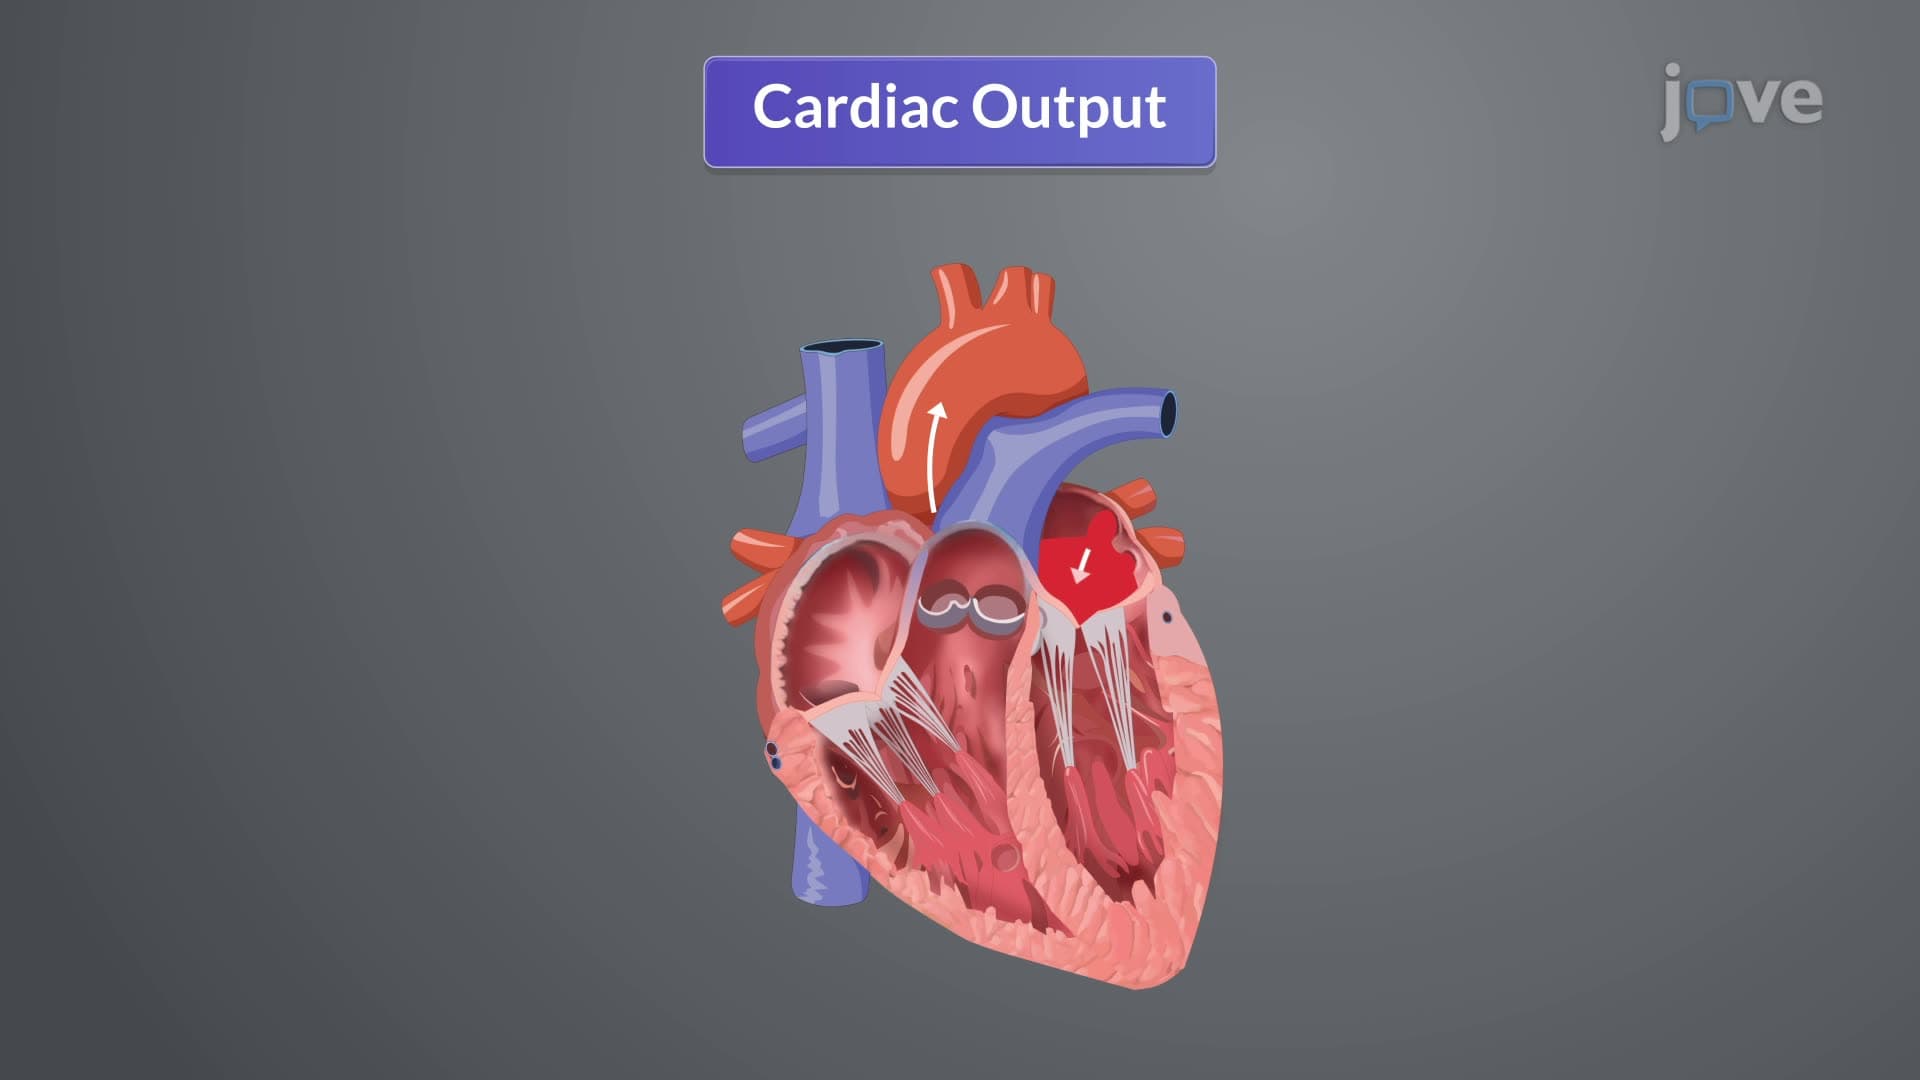
Cardiac output (CO) is an integral aspect of human physiology, reflecting the heart's efficiency and responsiveness to the body's needs. It represents the volume of blood that the left or right ventricle ejects into the aorta or pulmonary trunk each minute. The CO is calculated by multiplying the heart rate (HR)—the number of heartbeats per minute—by the stroke volume (SV)—the amount of blood pumped out with each heartbeat.
In an average resting adult male, the typical cardiac...
In an average resting adult male, the typical cardiac...
4.5K
 01:22
Cardiac Output II: Effect of Stroke Volume on Cardiac Output
3.2K
Cardiac output (CO), the amount of blood the heart pumps per minute, is a parameter in cardiovascular physiology determined by stroke volume and heart rate. Stroke volume, the amount of blood pushed from one of the ventricles per heartbeat, is influenced by preload, afterload, and contractility.
Preload
Preload refers to the initial elongation of the cardiac myocytes before contraction and is related to the volume of blood filling the heart at the end of diastole, or end-diastolic volume. The...
Preload
Preload refers to the initial elongation of the cardiac myocytes before contraction and is related to the volume of blood filling the heart at the end of diastole, or end-diastolic volume. The...
3.2K
 01:28
Acute Pyelonephritis II: Diagnostic Studies and Management
362
Introduction:For diagnosing acute pyelonephritis, a comprehensive patient history is collected to identify symptoms such as dysuria, frequent or urgent urination, flank pain, or costovertebral angle (CVA) tenderness that may suggest a kidney infection.Physical ExaminationDuring the physical examination, CVA tenderness is assessed. This involves gentle percussion over the costovertebral angle, where tenderness often indicates a kidney infection.Diagnostic TestsUrinalysis: Used to identify white...
362
 01:30
Acute Coronary Syndrome III: Diagnostic Studies
229
Diagnosing acute coronary syndrome or ACS begins with a thorough patient history. Notable symptoms include central, crushing chest pain radiating to the left arm, neck, jaw, or back, along with shortness of breath, sweating (diaphoresis), nausea, vomiting, dizziness, and palpitations.It is crucial to note any history of cardiac illnesses and assess risk factors, including age, gender, smoking, hypertension, diabetes, hyperlipidemia, and a sedentary lifestyle.During physical examination, vital...
229
 01:30
Acute Kidney Injury IV: Diagnostic Studies and Prevention
281
Accurate diagnosis and effective prevention are critical in managing Acute Kidney Injury (AKI), which is linked to high mortality rates ranging from 10% to 80%. Timely recognition of at-risk patients and careful monitoring can significantly reduce the likelihood of kidney damage.Diagnostic Assessments:The diagnostic process starts with a comprehensive medical history to identify prerenal, intrarenal, and postrenal causes.Prerenal causes, such as dehydration, hypotension, or blood loss, should...
281