
血清过氧化1的升高是ARDS多器官衰竭的生物标志物
Guoliang Jiang1,2, Yan Zhang2,3, Hanwei Huang2,4
1Department of Respiratory and Critical Care Medicine, Third Xiangya Hospital of Central South University, Changsha, Hunan, China.
BMJ open respiratory research
|February 19, 2026

概括
血清PRDX1显示为预测急性呼吸困扰综合征 (ARDS) 死亡率的生物标志物具有前景. 升高的水平与疾病严重程度和患者的结果相关,有助于临床管理.
科学领域:
- 生物化学 生物化学
- 临床医学 临床医学
- 肺部病理学 肺部病理学
背景情况:
- 急性呼吸困难综合征 (ARDS) 具有显著的死亡率,并且缺乏确定患者分层的生物标志物.
- 目前对ARDS病理生理学的理解还没有为疾病管理提供有效的工具.
- 这项研究调查了循环PRDX1作为ARDS的预后指标的潜力.
研究的目的:
- 评估血清PRDX1在ARDS患者中的诊断和预后效用.
- 确定PRDX1水平与ARDS28天死亡率之间的相关性.
- 评估PRDX1作为ARDS分层和管理的生物标志物的潜力.
主要方法:
- 90名ARDS患者的回顾性队列研究,将血清PRDX1水平与健康和非ARDS肺炎对照进行比较.
- 多变量逻辑回归和ROC曲线分析,以评估PRDX1对28天死亡率的预后值.
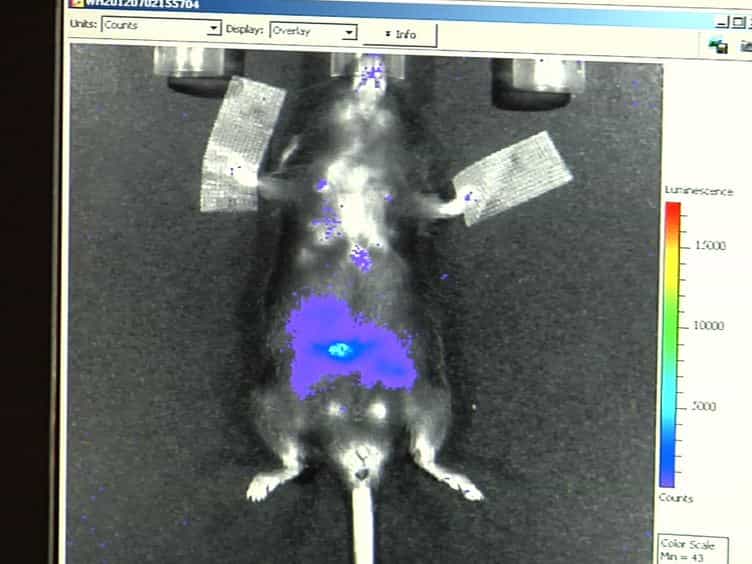
- 在独立的队列中验证和在急性肺损伤的小鼠模型中评估.
主要成果:
- 在ARDS患者中,血清PRDX1水平显著升高,特别是在多器官损伤患者中.
- 确定PRDX1和年龄是ARDS28天死亡率的独立风险因素.
- 在动物模型中,PRDX1表现出显著的预后效用 (AUC=0.776),与APACHE II得分相当,与动物模型中的肺损伤严重程度相关.
结论:
- 循环中的PRDX1在ARDS中升高,特别是在多器官损伤时,并作为潜在的预后生物标志物.
- PRDX1水平与28天死亡率相关,为患者的治疗结果提供了宝贵的见解.
- 将PRDX1集成到ARDS管理框架中可能会增强临床决策并改善患者的治疗结果.
关键词:
在ARDS中,我们使用ARDS.
相关概念视频
 01:23
Acute Respiratory Failure-IV
600
Respiratory failure can manifest suddenly or gradually, characterized by a rapid decline in PaO2 and a rapid rise in PaCO2. This situation indicates a severe respiratory problem that may quickly become a life-threatening emergency. One of the early signs of hypoxemic Acute Respiratory Failure (ARF) is a change in mental status due to the brain's sensitivity to oxygen levels and changes in acid-base balance. Symptoms such as restlessness, confusion, and agitation suggest inadequate oxygen...
600
 01:21
Acute Respiratory Failure-II
1.2K
Type I Respiratory Failure, or hypoxemic respiratory failure, occurs when the partial pressure of oxygen (PaO2) in arterial blood falls below 60 mmHg while breathing room air without a corresponding increase in arterial carbon dioxide levels (PaCO2). This condition highlights a significant impairment in the lungs' capacity to oxygenate the blood.
The underlying physiological abnormalities that contribute to hypoxemic respiratory failure include:
The underlying physiological abnormalities that contribute to hypoxemic respiratory failure include:
1.2K