

概括
短暂的α-上腺刺激会收缩冠状动脉血管,而持续的刺激则不会,这表明冠状动脉循环可以适应. 过度 perfused 心肌能耐受持续的刺激,而不会影响氧化.
科学领域:
- 心血管生理学心血管生理学
- 药理学 药理学是指药理学的学科.
背景情况:
- 阿尔法上腺刺激会影响冠状动脉循环.
- 了解其在不同服用时间的效果至关重要.
研究的目的:
- 为了比较短暂的 (球体) 与持续 (输注) 的α-上腺素刺激对冠状动脉循环的影响.
- 研究冠状动脉循环适应持续血管收缩刺激的能力.
主要方法:
- 醒着的猪被用来研究冠状动脉血流.
- 烯通过玻尿酸注射或15分钟的输液进入左前垂下冠状动脉 (LAD).
- 用放射性微球技术测量心肌动脉血流量,比较LAD和左环冠状动脉 (LCF) 区域.
主要成果:
- 烯玻尿酸剂显著降低了LAD/LCF流量比,表明血管收缩.
- 在正常情况下,持续输注烯并没有改变LAD/LCF比率.
- 在过度 perfusion 的条件下 (腺素预处理),持续的烯输注显著降低了 LAD/LCF 的比率,揭示了血管收缩.
结论:
- 短暂的α-上腺刺激可以覆盖正常的调节机制,导致冠状动脉阻力血管收缩.
- 持续的α-上腺刺激不会导致冠状动脉流量的显著变化,这表明冠状动脉循环中的适应机制.
- 冠状动脉循环可以抵消慢性血管收缩效应,过度注的心肌可以耐受持续的α-上腺刺激而不会影响氧化.


相关概念视频
 01:27
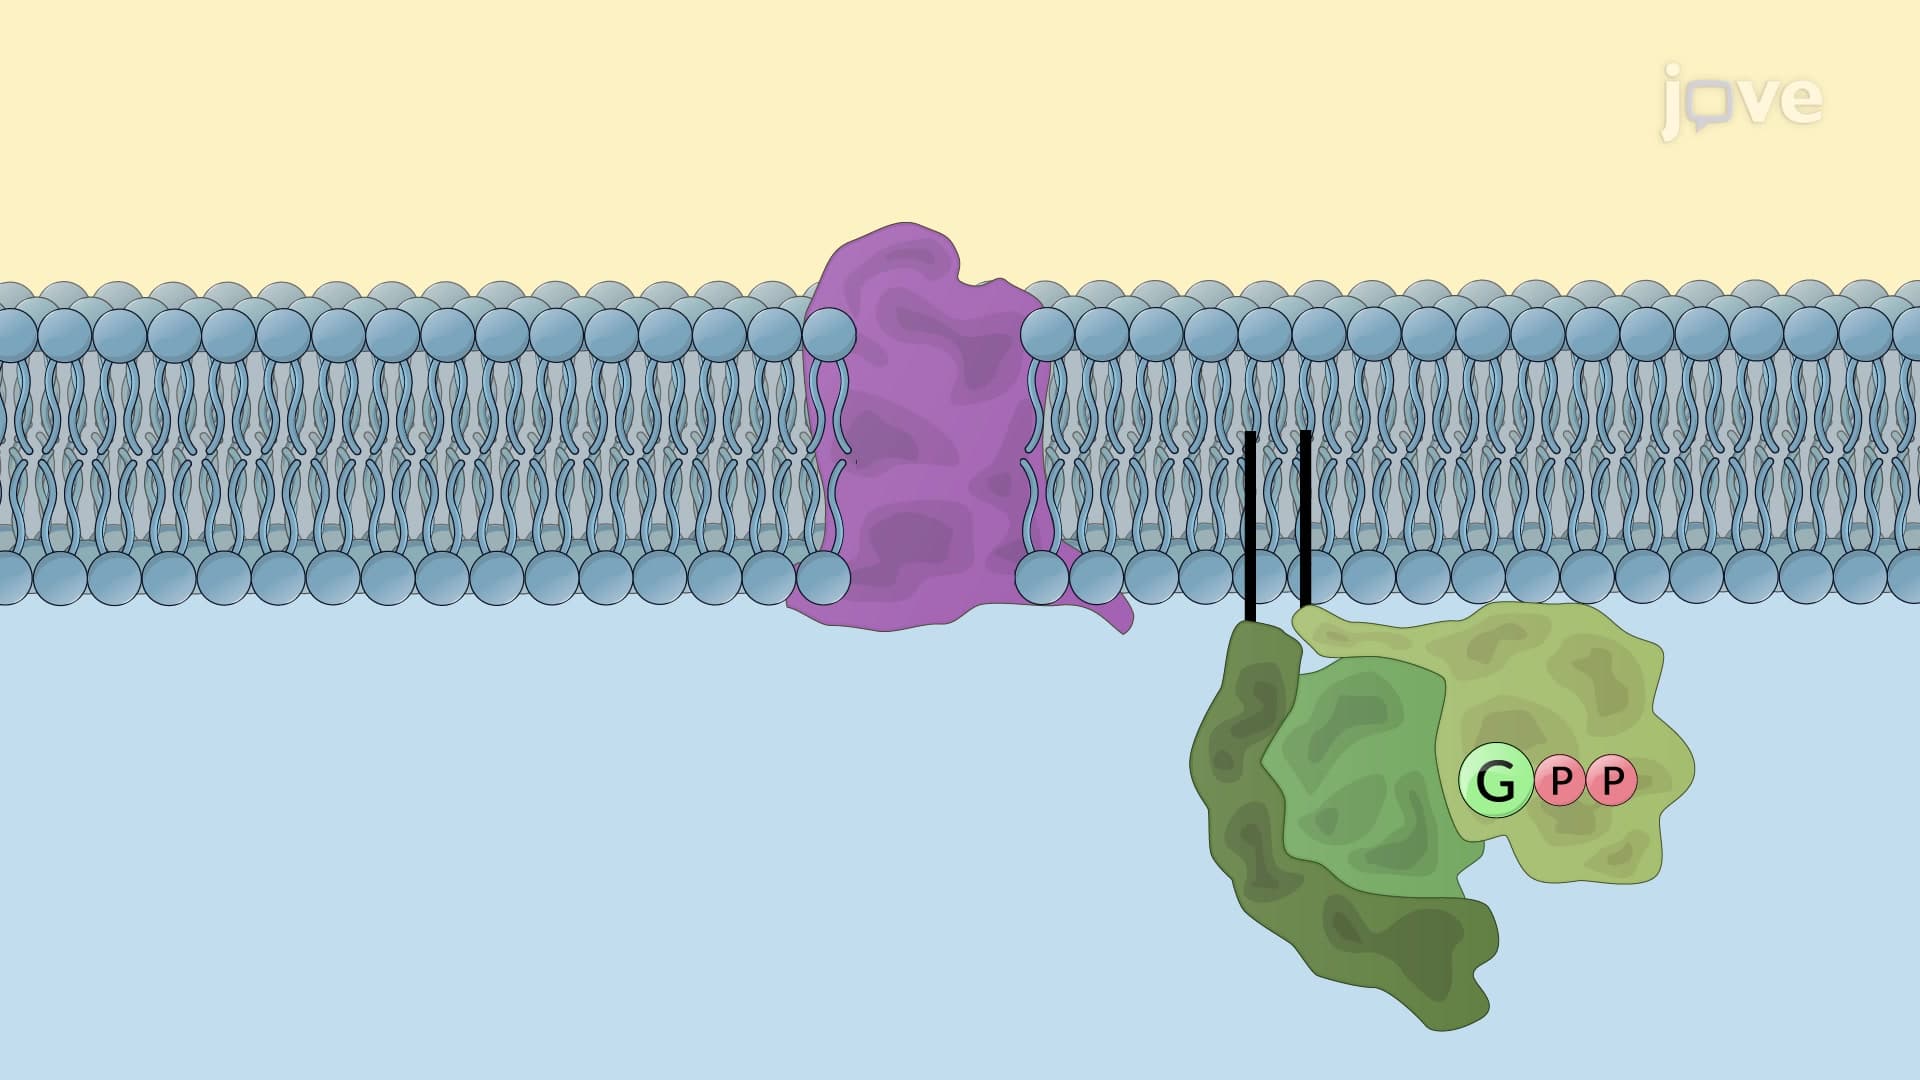
Adrenergic Receptors (Adrenoceptors): Classification
Adrenergic receptors, or adrenoceptors, respond to the autonomic neurotransmitter noradrenaline and other endogenous catecholamine agonists. They are classified into two main families, α and β, based on their pharmacological response and are further subdivided depending on their location, elicited response, and affinity to specific agonists or antagonists.
α-Adrenoceptors
α-Adrenoceptors are classified into two main subtypes: α1 and α2. The α1 adrenoceptors, which are found on postsynaptic...
α-Adrenoceptors
α-Adrenoceptors are classified into two main subtypes: α1 and α2. The α1 adrenoceptors, which are found on postsynaptic...
 01:31
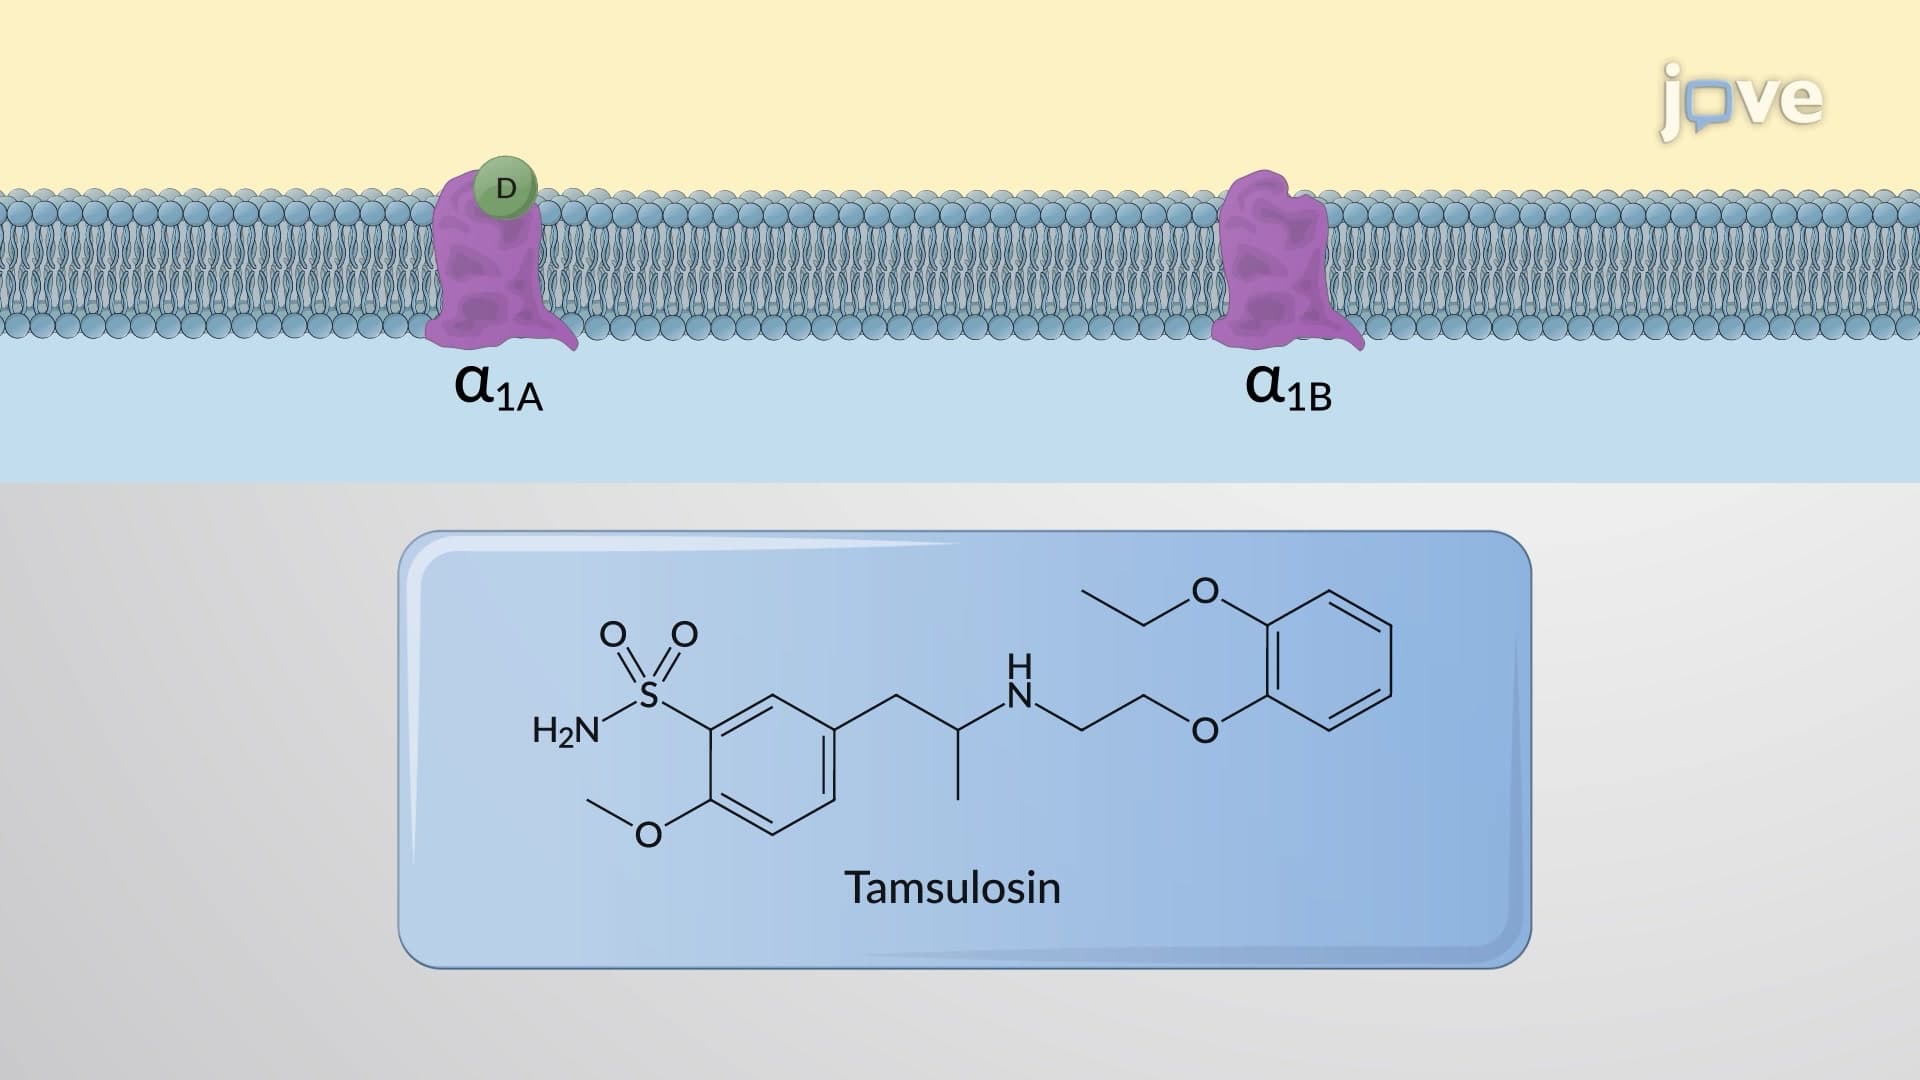
Adrenergic Receptors: ɑ Subtype
Adrenoceptors are classified into α and ꞵ classes based on their potencies to catecholamine agonists. α-adrenoceptors show the following order of catecholamine potency:
Adrenaline ≥ Noradrenaline >> Isoprenaline
α-adrenoceptors are further divided into α1 and α2-adrenoceptors.
α1-Adrenoceptors: These receptors are located postsynaptically on the effector organs and cause constriction of smooth muscle mediated by activation of phospholipase C—inositol-1,4,5-trisphosphate...
Adrenaline ≥ Noradrenaline >> Isoprenaline
α-adrenoceptors are further divided into α1 and α2-adrenoceptors.
α1-Adrenoceptors: These receptors are located postsynaptically on the effector organs and cause constriction of smooth muscle mediated by activation of phospholipase C—inositol-1,4,5-trisphosphate...
 01:26
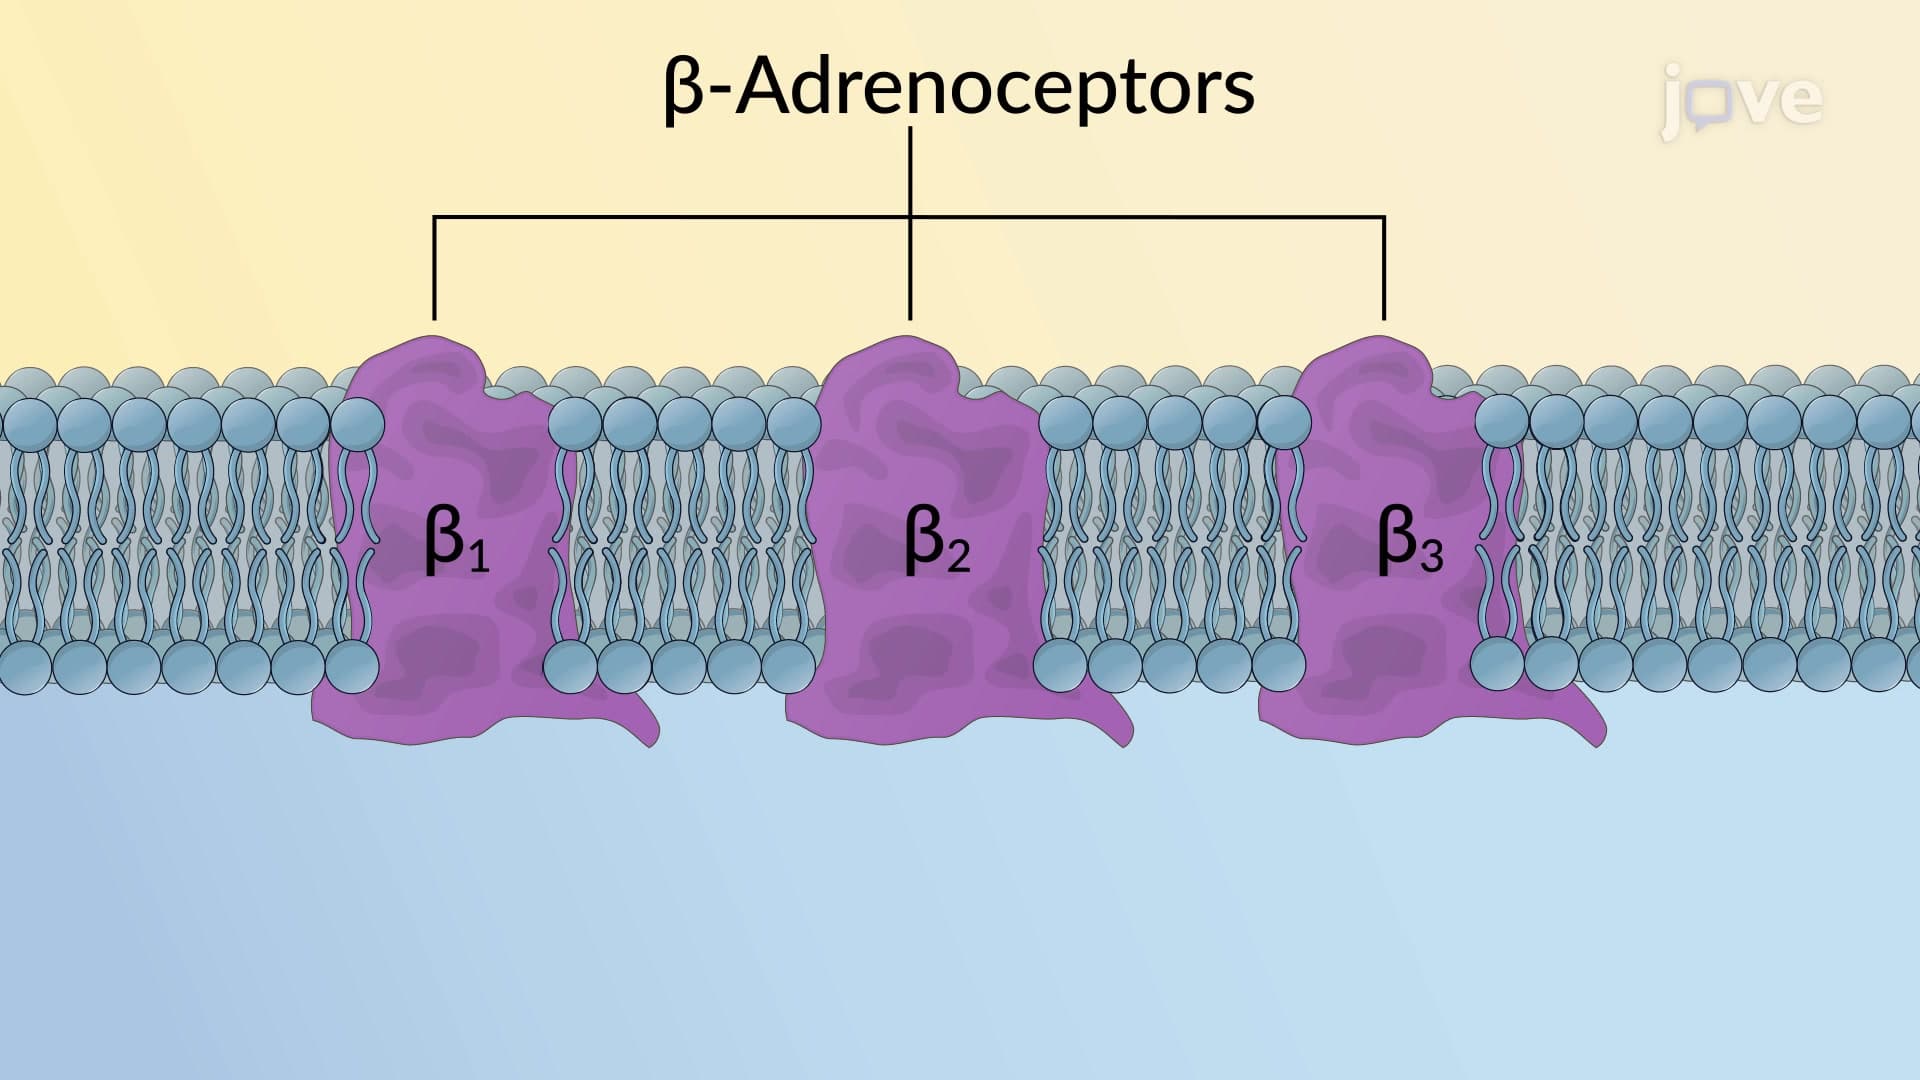
Adrenergic Receptors: β Subtype
β-adrenoceptors have varied sensitivities towards adrenaline, noradrenaline, and isoprenaline. The order of agonist potency is as follows:
Isoprenaline > Adrenaline > Noradrenaline
Neurotransmitter binding to these receptors causes activation of adenylyl cyclase resulting in increased concentrations of cAMP and modulation of calcium ion channels within the cell. They are further classified into β1, β2, and β3 subtypes.
β1-adrenoceptors: β1-adrenoceptors have equal affinities for...
Isoprenaline > Adrenaline > Noradrenaline
Neurotransmitter binding to these receptors causes activation of adenylyl cyclase resulting in increased concentrations of cAMP and modulation of calcium ion channels within the cell. They are further classified into β1, β2, and β3 subtypes.
β1-adrenoceptors: β1-adrenoceptors have equal affinities for...
 01:30
Adrenergic Agonists: Direct-Acting Agents
Drugs that mimic the action of endogenous catecholamines like noradrenaline and adrenaline are called adrenergic agonists or sympathomimetics. Based on their mechanism of action, sympathomimetics can be classified as direct-, indirect-, or mixed-acting sympathomimetics. Direct-acting adrenergic agonists activate adrenoceptors without affecting presynaptic neurons, making them independent of neuronal catecholamine-depleting agents like reserpine and guanethidine.
These agents can be classified...
These agents can be classified...
 01:29
Pathophysiology of Cardiac Performance
Typical heart performance is influenced by heart rate, rhythm, myocardial contraction, and metabolism or blood flow. The cardiac muscle exhibits distinct electrophysiological features, including pacemaker activity and calcium channel control, which play a vital role in the heart's response to various drugs. The autonomic nervous system, comprising the sympathetic and parasympathetic branches, regulates heart rate. Sympathetic activation increases heart rate, while parasympathetic activation...
 01:19
Acute Coronary Syndrome II: Pathophysiology and Clinical Manifestations
The pathophysiology of Acute Coronary Syndrome [ACD] involves several key processes:The main underlying cause of ACD is atherosclerosis, a chronic inflammatory disease characterized by the buildup of lipid-laden plaques within the coronary arteries.As the atherosclerotic plaque grows in the coronary artery, it may become unstable due to the formation of a lipid-rich core and a thin fibrous cap. Inflammatory cells within the plaque, such as macrophages, secrete enzymes that degrade the...