Related Experiment Video
Updated: Oct 24, 2026

International Expert Consensus and Recommendations for Neonatal Pneumothorax Ultrasound Diagnosis and Ultrasound-guided Thoracentesis Procedure
Published on: March 12, 2020
The use of pleuroperitoneal shunts in the management of persistent chylothorax in infants
S A Engum1, F J Rescorla, K W West
1Department of Surgery, Indiana University School of Medicine and the James Whitcomb Riley Hospital for Children, Indianapolis 46202, USA.

Insights
Pleuroperitoneal shunting effectively treats infant chylothorax when other methods fail. This safe and simple procedure resolves symptoms, offering a viable option for complex cases.
Area of Science:
- Pediatric Surgery
- Thoracic Surgery
- Neonatal Care
Background:
- Chylothorax in infants presents significant respiratory, nutritional, and immunologic challenges.
- Medical management of chylothorax often has a high failure rate, necessitating alternative treatments.
- Surgical intervention is increasingly recognized as a primary treatment for complicated chylothorax.
Purpose of the Study:
- To evaluate the safety and efficacy of pleuroperitoneal shunting in managing refractory chylothorax in infants.
- To assess outcomes and complications associated with pleuroperitoneal shunt placement in a neonatal population.
Main Methods:
- Seven infants with refractory chylothorax underwent pleuroperitoneal shunt placement using a Denver double-valved system.
- Patients included neonates with congenital or acquired etiologies, many ventilator-dependent.
- Shunt implantation was performed under general anesthesia, with manual pumping required postoperatively.
Main Results:
- All seven patients experienced elimination of chylothorax and symptom resolution.
- Shunt survival rate was 86% (6/7), with a patient survival rate of 71% (5/7).
- Complications included two cases, with deaths attributed to progressive pulmonary disease and viral sepsis.
Conclusions:
- Pleuroperitoneal shunting is a safe, simple, and effective treatment for infant chylothorax.
- The procedure is suitable for infants of varying sizes, ages, and degrees of prematurity.
- Shunting offers a valuable therapeutic option for complex and refractory cases of neonatal chylothorax.
Background/Purpose:
The development of chylothorax is a serious and often life-threatening clinical entity that may cause profound respiratory, nutritional, and immunologic complications and has become increasingly common in recent years. Optimal management of this problem has not been well defined because medical therapy has a significant failure rate. Surgical treatment of complicated chylothorax has become a mainstay of care.
Methods:
Over the last 36 months, seven infants had a pleuroperitoneal shunt placed for the management of refractory chylothorax. Ages ranged from 10 to 66 days with a weight between 1,000 to 4,850 g. Five of the seven infants were ventilator dependent. The etiologies were congenital in four and acquired in three with one related to a cardiothoracic procedure, one related to superior vena caval thrombosis, and one postoperative diaphragmatic hernia repair with superior vena caval thrombosis. Associated conditions included a left congenital diaphragmatic hernia, asplenia, isolated renal agenesis, bronchopulmonary dysplasia, and a patent ductus arteriosus. Each patient was unresponsive to thoracentesis, tube thoracostomy, and dietary manipulation with preoperative volume of chest tube output ranging from 50 to 162 cc/kg/d. The duration of preoperative therapy in congenital occurrences ranged from 10 to 46 days (average, 22 days). A Denver double-valved shunt system was used and catheters were implanted under general anesthesia. Manual pumping was required postoperatively on an hourly basis.
Results:
All seven patients had excellent results with the elimination of the chylothorax and resolution of symptoms. There were two complications. Shunt survival rate was six of seven (86%). Shunt removal ranged from 24 to 79 days (average, 44 days). Patient survival rate was five of seven (71%) with one infant dying of progressive pulmonary disease and one infant dying from viral sepsis; both had functioning shunts. One patient remains ventilator dependent secondary to chronic lung disease from prematurity.
Conclusions:
Pleuroperitoneal shunting is safe, simple, and an effective treatment of chylothorax in infants despite their size, age, or degree of prematurity.
Related Concept Videos
 01:27
Pneumothorax-II
Clinical Manifestations:
 01:26
Endoscopic Studies II: Thoracocentesis
Description
Excess pleural fluid or air may accumulate in some respiratory disorders in the thoracic cavity. To treat pleural effusion, a physician conducts thoracentesis by carefully piercing the chest wall and entering...
 01:28
Pleural Effusion II: Symptoms and Management
A pleural effusion is the abnormal collection of fluid between the parietal and visceral pleura layers of tissue that form the lining of the lungs and chest cavity. It can occur independently or due to surrounding parenchymal diseases, such as infection, malignancy, or inflammatory conditions.
Clinical Manifestations:
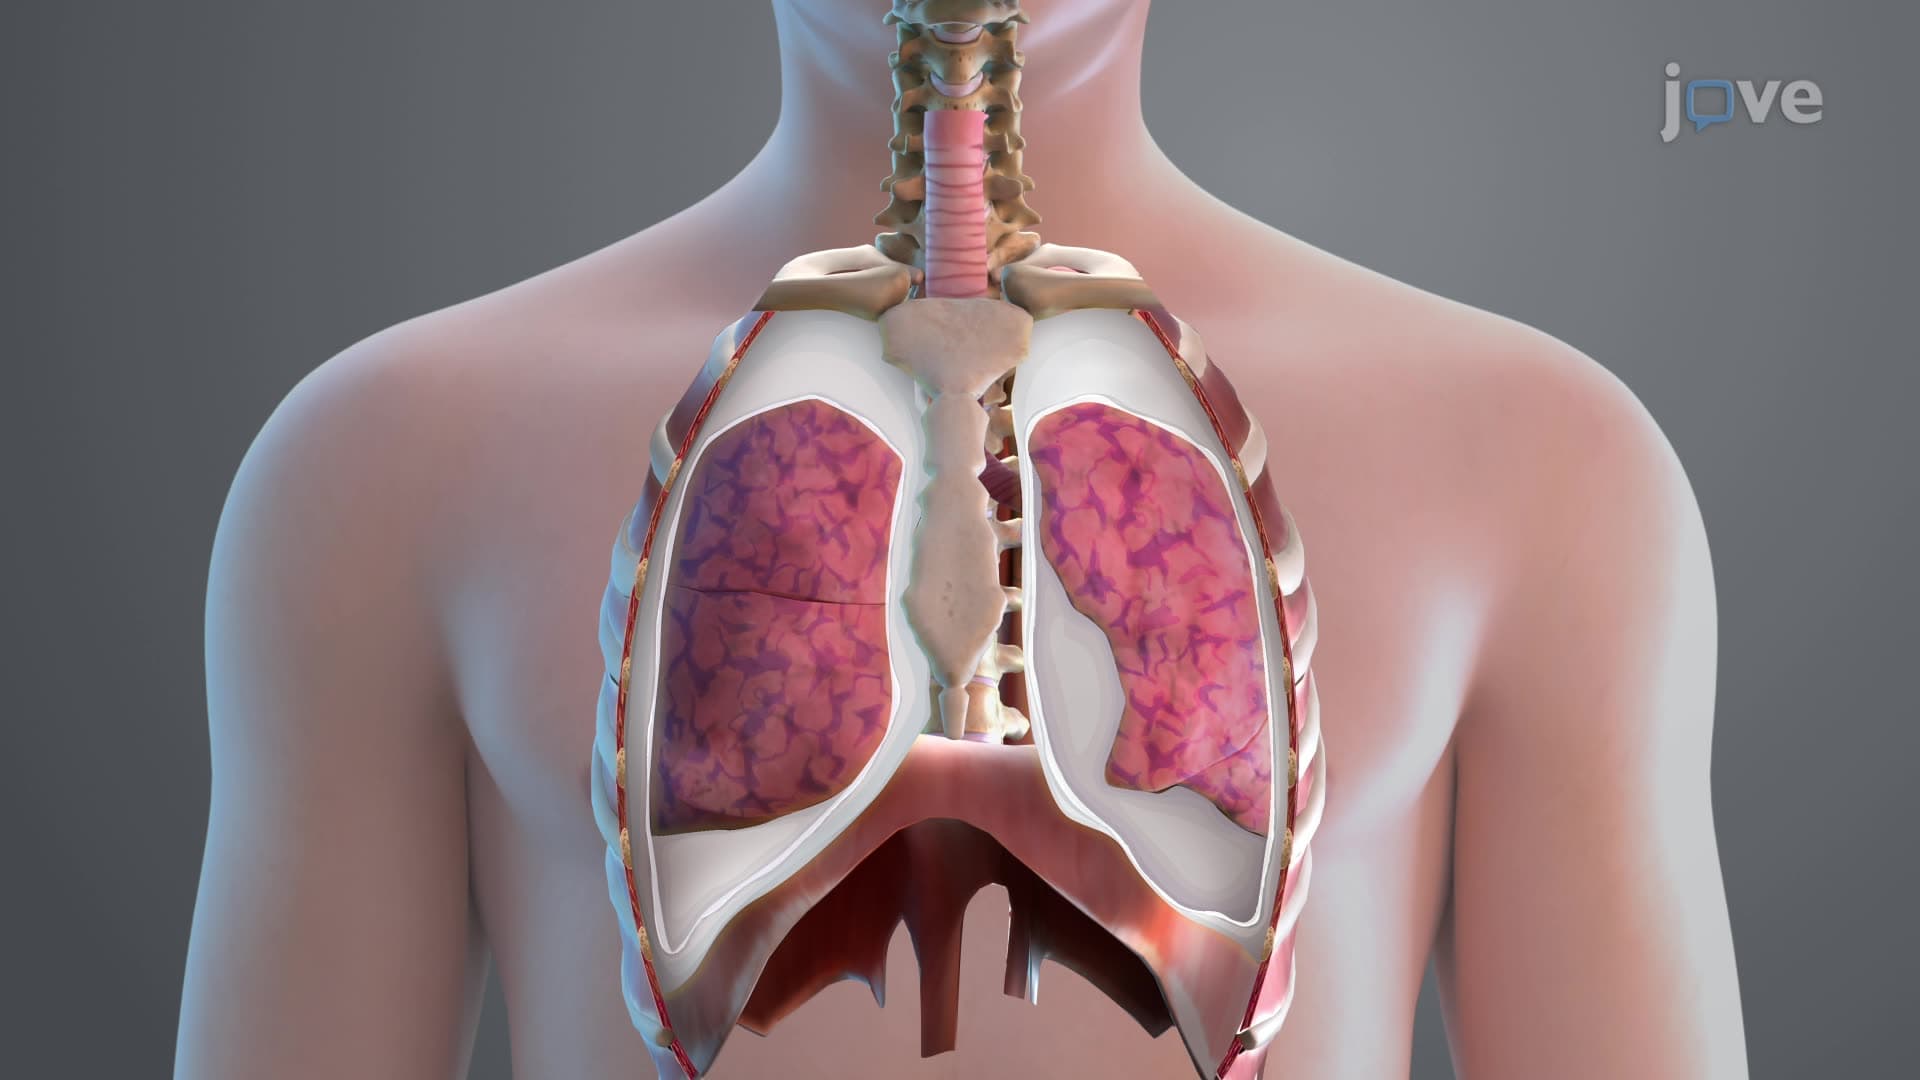 01:13
Pleura of the Lungs