[Monosymptomatic hyperthyroidism and TSH-producing adenoma: successful therapy with octreotide]
Related Experiment Video
Updated: Oct 24, 2026

An Orthotopic Mouse Model of Anaplastic Thyroid Carcinoma
Published on: April 17, 2013
B Mayinger1, D Axelos, M Pavel
1Medizinische Klinik I mit Poliklinik, Friedrich-Alexander-Universität, Erlangen-Nürnberg.

History And Findings:
Magnetic resonance imaging (MRI) of the central nervous system was performed on a 72-year-old woman who was hyperthyroid without suppression of the thyroid-stimulating hormone (TSH) and had complained of a recent onset of headaches. MRI demonstrated a space-occupying lesion, 1 cm in diameter, in the anterior pituitary. The clinical symptoms were marked by a long-standing monosymptomatic illness of rapidly changing mood swings with depressive and manic phases.
Investigations:
Endocrinological-biochemical tests showed hyperthyroidism (fT3 10.55 pmol/l and fT4 39 pmol/l) but no TSH suppression (TSH: 2.9 microU/ml). Octreotide scintigraphy documented an activity-rich area in the anterior pituitary and the upper anterior mediastinum. Mediastinal MRI revealed a 5 cm space-occupying mass lying on the right atrium. 131I scintigraphy identified the mass as a retrosternal goitre.
Treatment And Course:
As an operation on the anterior pituitary would have carried a high risk for the patient who was in a poor general condition and she had refused to be operated, treatment with octreotide, a long-acting somatostatin analogue, was initiated. This achieved a euthyroid state with partly suppressed TSH, and the patient's emotional swings ceased.
Conclusion:
If hyperthyroidism coexists with non-suppressed TSH levels, a TSH-producing hypophyseal adenoma should be considered in the differential diagnosis despite its rarity. Octreotide administration is an effective and safe treatment and is the method of choice, especially when there are contraindications to surgical resection of the anterior pituitary.

Related Concept Videos
 01:27
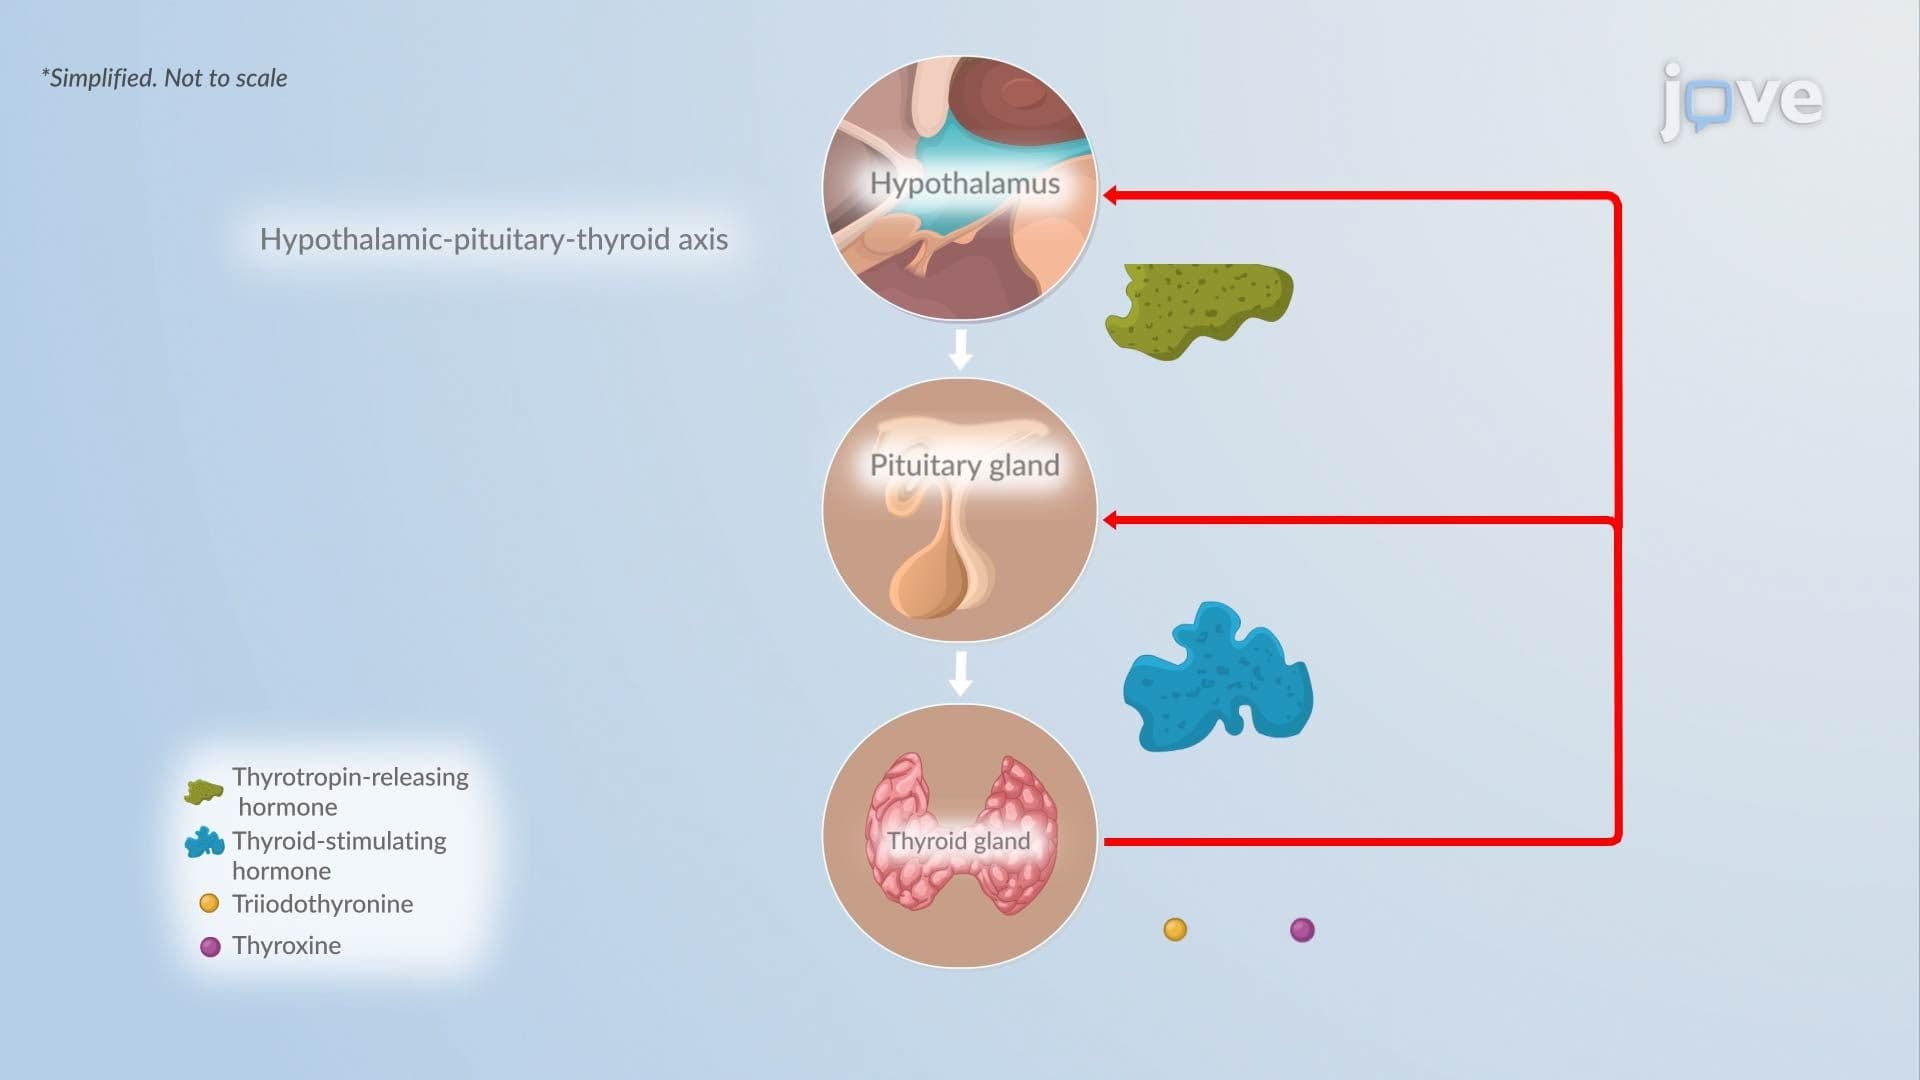
Hyperthyroidism II: Pathophysiology
 01:25
Hyperthyroidism I: Introduction
 01:24
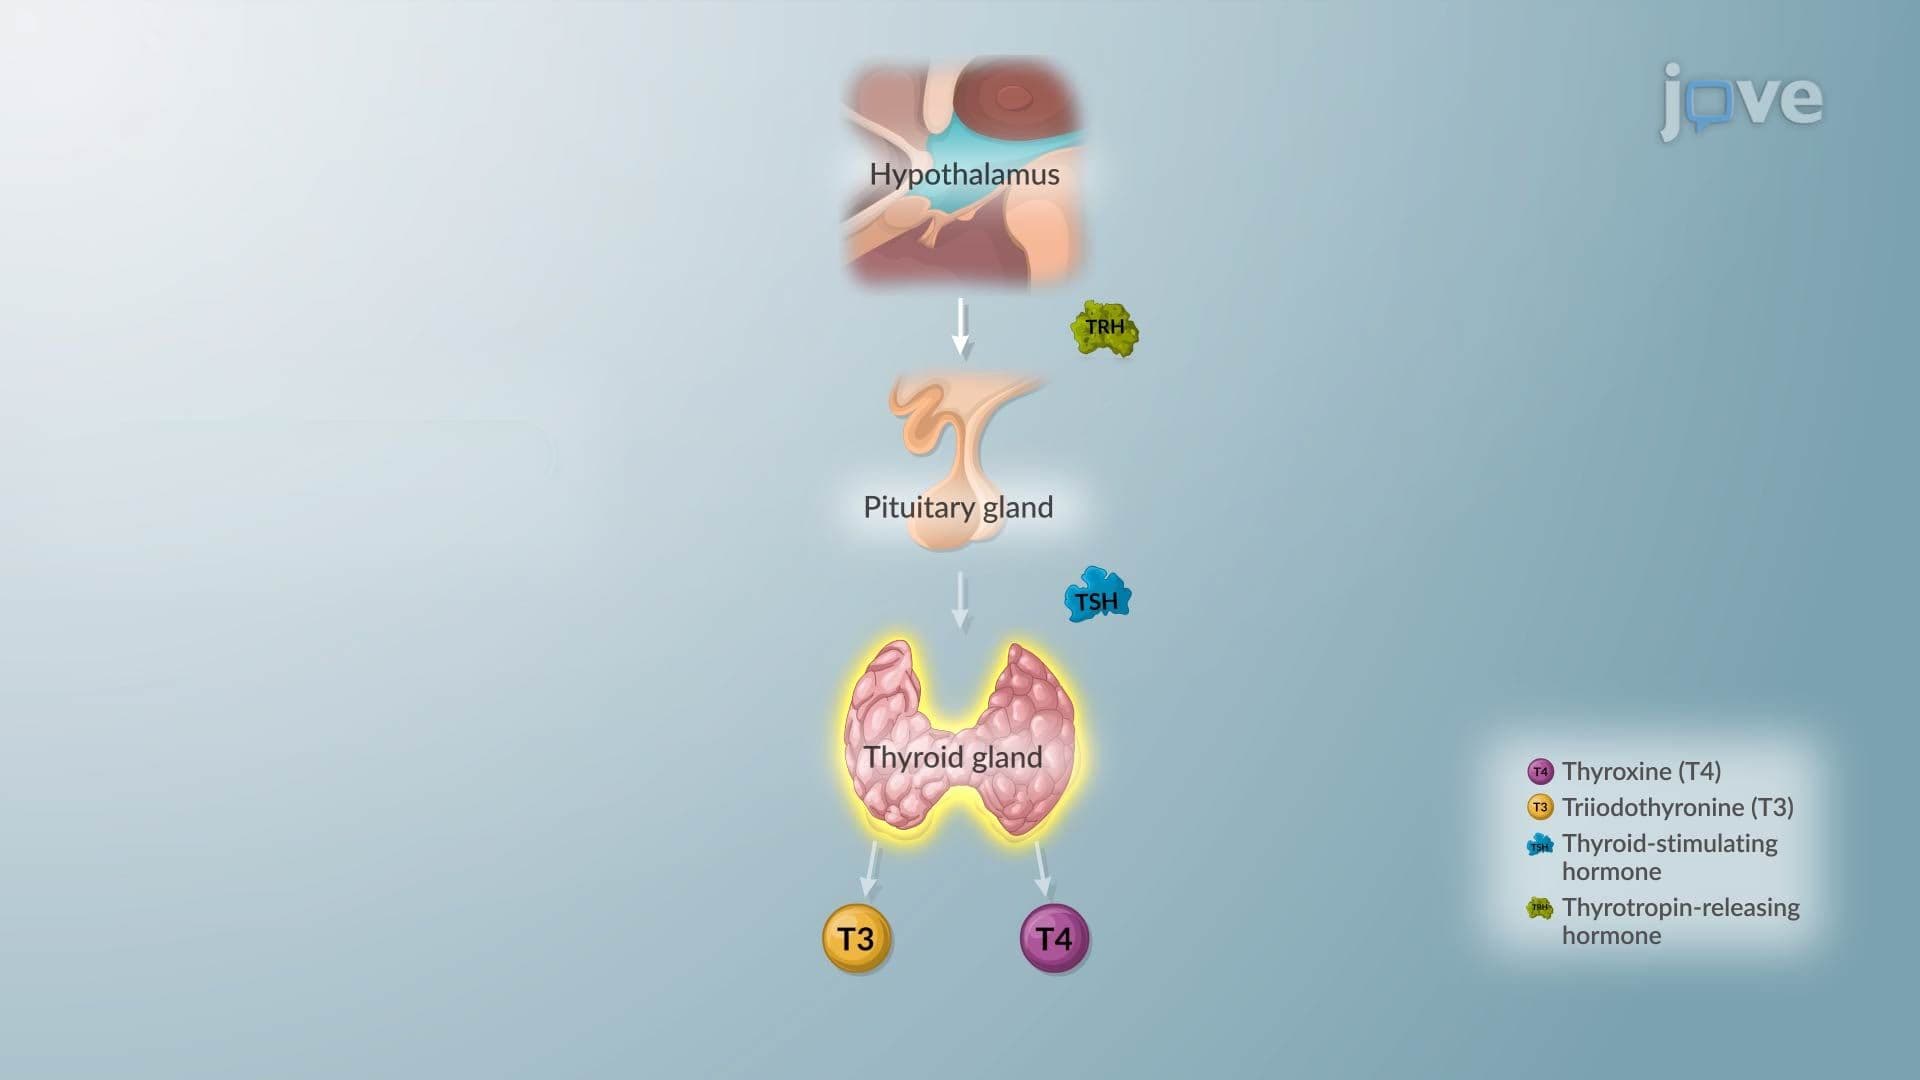
Graves Disease II: Pathophysiology
 01:23
Hypothyroidism II: Pathophysiology
 01:27
Goiter
 01:28
Graves' Disease I: Introduction