Related Experiment Video
Updated: Sep 10, 2026


The Perinatal Asphyxiated Lamb Model: A Model for Newborn Resuscitation
Published on: August 15, 2018
The outcome after perinatal management of infants with potential airway obstruction
E Raveh1, B C Papsin, D Farine
1The Department of Otolaryngology The Hospital for Sick Children, Toronto Ontario, Canada.

Masses in the head and neck are being detected prenatally with increasing frequency, necessitating the need for management of potential upper airway obstruction at delivery. Establishment of the airway at delivery and its maintenance thereafter are critical. This should optimally be performed with the baby still attached to the placental circulation. The importance of multidisciplinary team management, including a high risk obstetrician, neonatologist, pediatric otolaryngologist, pediatric thoracic surgeon, and an anesthetist, cannot be overemphasized. Endotracheal intubation is attempted first, if unsuccessful then is followed by insertion of a rigid bronchoscope. Tracheotomy should be reserved for airway obstructions, which are not amenable to endotracheal intubation or in babies in whom exchange from a bronchoscope to endotracheal tube cannot be safely performed. The management of six infants with prenatally diagnosed potential airway obstruction is presented. Morbidity and mortality still ultimately depend on the severity of the existent anomalies.
Masses in the head and neck are being detected prenatally with increasing frequency, necessitating the need for management of potential upper airway obstruction at delivery. Establishment of the airway at delivery and its maintenance thereafter are critical. This should optimally be performed with the baby still attached to the placental circulation. The importance of multidisciplinary team management, including a high risk obstetrician, neonatologist, pediatric otolaryngologist, pediatric thoracic surgeon, and an anesthetist, cannot be overemphasized. Endotracheal intubation is attempted first, if unsuccessful then is followed by insertion of a rigid bronchoscope. Tracheotomy should be reserved for airway obstructions, which are not amenable to endotracheal intubation or in babies in whom exchange from a bronchoscope to endotracheal tube cannot be safely performed. The management of six infants with prenatally diagnosed potential airway obstruction is presented. Morbidity and mortality still ultimately depend on the severity of the existent anomalies.
More Related Videos
 05:50
International Expert Consensus and Recommendations for Neonatal Pneumothorax Ultrasound Diagnosis and Ultrasound-guided Thoracentesis Procedure
Published on: March 12, 2020
 04:56
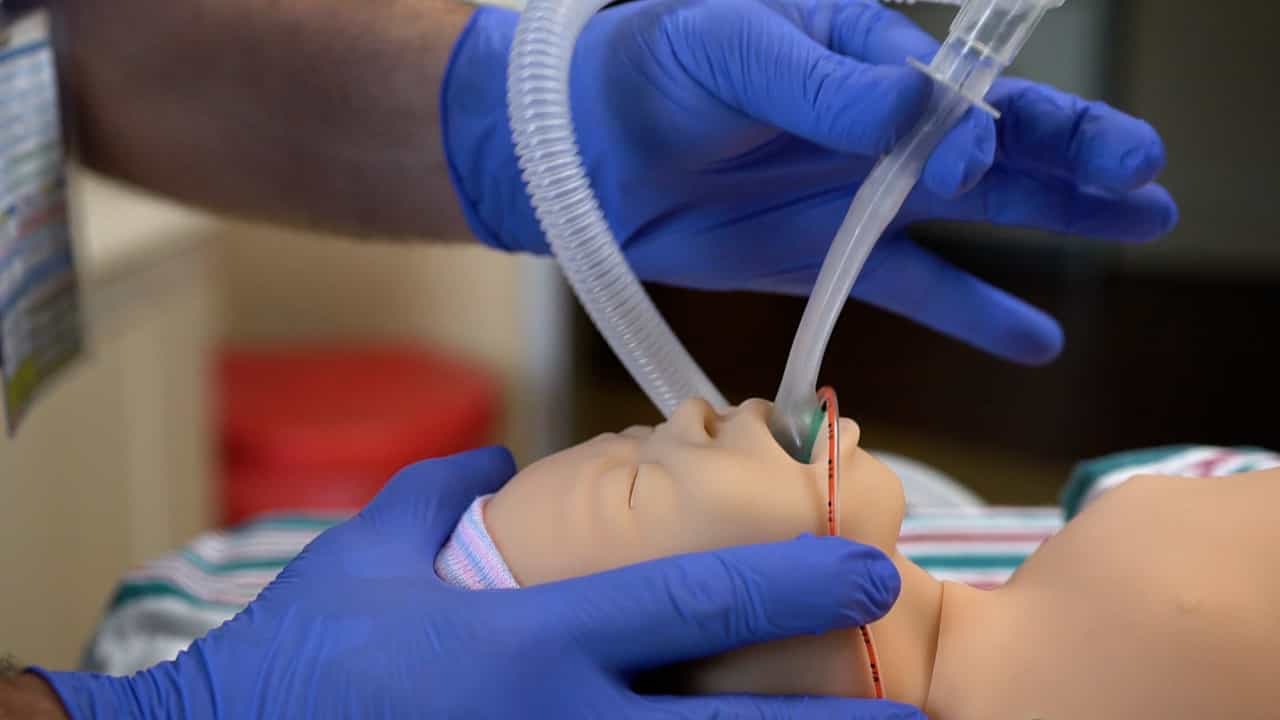
Laryngeal Mask Airway (LMA) Placement in a Neonatal Patient Simulator Using a Non-Inflatable Supraglottic Airway (SGA)
Published on: July 14, 2023
Related Concept Videos
 01:30
Assessment of Airway, Skin Color, and Use of Accessory Muscles
Introduction
The initial evaluation of a patient's respiratory system...
 01:15
Endotracheal Intubation I: Procedure
The ET tube comprises various components, including a standard adaptor to attach a bag-valve-mask (BVM) or ventilator, a cuff, a pilot balloon, and radiopaque markings along its length to measure the insertion distance. The tube sizes...
 01:17
Endotracheal Intubation II: Nursing Management
1. Nursing Care of Patients Before Intubation
Before the endotracheal intubation procedure, nurses play an essential role in ensuring the process goes smoothly. The nurses must be familiar with intubation...
 01:24
Endotracheal Tube Extubation
Procedure
Extubation removes the endotracheal tube (ETT) from the patient on mechanical ventilation. It requires a well-coordinated, multidisciplinary approach involving physicians, nurses, respiratory therapists, and other healthcare professionals.
 01:22
Cardiopulmonary Resuscitation II: ACLS Airway Management
 01:30
Cardiopulmonary Resuscitation V: Advanced Airway Management Techniques