Related Experiment Video
Updated: Sep 12, 2026
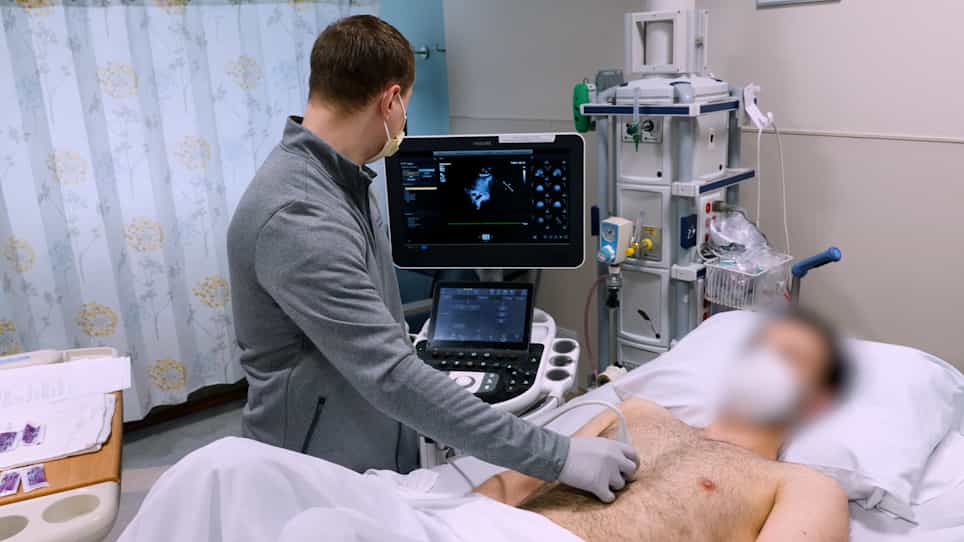

Image Acquisition Method for the Sonographic Assessment of the Inferior Vena Cava
Published on: January 13, 2023
The clinical outcome after inferior vena cava thrombosis in early infancy
1Department of Paediatrics, University Hospital RWTH Aachen, Germany. Haeusler@RWTH-Aachen.de

Insights
Infants with inferior vena cava thrombosis often experience persistent clots, leading to long-term health issues like kidney problems and leg pain. Further research is needed for effective infant thrombosis treatments.
Area of Science:
- Pediatric Thrombosis
- Vascular Health
- Neonatal Medicine
Background:
- The long-term clinical outcomes of inferior vena cava thrombosis in infants are not well-established.
- This condition can occur in premature and full-term newborns.
Purpose of the Study:
- To investigate the long-term clinical outcomes of 12 infants diagnosed with inferior vena cava thrombosis within their first few months of life.
- To identify associated complications and potential risk factors.
Main Methods:
- Retrospective clinical follow-up of 12 infants with inferior vena cava thrombosis (gestational age 24-41 weeks).
- Data collected on associated conditions (renal venous thrombosis, adrenal bleeding), potential causes (central venous catheter, Factor V Leiden mutation), treatments (thrombolysis, surgery), and long-term sequelae.
- Follow-up duration averaged 7+/-3 years.
Main Results:
- Inferior vena cava thrombosis frequently persisted (occlusion or stenosis in 6/12 infants) despite treatments like thrombolysis or surgery.
- No deaths directly attributed to the thrombosis occurred.
- Long-term complications included extensive internal collaterals (6/12), varicosis (5/12), leg pain (3/12), and persistent renal disease with hypertension (3/12).
- Spontaneous recanalization occurred in some cases without effective therapy.
Conclusions:
- Infantile inferior vena cava thrombosis often leads to persistent vascular changes and significant long-term morbidity.
- Current therapeutic strategies may be insufficient, highlighting the need for novel approaches to early and ongoing management.
Unlabelled:
The clinical outcome after inferior vena cava thrombosis in early infancy is unknown. We report the clinical long-term follow-up of 12 patients presenting inferior vena cava thrombosis within their first months of life (gestational age: 24-41 weeks; follow-up: 7+/-3 years). Accompanying renal venous thrombosis occurred in 9, and adrenal bleeding in 4 patients. A central venous catheter was related to the thrombosis in only four patients. Heterozygous factor V Leiden mutation was found in two of the eight infants without central venous catheter. Thrombolysis was performed in seven and effective in three infants; one infant required surgical thrombectomy. In three of eight infants with ineffective or with no therapy, spontaneous recanalization occurred during follow-up. No patient died of the thrombosis. Although no long-term anticoagulatory prophylaxis was performed, none of the children with persisting occlusion (n = 5) or stenosis (n = 1) of the inferior vena cava developed symptomatic thrombo-embolic complications. However, extensive internal collaterals (n = 6), visible varicosis (n = 5), pain in the legs (n = 3) and persisting renal disease (n = 3) with arterial hypertension (n = 2) were observed during follow-up.
Conclusion:
Inferior vena cava thrombosis of early infancy frequently persists and may cause considerable long-term morbidity. New strategies for early and long-term therapy are necessary.
More Related Videos

Related Concept Videos
 01:20
Venous Thrombosis II: Clinical Manifestations and Diagnostic Studies
 01:29
Venous Thrombosis III: Interprofessional Care
 01:29
Pulmonary Embolism II: Diagnostic Studies and Interprofessional Care