Related Experiment Video
Updated: Oct 20, 2026
Experimental Approach to Examine Leptin Signaling in the Carotid Bodies and its Effects on Control of Breathing
Published on: October 25, 2019
Elevation of plasma leptin concentrations in obese hyperinsulinaemic hypothyroidism before and after treatment
A Kautzky-Willer1, C Ludwig, P Nowotny
1Department of Internal Medicine III, University of Vienna, Austria.

Background:
Plasma leptin is considered to play a role in maintenance of energy balance and body weight by neuroendocrine mechanisms. Thyroid hormones are permissive for adrenergic activation, which in turn has been shown to decrease leptin expression. This study was therefore designed to test the hypothesis that hyperthyroidism results in lower leptin concentrations, whereas hypothyroidism leads to higher plasma leptin concentrations. In addition, the effects of normalization of thyroid function on plasma leptin were investigated.
Materials And Methods:
Fasting plasma leptin concentrations and body fat mass (total body electrical conductivity) were measured in patients with overt hypothyroidism and hyperthyroidism before and after successful treatment. Plasma leptin, glucose, insulin and free fatty acid concentrations were monitored during an oral glucose tolerance test (OGTT 75 g).
Results:
Fasting plasma leptin concentrations were similar in lean patients, independently of their thyroid function (hyperthyroid 12.5 +/- 2 ng mL-1, hypothyroid 10.2 +/- ng mL-1, euthyroid 12.7 +/- 3 ng mL-1). In obese hypothyroid patients, plasma leptin was threefold higher (P < 0.0005) than in lean hypothyroid patients, twofold higher (P < 0.005) than in obese hyperthyroid patients matched for fat mass and 30% increased (P < 0.01) compared with obese euthyroid subjects. There were no differences between fasting and post-prandial (OGTT) leptin concentrations in any group. Normalization of thyroid function did not affect plasma leptin, which remained elevated (P < 0.005) in formerly obese hypothyroid patients. Plasma leptin was not associated with serum thyroid hormones but highly correlated with body mass index and body fat mass in all patients (r = 0.85, P < 0.001). Plasma leptin correlated with plasma insulin concentration only in hyperthyroid patients (P < 0.01, r = 0.64), who presented with blunted stimulation of insulin release and higher plasma glucose (P < 0.05) than hypothyroid subjects.
Conclusion:
The results indicate that (a) the correlation of leptin with body fat mass is preserved in thyroid dysfunction, (b) plasma leptin is markedly increased in obese hypothyroid hyperinsulinaemic patients and (c) plasma leptin is not affected by oral glucose loading.
Related Concept Videos
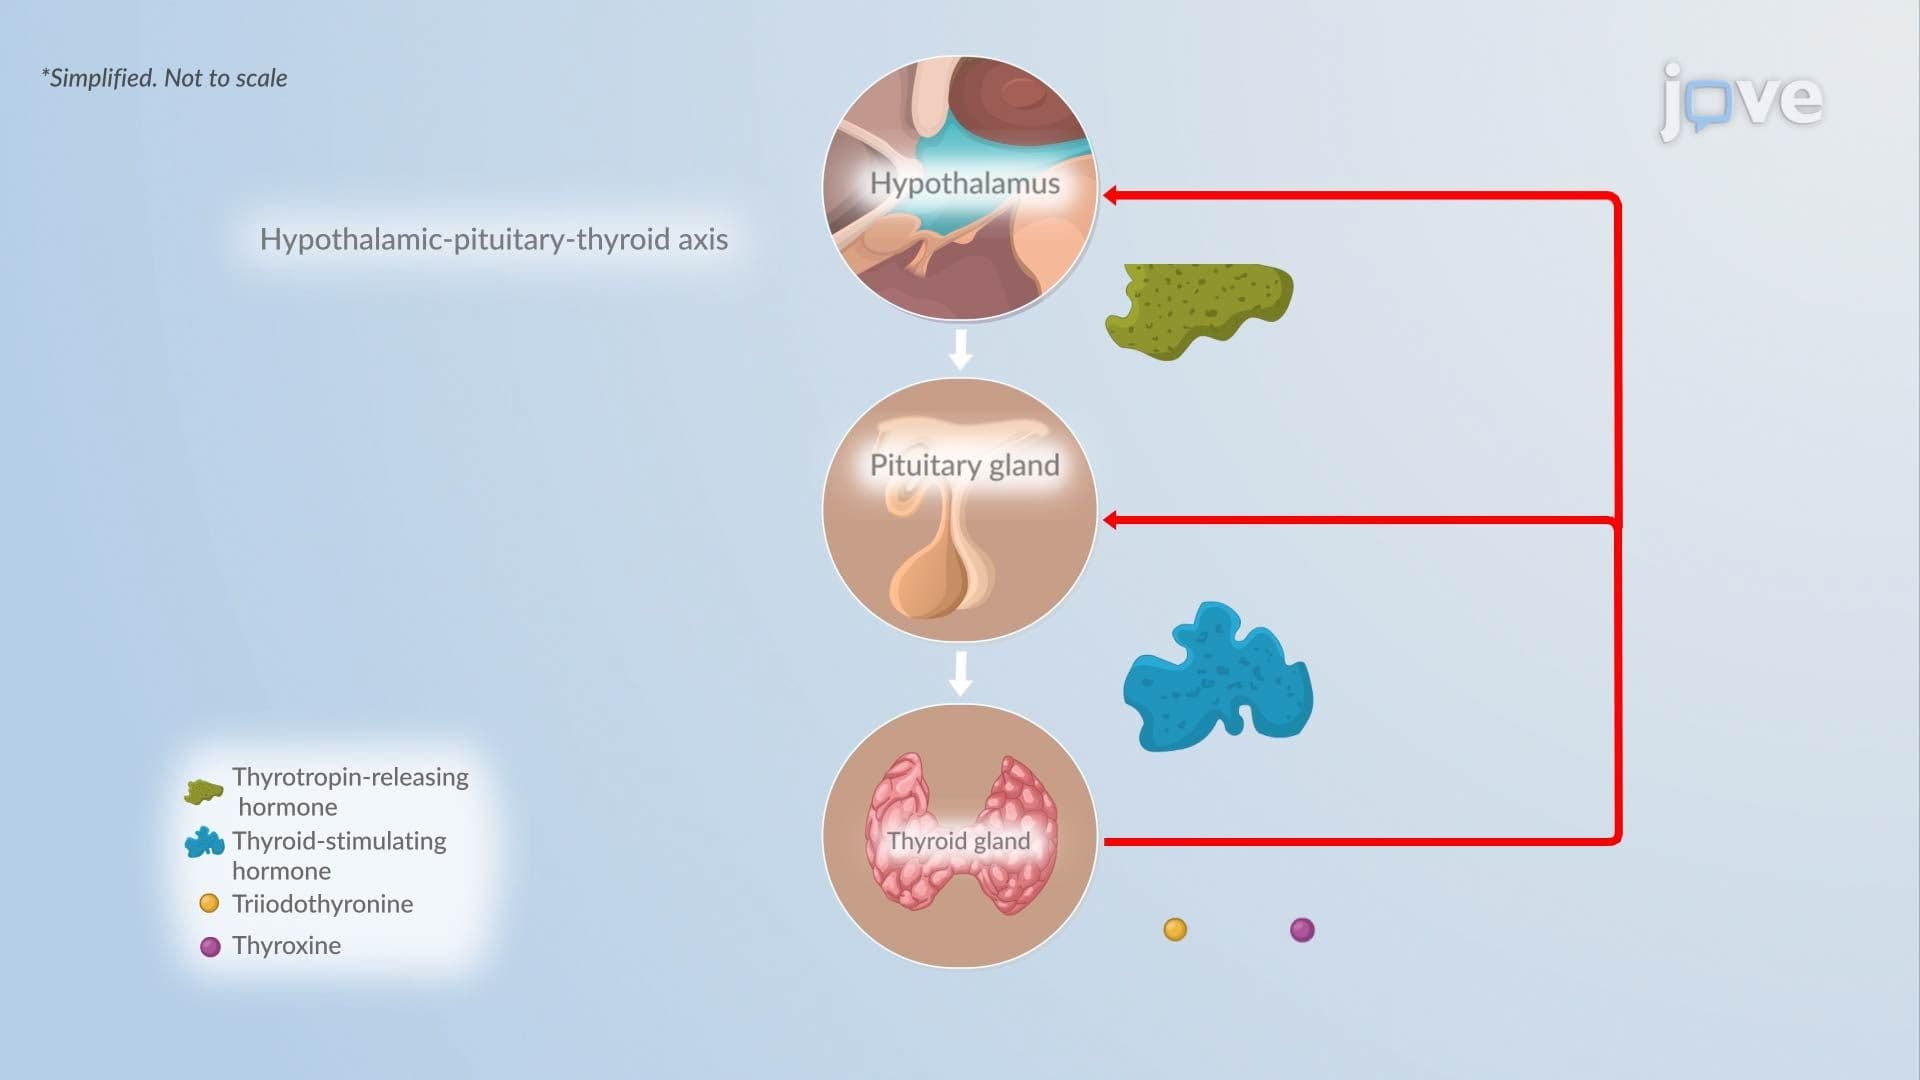 01:25
Hyperthyroidism I: Introduction
 01:25
Pharmacokinetics in Obese Patients: Drug Absorption and Distribution
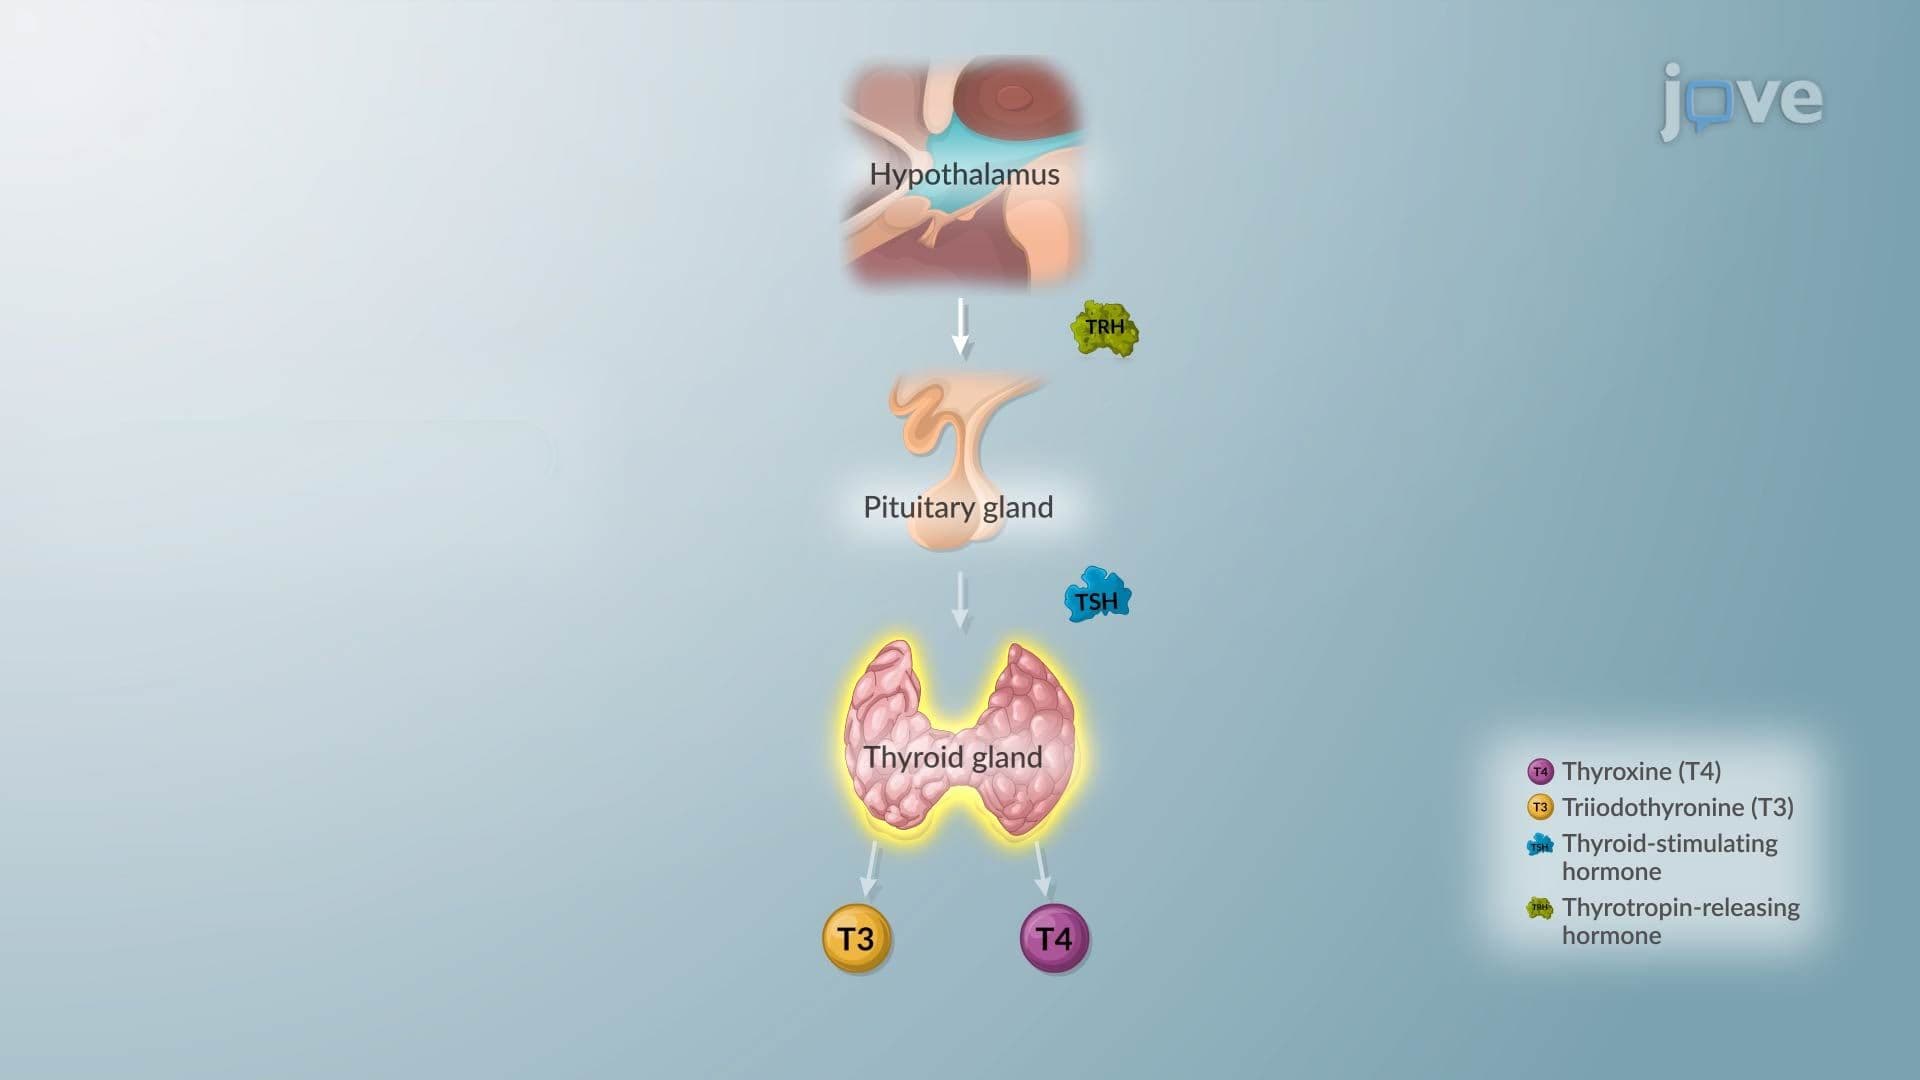 01:23
Hypothyroidism II: Pathophysiology
 01:16
Insulin: Dosing Regimen and Adverse Effects
The basal dose constitutes about 40%-50% of the total daily dose, with the rest as premeal insulin. The mealtime insulin dose should mirror...
 01:20
Pharmacokinetics in Obese Patients: Drug Metabolism and Excretion
 01:26
Hypoglycemia