Related Experiment Video
Updated: Aug 30, 2026


Establishing a Mouse Model of a Pure Small Fiber Neuropathy with the Ultrapotent Agonist of Transient Receptor Potential Vanilloid Type 1
Published on: February 13, 2018
[Critical polyneuropathy]
1Neurologische Universitätsklinik, Heidelberg. ernst_hund@ukl.uni-heidelberg.de

Abstract:
Contrary to earlier belief, muscle weakness and atrophy in critically ill patients is not due to inactivity or disuse but rather caused by neuromuscular disorders arising de novo during the stay in the ICU. Clinical manifestations include delayed weaning from the respirator and prolongation of the rehabilitation phase. The available data indicate that critical illness polyneuropathy is the most frequent cause of such secondary neuromuscular problems. For differential diagnosis prolonged neuromuscular blockade and several myopathies have to be taken into consideration. The pathogenesis of critical illness polyneuropathy is unknown. It has been suggested that the factors mediating the systemic inflammatory response are also responsible for axonal damage in critical illness polyneuropathy. We recently described a neurotoxic activity present in the sera of affected patients, which can be reversed completely by NMDA antagonists. The critical illness per se is unrelated to the development of neuropathy. By contrast, occurrence of myopathies may be triggered by exogenous factors such as high-dose glucosteroids and non-depolarizing muscle blocking agents. Detailed electrodiagnostic studies are desirable in patients with long-lasting ICU stays, whenever possible as weekly monitoring. In doubtful cases, muscle biopsy might be necessary for proper diagnosis and management.
Related Concept Videos
 01:24
Local Anesthetics: Differential Sensitivity of Nerve Fibers
 01:21
Peripheral Arterial Disease II: Clinical Manifestations and Diagnostic Evaluation
 01:19
Type I Diabetes III: Clinical Manifestations
 01:31
Diabetic Foot Ulcer
 01:28
Diabetic Nephropathy
 01:22
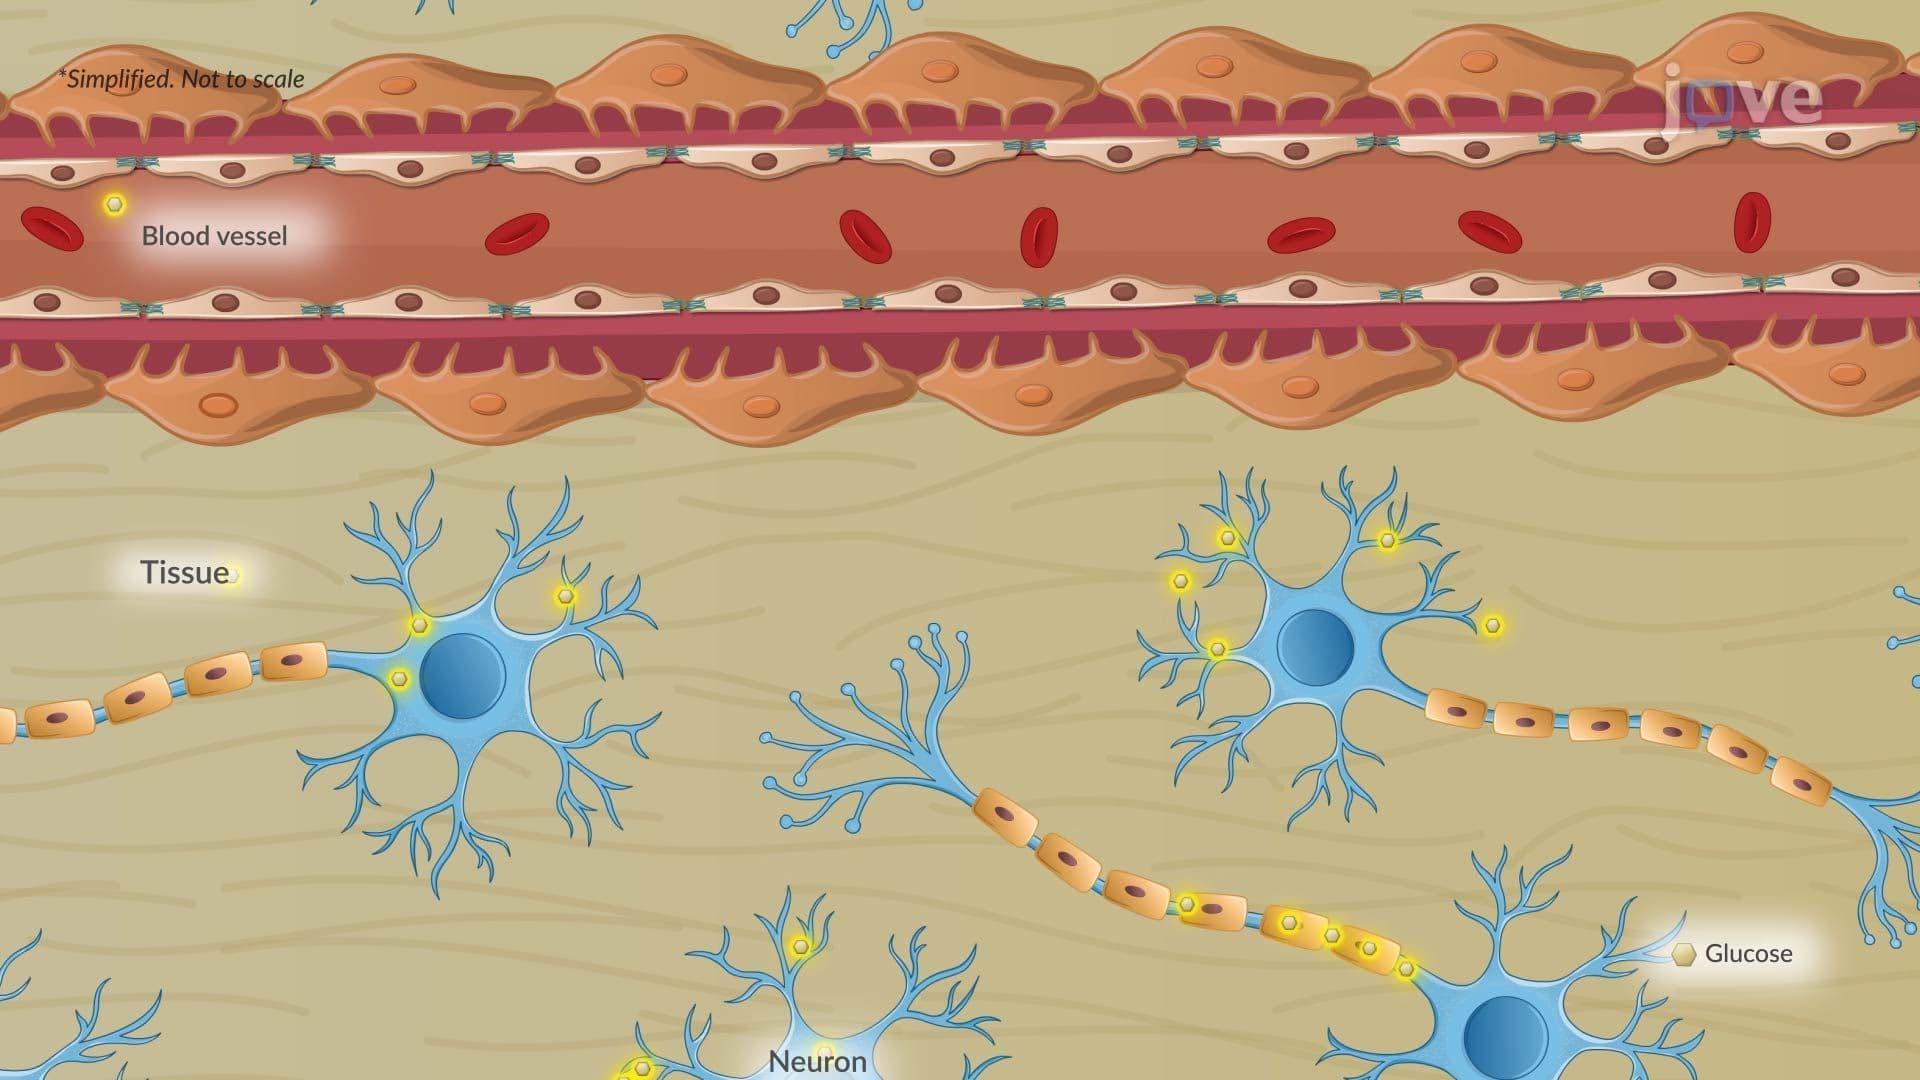
Diabetic Neuropathy